Request for Family or Medical Leave
What is this form?
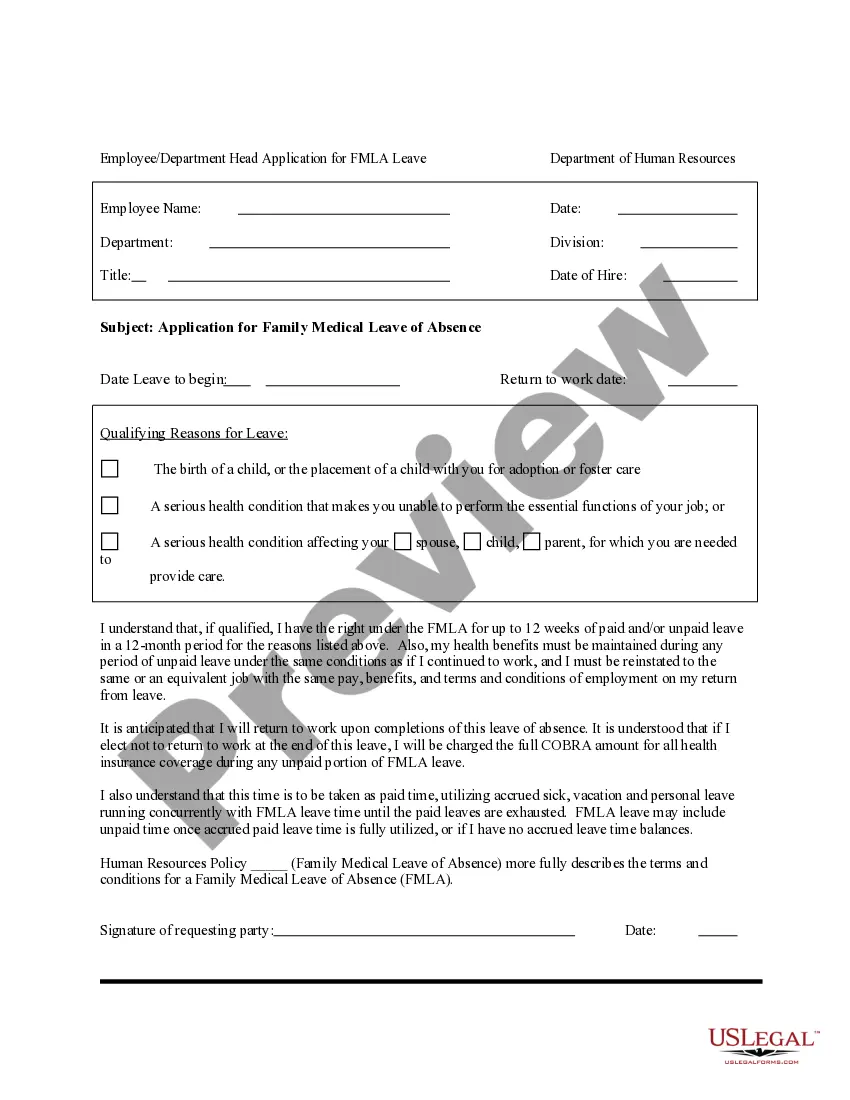
The Request for Family or Medical Leave form is designed for eligible employees to formally request leave under the Family and Medical Leave Act (FMLA). This form differs from other leave requests, as it specifically pertains to unpaid leave for personal medical needs or to care for family members with serious health conditions. It facilitates the processing of intermittent leave or reduced work schedules, ensuring that employees can meet their family and health obligations while maintaining compliance with workplace policies.
Key components of this form
- Employee details: Name, department, title, status, and date of hire.
- Reason for leave: Options include childbirth, adoption, family care, or personal health issues.
- Intermittent leave schedule: Specify the schedule for reduced hours or time off.
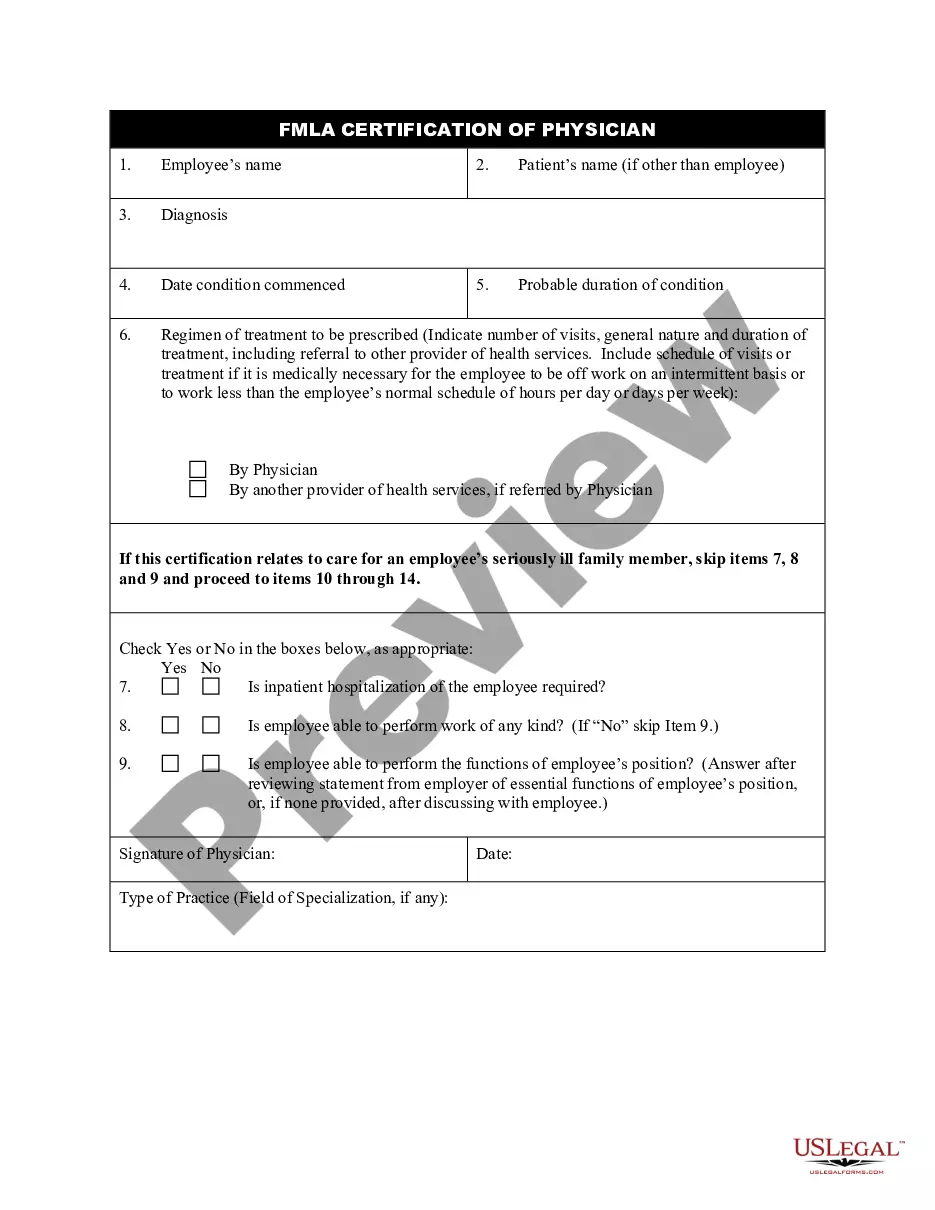
- Certification requirement: A note on the potential need for a health care provider's certification.
- Agreement provisions: Employee acknowledgment of eligibility and conditions for leave.






When this form is needed
This form should be used when an employee needs to request leave for specific qualifying reasons under the FMLA. Typical situations for using this form include taking time off for the birth or adoption of a child, caring for a seriously ill family member, or addressing one's own serious health condition. It is essential for those needing intermittent leave or a modified work schedule to also use this form to ensure proper documentation and compliance.
Who needs this form
- Employees who have been employed for at least one year and have worked a minimum of 1,250 hours during the past 12 months.
- Individuals who require family or medical leave due to personal health conditions or to care for immediate family members.
- Employees who need to set up intermittent leave or a reduced work schedule for qualifying FMLA reasons.
How to complete this form
- Enter your personal details, including name, department, and title.
- Select the reason for your leave from the provided options and fill in relevant dates.
- If applicable, specify the schedule for any intermittent leave.
- Provide information about any previous family or medical leave taken in the past twelve months.
- Sign and date the form, and ensure your supervisor also signs for their records.
Does this form need to be notarized?
Notarization is not commonly needed for this form. However, certain documents or local rules may make it necessary. Our notarization service, powered by Notarize, allows you to finalize it securely online anytime, day or night.
Get your form ready online
Our built-in tools help you complete, sign, share, and store your documents in one place.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.
Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.
Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.

Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.

Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Avoid these common issues
- Failing to provide adequate notice when the leave is foreseeable.
- Not completing all required fields, which can delay processing.
- Neglecting to attach necessary documentation or certification from healthcare providers, when required.
- Signing the form without verifying all information is correct.
Advantages of online completion
- Convenience: Easily fill out and download the form from anywhere.
- Editability: Make adjustments to your request as needed before submission.
- Reliability: The forms are drafted by licensed attorneys in accordance with legal requirements.
What to keep in mind
- The Request for Family or Medical Leave form is essential for formal leave requests under the FMLA.
- Understanding the reasons and procedures for requesting leave can help prevent delays and misunderstandings.
- Be aware of your rights and responsibilities while on family or medical leave.
Looking for another form?









Form popularity
FAQ
In order to be eligible to take leave under the FMLA, an employee must (1) work for a covered employer, (2) work 1,250 hours during the 12 months prior to the start of leave, (3) work at a location where 50 or more employees work at that location or within 75 miles of it, and (4) have worked for the employer for 12
Dear name, I am writing this letter to inform you that I need to take sick leave from work. I will need to remain off work until date. I've included a letter from my doctor to confirm that I need to take that amount of time off to fully recover.
How Do I Request FMLA Leave? To take FMLA leave, you must provide your employer with appropriate notice. If you know in advance that you will need FMLA leave (for example, if you are planning to have surgery or you are pregnant), you must give your employer at least 30 days advance notice.
The FMLA permits employers to request a doctor's note or medical certification when an employee first requests leave under the FMLA. If the employee is on extended leave, a doctor's note can be requested every 30 days.
They have designated seven different FMLA application forms aligned to the reason for the qualified leave and how much information your employer requires to approve or deny the request. You can download the form from the DOL-WHD website or by calling them at 1-866-487-9243.
You need leave under the Family & Medical Leave Act (FMLA). Your employer gives you a form to have your doctor fill out certifying your need for leave under the FMLA.Under the FMLA, an employer can request that you have your doctor complete a form certifying your need for leave under the FMLA.
Understand your legal rights regarding time off and pay. Make the request in person. Give sufficient advance notice. If possible, work with your boss to develop an agreeable plan. Keep track of relevant paperwork.
Dear (Supervisor / HR Manager): Please be advised that I hereby request an FMLA leave for a period of (number of weeks) in connection with my serious health condition. The leave is to start on (date). Attached is my medical note reflecting the need for FMLA leave.




