Washington Release and Authorization
Overview of this form
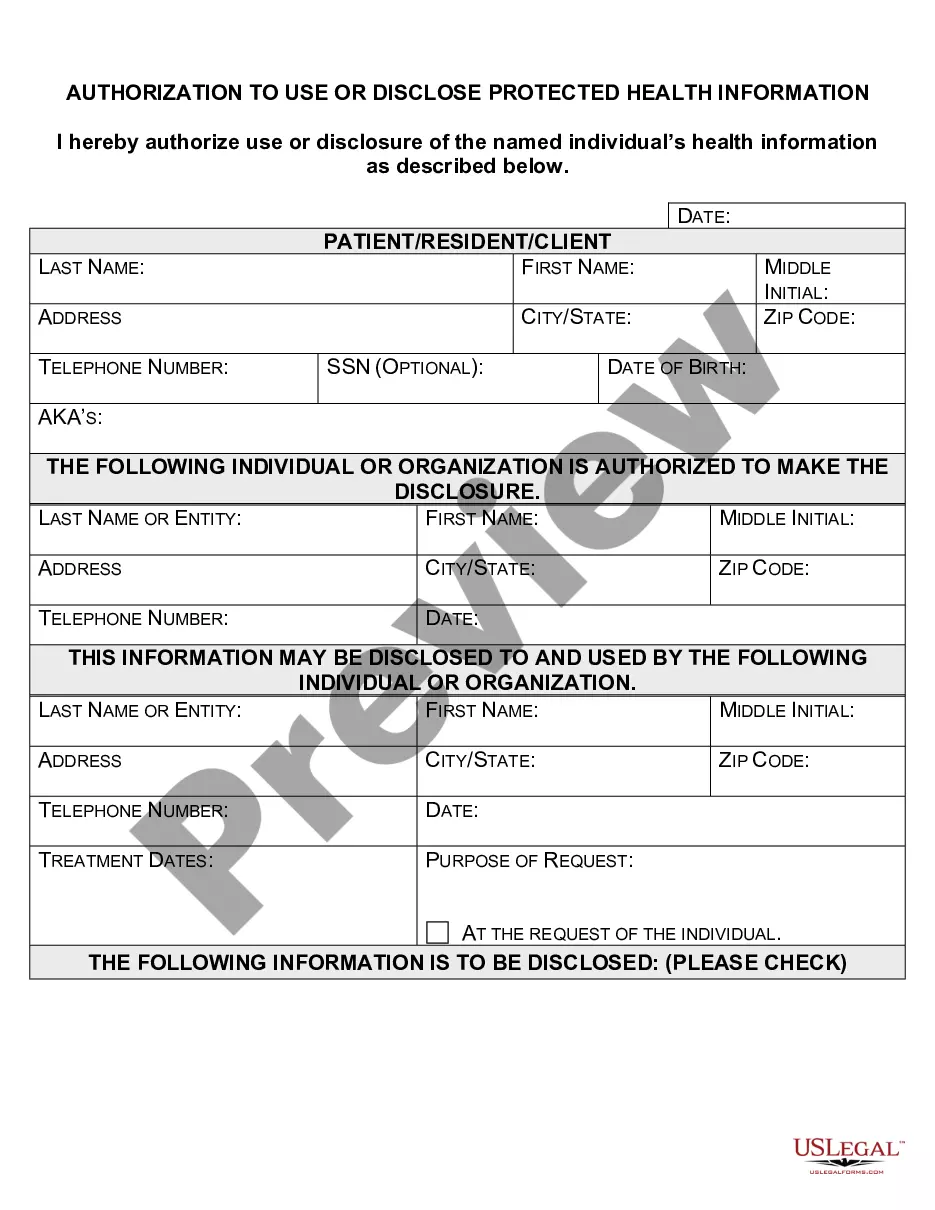
The Washington Release and Authorization is a HIPAA authorization form that allows individuals to authorize their healthcare providers to disclose protected health information. This form is specifically designed to meet the requirements of Washington state, ensuring compliance with both state and federal privacy laws. Unlike other authorization forms, this one is tailored to safeguard your medical information while granting access to designated individuals for specific purposes, such as treatment, billing, or insurance claims.
Key components of this form
- Authorization Section: Allows you to designate the healthcare provider and the person authorized to receive your medical information.
- Effective Period: Specifies that the authorization covers all past, present, and future healthcare periods.
- Extent of Authorization: Authorizes the release of your complete health record.
- Use of Information: Describes how authorized individuals may use your health information.
- Termination Clause: Indicates that the authorization remains valid until the death of the patient.
- Revocation Rights: Outlines your right to revoke the authorization at any time.






When to use this form
This form should be used when you need to allow a specific individual or entity to access your personal health information. Common scenarios include when you're consulting with a new healthcare provider, allowing a family member to handle your medical billing or insurance claims, or when transferring your medical records between facilities. It is essential to have this form in place whenever you want to ensure that your health information is shared in compliance with HIPAA regulations.
Intended users of this form
- Individuals seeking to share their health records with a designated person or entity.
- Patients who want to provide access to their healthcare information for treatment or billing purposes.
- Personal representatives acting on behalf of someone who is unable to complete the form themselves.
Completing this form step by step
- Identify the healthcare provider who will disclose your information by providing their name, title or facility, and contact details.
- Specify the individual or entity you are authorizing to receive your health information.
- Complete the patient information section with your name, address, telephone number, email address, and date of birth.
- Sign and print your name, and include the date of signing to validate the authorization.
- Keep a copy of the completed form for your records.
Is notarization required?
This form does not typically require notarization unless specified by local law. However, it is advisable to check with your healthcare provider or legal advisor for any specific requirements.
Get your form ready online
Our built-in tools help you complete, sign, share, and store your documents in one place.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.
Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.
Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.

Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.

Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Common mistakes
- Failing to include complete and accurate contact information for the healthcare provider.
- Not specifying the exact individual or entity to receive the information.
- Neglecting to sign and date the authorization, rendering it invalid.
- Overlooking the revocation rights clause, which is crucial for patient control over their information.
Why complete this form online
- Convenience of immediate download and access to the form.
- Editability to customize the form to fit individual needs before printing.
- Reliability ensured by professionally drafted content that aligns with legal standards.
Looking for another form?









Form popularity
FAQ
The medical record information release (HIPAA) form allows a patient to give authorization to a 3rd party and access their health records.
By setting up a Release Authorization (ARI), you are giving customer service your permission to disclose information about your accounts to another person. Typically, this is used to give account access to a spouse or other family member.
Authorization. A covered entity must obtain the individual's written authorization for any use or disclosure of protected health information that is not for treatment, payment or health care operations or otherwise permitted or required by the Privacy Rule.
A Privacy Rule Authorization is an individual's signed permission to allow a covered entity to use or disclose the individual's protected health information (PHI) that is described in the Authorization for the purpose(s) and to the recipient(s) stated in the Authorization.
By setting up a Release Authorization (ARI), you are giving customer service your permission to disclose information about your accounts to another person. Typically, this is used to give account access to a spouse or other family member.
A HIPAA authorization form, also known as a HIPAA release form, is a document that individual signs for their health provider before the entity may use or disclose their protected health information (PHI).
The authorization form (sometimes called a patient HIPAA consent form), essentially serves as a handy dandy permission slip allowing a practice or business associate to use or disclose protected health information (PHI) in the ways a patient wants their data used.




