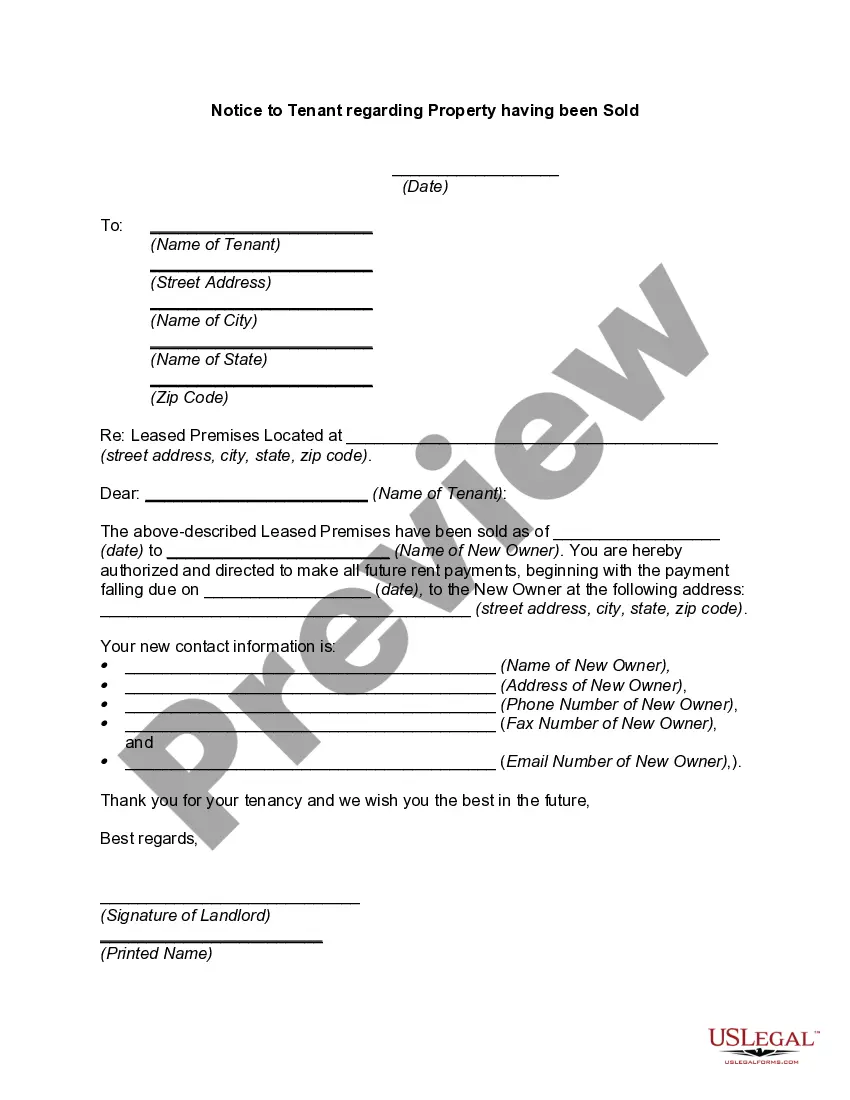
Medical Partnership with Senior Member to Control Policy of Partnership
Understanding this form
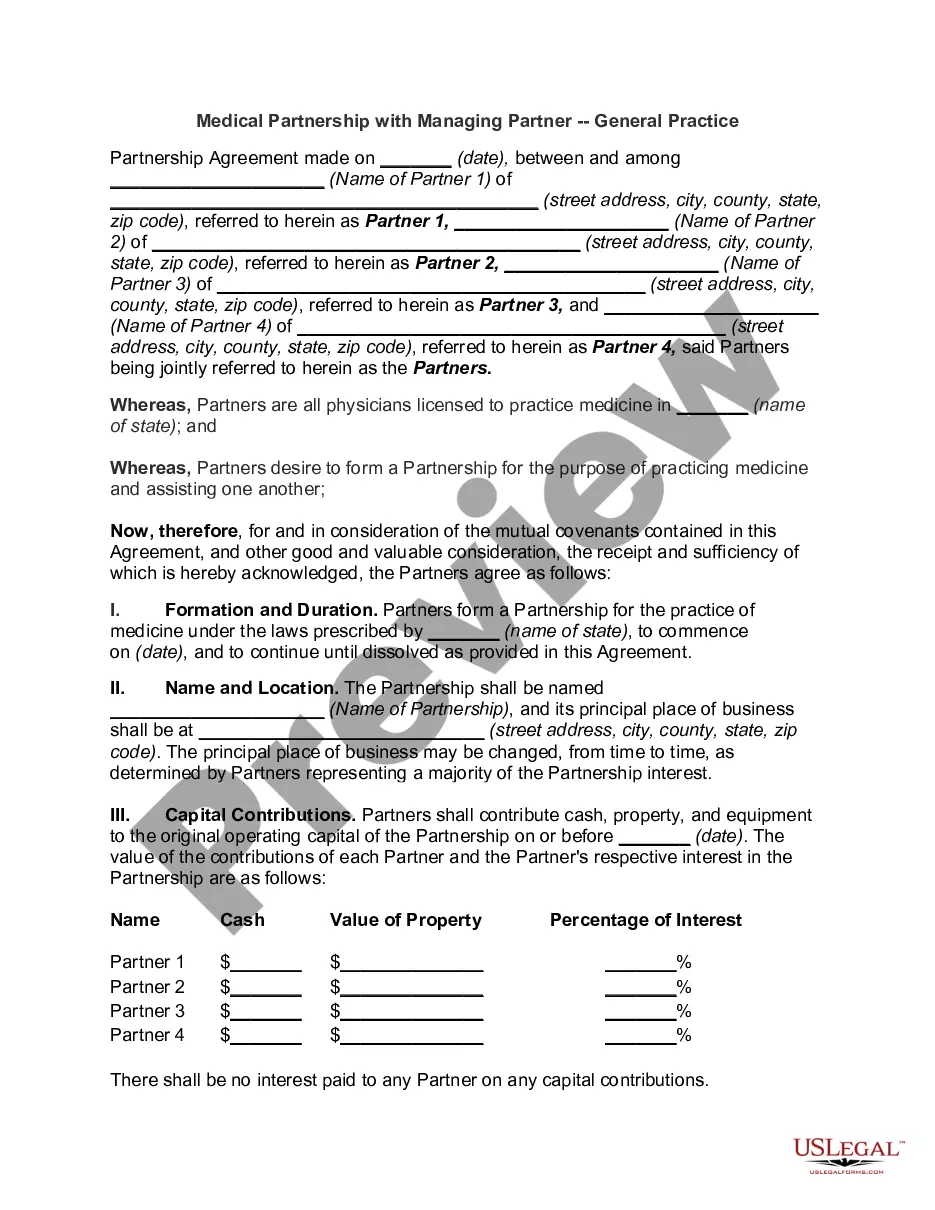
The Medical Partnership with Senior Member to Control Policy of Partnership is a legal document that outlines the framework for establishing a medical partnership among physicians. This agreement specifies the roles and responsibilities of partners, compensation arrangements, and how decisions regarding the partnership will be made. It is essential for managing the unique structures of medical practices compared to standard business partnerships, particularly with the emphasis on leadership and control by a senior member.
What’s included in this form
- Partnership Agreement Date: Specifies when the agreement becomes effective.
- Partner Information: Details on each partner, including names and addresses.
- Duration of Partnership: Outlines the term of the partnership and termination conditions.
- Compensation Structure: Defines how profits and salaries will be distributed among partners.
- Senior Partner Designation: Identifies the partner in charge of policy decisions and transitions of leadership.
- Matters of Policy: Dictates how decisions regarding work types and fees will be made.











When this form is needed
This form is ideal for medical professionals looking to establish a partnership that allows for shared resources, responsibilities, and decision-making within their practice. It is particularly useful when multiple physicians want to collaborate under a single entity while ensuring clarity in financial arrangements and leadership roles.
Intended users of this form
- Physicians planning to set up a medical practice partnership.
- Healthcare professionals involving multiple partners within their practice.
- Existing partners looking to formalize or revise their partnership agreements.
How to complete this form
- Identify each partner involved in the medical partnership, including their full names and addresses.
- Specify the effective date of the partnership and the intended duration.
- Detail the compensation structure, including base salaries and profit distribution percentages.
- Designate a senior partner responsible for policy decisions and transitions of leadership within the practice.
- Each partner should review and sign the agreement to finalize the partnership.
Does this document require notarization?
This form does not typically require notarization unless specified by local law. Always check your state regulations to ensure compliance.
Get your form ready online
Our built-in tools help you complete, sign, share, and store your documents in one place.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.
Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.
Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
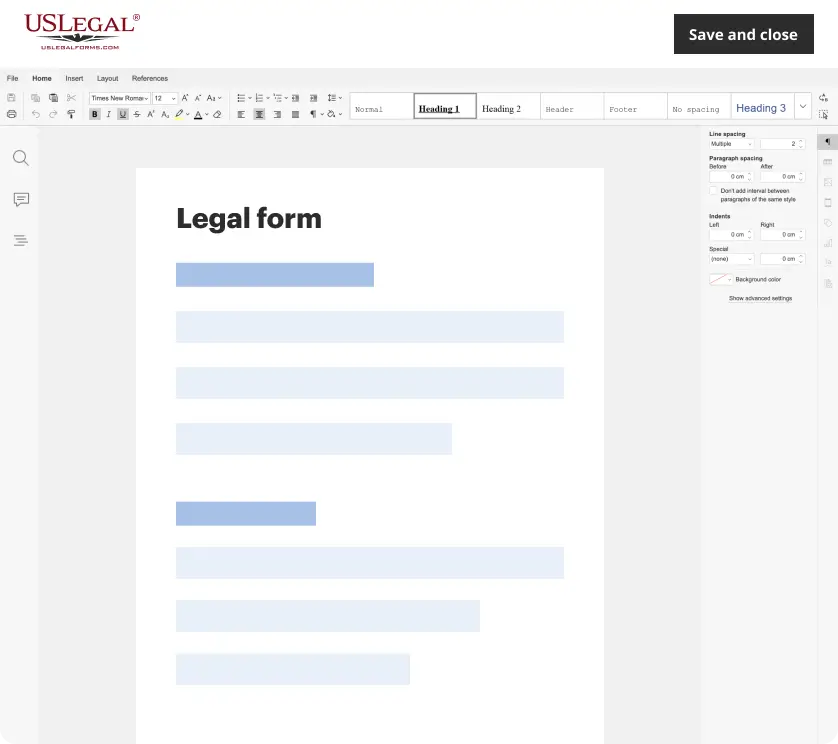
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.

Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.

Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Common mistakes to avoid
- Failing to clearly define roles and responsibilities of each partner.
- Not specifying the compensation structure adequately, leading to future disputes.
- Neglecting to include essential clauses regarding exiting the partnership.
Advantages of online completion
- Easy access and immediate download for quick setup.
- Editable templates that allow customization to fit specific partnership needs.
- Reliability of legal documents drafted by licensed attorneys.