New Mexico Release and Authorization
What is this form?
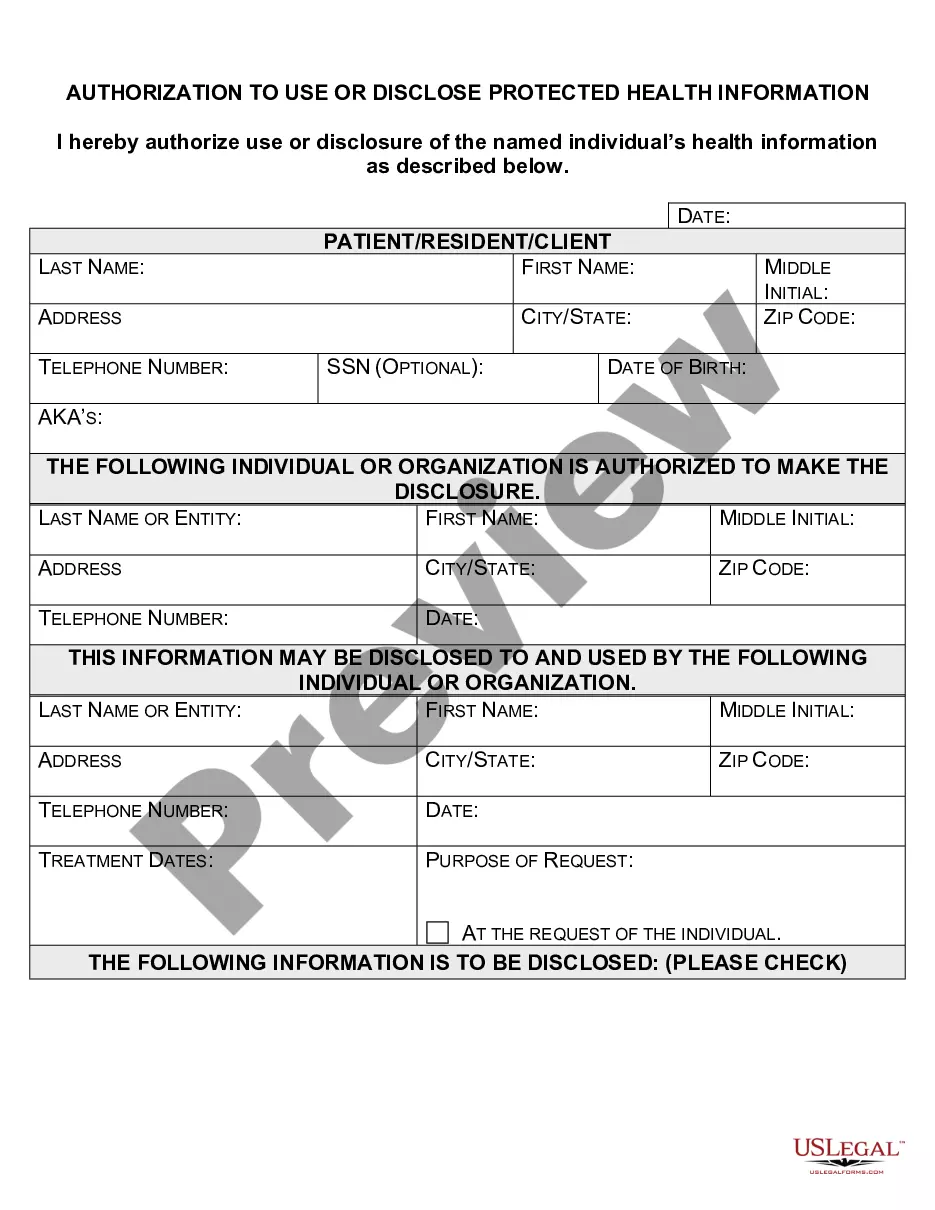
The New Mexico Release and Authorization is a HIPAA authorization form specifically designed for residents of New Mexico. This form allows individuals to authorize their healthcare providers to disclose their protected health information to designated individuals. By using this form, patients can ensure that their medical data is shared appropriately for treatment, billing, or other needed purposes while complying with privacy regulations.
What’s included in this form
- Authorization statement: Authorizes a healthcare provider to release protected health information.
- Effective period: Specifies that the authorization applies to all past, present, and future healthcare periods.
- Extent of authorization: Indicates the release of complete health records.
- Use of information: Defines the purposes for which the information may be used.
- Termination details: States that the authorization remains valid until the patient's death.
- Revocation rights: Explains the patient's right to revoke authorization at any time in writing.






Common use cases
This form is used when a patient needs to grant permission for their healthcare provider to share their medical records with a specific person or organization. This may be necessary for reasons such as seeking a second opinion, coordinating care, or processing medical bills. It is essential to have this form completed if you want to ensure that your private health information is shared appropriately.
Who should use this form
- Patients in New Mexico seeking to authorize the release of their personal medical information.
- Individuals who wish to facilitate communication between their healthcare providers and third parties, such as family members or healthcare consultants.
- Legal guardians or personal representatives acting on behalf of patients who need to disclose health information.
How to complete this form
- Identify your healthcare provider's name, title or facility, and contact details.
- Fill in your personal information, including name, address, phone number, email, and date of birth.
- Specify the individual or organization you are authorizing to receive your health information.
- Provide your signature and date to validate the authorization.
- Keep a copy of the completed form for your records and provide a copy to your healthcare provider.
Does this form need to be notarized?
This form does not typically require notarization unless specified by local law. However, it is recommended to check for any specific state requirements that may apply to your situation.
Get your form ready online
Our built-in tools help you complete, sign, share, and store your documents in one place.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.
Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.
Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.

Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.

Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Mistakes to watch out for
- Failing to specify the recipient of the health information clearly.
- Not including complete contact information for the healthcare provider.
- Overlooking the need to sign and date the form.
- Neglecting to indicate any specific limitations on the use of health information.
Benefits of completing this form online
- Convenience: Download the form anytime and anywhere you have internet access.
- Editability: Easily fill in the necessary information and customize as needed.
- Reliable templates: Access forms drafted by licensed attorneys to ensure compliance with legal standards.
Legal use & context
- This form serves as a legal document that authorizes the disclosure of protected health information.
- It complies with federal HIPAA regulations, ensuring that your rights to privacy are respected.
- Proper completion and use may help prevent legal issues surrounding the unauthorized sharing of health information.
Summary of main points
- The New Mexico Release and Authorization allows you to manage who has access to your health information.
- This form should be used whenever you need to authorize your healthcare provider to share your medical data.
- Completing the form accurately is essential to ensure your privacy rights are upheld.
Looking for another form?








Form popularity
FAQ
A New Mexico tax power of attorney (Form ACD-31102) is a form that gives a taxpayer authority to select up to two (2) representatives the power to handle tax matters on their behalf before the New Mexico Taxation and Revenue Department (TRD).
A HIPAA authorization form, also known as a HIPAA release form, is a document that individual signs for their health provider before the entity may use or disclose their protected health information (PHI).
I understand that this information is protected by law and cannot be released/requested without my written consent unless otherwise provided by law. I further understand that this consent may be revoked by me, in writing at any time, except if the information has already been released or obtained.
Description. The Third Party Authorization form authorizes a person other than the payor or recipient to act on the payor's or recipient's behalf. A Family Responsibility Office (FRO) support payor or support recipient may designate this person to request and receive information from the FRO regarding their case.
By setting up a Release Authorization (ARI), you are giving customer service your permission to disclose information about your accounts to another person. Typically, this is used to give account access to a spouse or other family member.




