Health Information Privacy Complaint for filing with Dept. of Health and Human Services Office of Civil Rights
What this document covers
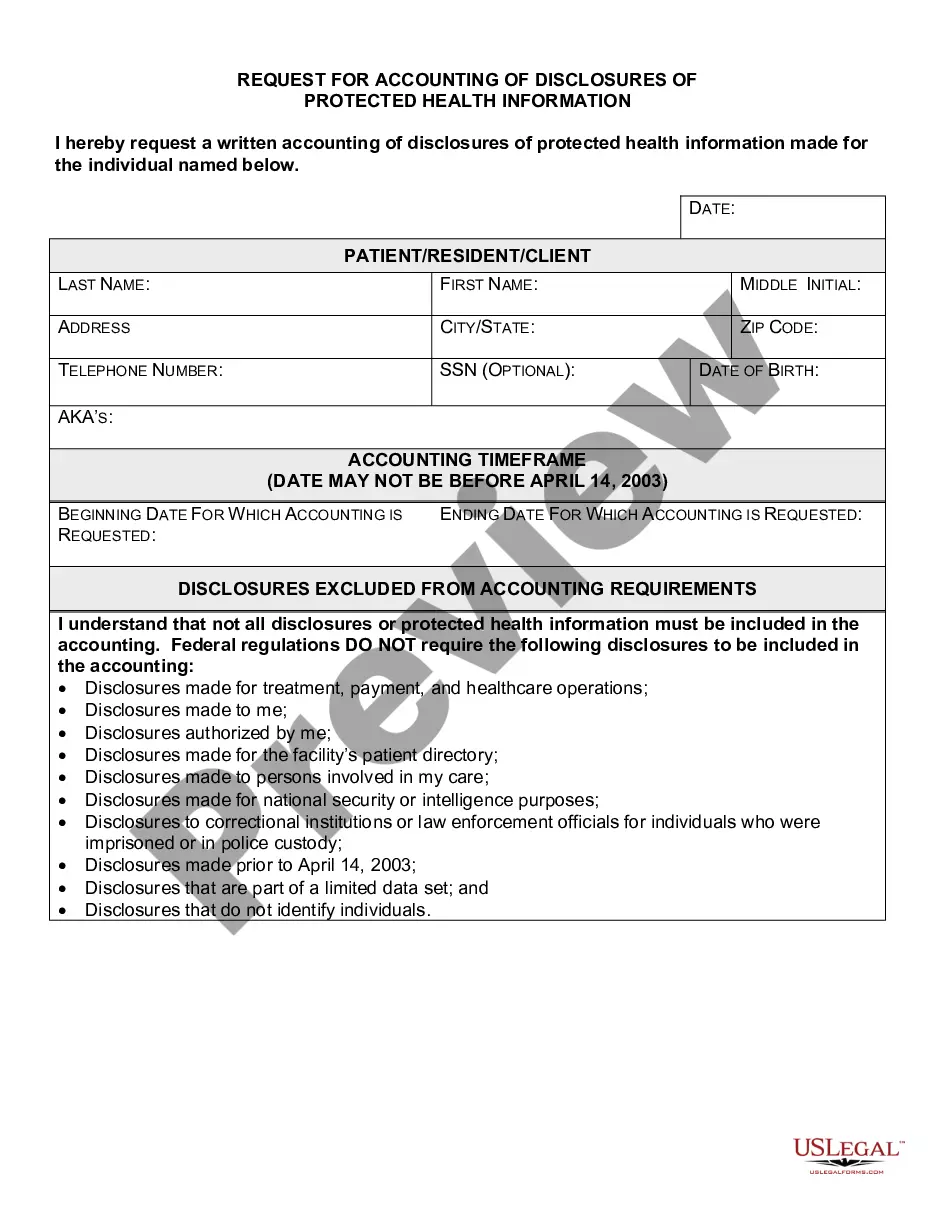
The Health Information Privacy Complaint form allows individuals to report violations of their health care privacy rights. Specifically, it is used to file complaints with the Department of Health and Human Services Office of Civil Rights (OCR) regarding breaches of the Privacy Rule under the Health Insurance Portability and Accountability Act (HIPAA). This form is distinct because it focuses on health information privacy issues and provides a structured way to present grievances to the appropriate authorities.
Key components of this form
- Identification of the complainant and the individual whose rights are believed to have been violated.
- Details of the entity or individual suspected of committing the violation.
- Date(s) when the privacy violation occurred.
- A detailed description of the incident(s) leading to the complaint.
- Information about whether the complaint has been filed with any other agency or court.
- Optional sections for demographic information to aid in public service improvement.







When to use this form
This form should be used when an individual believes that their health information has been disclosed without their consent, or when a health care provider or organization has not adhered to privacy regulations outlined in HIPAA. Examples include unauthorized access to medical records, failure to protect health information, or improper sharing of health information with third parties.
Who needs this form
This form is intended for:
- Employees who feel their health care privacy rights have been violated.
- Individuals filing a complaint on behalf of someone else.
- Patients who have concerns about unauthorized access or use of their health information.
Completing this form step by step
- Indicate whether you are filing the complaint for yourself or someone else.
- Fill in the name of the person or entity you believe violated privacy rights.
- Provide the date(s) when you believe the violation occurred.
- Describe the circumstances surrounding the privacy violation in detail.
- Sign and date the form to validate your complaint.
- Optionally, provide demographic information for internal reporting purposes.
Does this form need to be notarized?
This form does not typically require notarization unless specified by local law. Users can complete and submit this form without the need for notarization, ensuring a straightforward process for filing complaints regarding health information privacy violations.
Get your form ready online
Our built-in tools help you complete, sign, share, and store your documents in one place.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.
Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.
Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.

Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.

Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Mistakes to watch out for
- Failing to provide specific details about the violation can hinder investigation.
- Not including all necessary contact information for effective communication.
- Submitting the complaint to the wrong department or agency.
Benefits of using this form online
- Quick and easy access to the form for immediate use.
- Downloadable version allows users to complete it at their convenience.
- Forms drafted by licensed attorneys ensure compliance with legal standards.
Looking for another form?

Form popularity
FAQ
The most common HIPAA violations that have resulted in financial penalties are the failure to perform an organization-wide risk analysis to identify risks to the confidentiality, integrity, and availability of protected health information (PHI); the failure to enter into a HIPAA-compliant business associate agreement;
If you believe your privacy rights have been violated by us, you may file a complaint with us by notifying our Compliance Officer of your complaint. We will not retaliate against you for filing a complaint. You may also complain to us or to the Secretary of Health and Human Services.
You may file a complaint for yourself, your organization, or for someone else. If you need help filing a civil rights, conscience and religious freedom, or health information privacy complaint, please email OCR at OCRMail@hhs.gov or call 1-800-368-1019.
Start by correcting the breach if possiblestop any further disclosure or uses of unauthorized PHI. If the damage is already done, take measures to mitigate the breach. By completing an investigation, you should understand what caused the breach and determine ways of preventing similar breaches in the future.
If a patient or personal representative complains about a breach of confidentiality or a violation of a HIPAA rule, notify your supervisor and contact the representative listed on the Notice of Privacy Practices.
A HIPAA violation is a failure to comply with any aspect of HIPAA standards and provisions detailed in detailed in 45 CFR Parts 160, 162, and 164.Failure to maintain and monitor PHI access logs. Failure to enter into a HIPAA-compliant business associate agreement with vendors prior to giving access to PHI.
If you believe that a HIPAA-covered entity or its business associate violated your (or someone else's) health information privacy rights or committed another violation of the Privacy, Security, or Breach Notification Rules, you may file a complaint with the Office for Civil Rights (OCR).
Filing a ComplaintIf you believe that a HIPAA-covered entity or its business associate violated your (or someone else's) health information privacy rights or committed another violation of the Privacy, Security, or Breach Notification Rules, you may file a complaint with the Office for Civil Rights (OCR).
To file a complaint with HHS, fill out a "Health Information Privacy Complaint" (PDF) form and file it within 180 days of the alleged act. Make sure you send your complaint to the appropriate regional office, via mail or fax.




