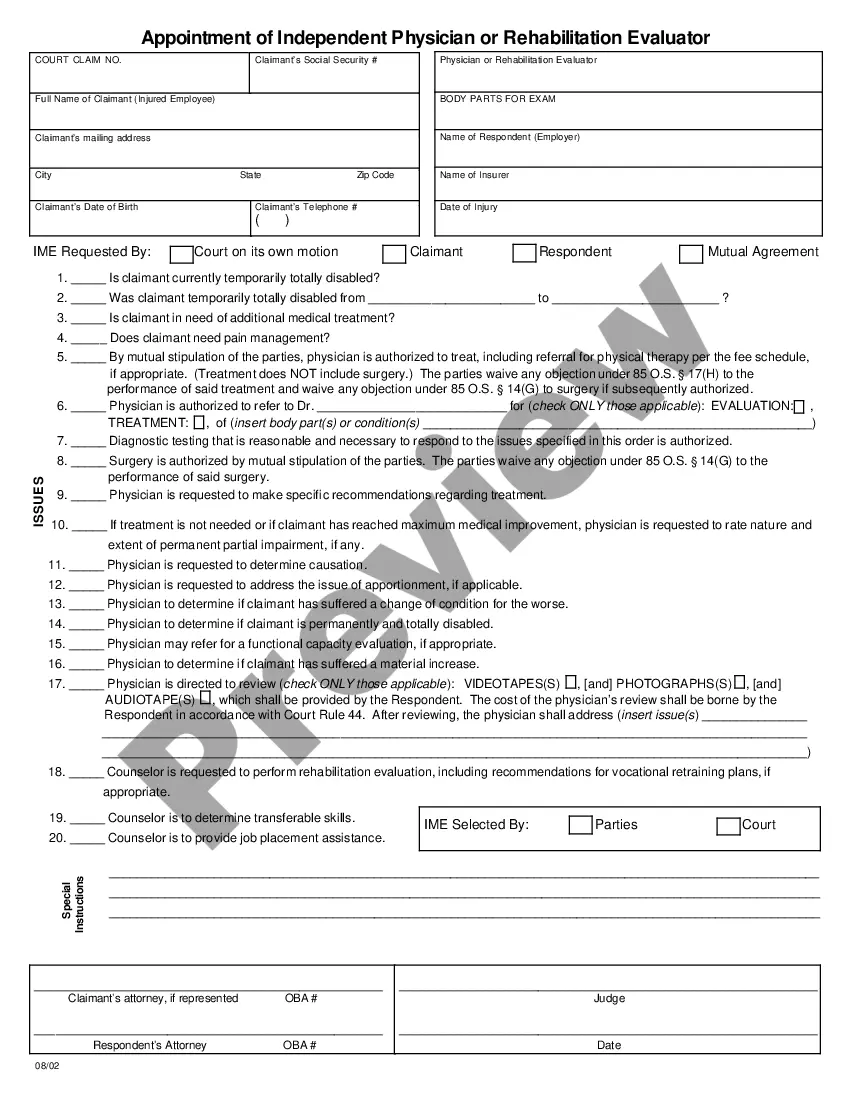
Oklahoma Appointment of Independent Physician or Rehabilitation Evaluator
Overview of this form
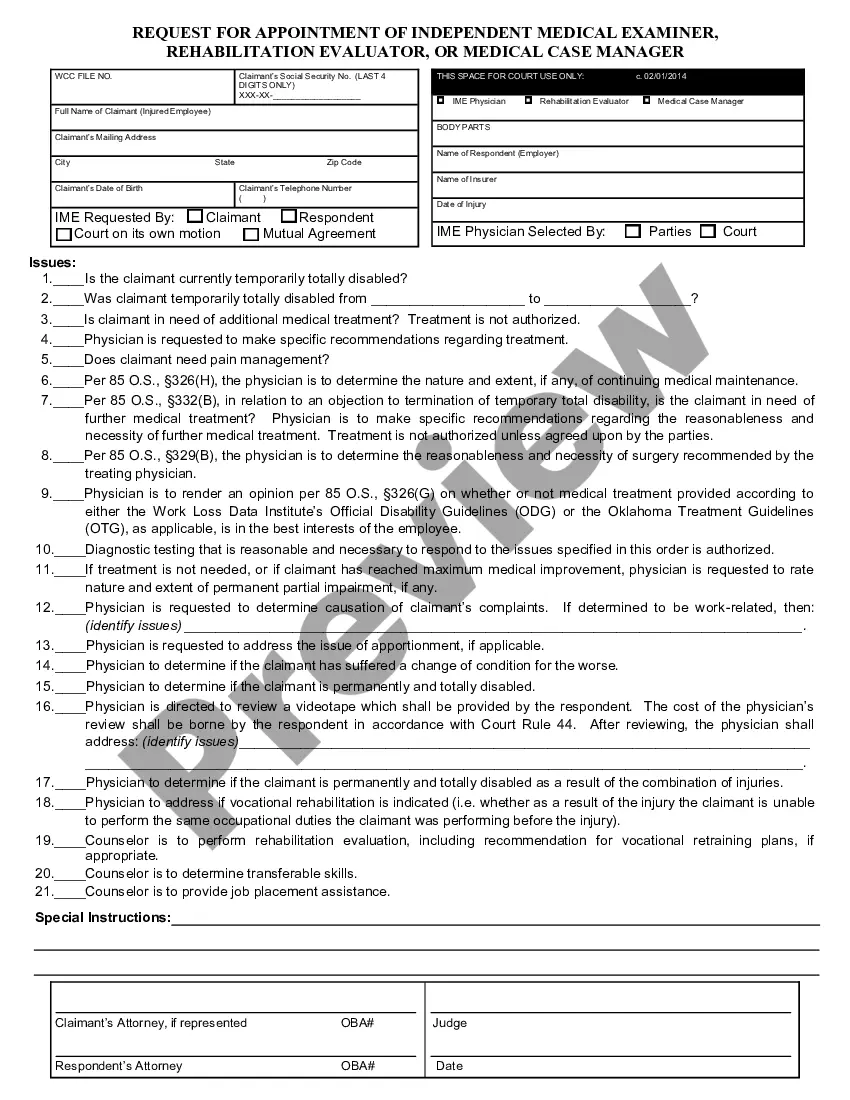
The Appointment of Independent Physician or Rehabilitation Evaluator is an official form utilized within the Oklahoma Workers Compensation system. This document serves to appoint a qualified independent medical examiner or rehabilitation evaluator for assessing claims related to workplace injuries. It is specifically designed to ensure that medical evaluations and treatments comply with Oklahoma laws and regulations. Unlike other forms, this document facilitates the assessment of the injured employee's condition and the necessary medical interventions, providing a structured approach for handling workers' compensation claims.
What’s included in this form
- IME Requested By: Indicates who is requesting the independent medical examination.
- Details regarding the injured employee including name, mailing address, and social security number.
- Questions for the physician regarding the claimant's current medical status and treatment needs.
- Authorization for the physician to conduct evaluations, treatments, and diagnostic tests.
- Instructions for potential surgery and referrals for additional medical opinions.
- Section for attorneys' signatures to ensure legal compliance and representation.

Common use cases
This form should be used when a claimant under Oklahoma's workers' compensation system requires an independent medical evaluation to determine the extent of their injury, capacity for work, or ongoing treatment needs. It is commonly employed in situations where there is a dispute over the claimant's medical condition, ability to return to work, or treatment plan. The form is also used if there is a mutual agreement between parties to seek an independent assessment of the case.
Intended users of this form
- Claimants (injured employees) involved in a workers' compensation case.
- Employers who wish to appoint a medical evaluator to assess an employee's injury.
- Insurers managing a workers' compensation claim.
- Attorneys representing either the claimant or the employer in a workers' compensation dispute.
Completing this form step by step
- Identify the parties involved: enter the details of the claimant, employer, and insurer.
- Specify the date of injury and relevant body parts that require evaluation.
- Answer the evaluation-related questions about the claimant's current medical condition.
- Authorize physicians for treatment and necessary diagnostic tests.
- Include the signatures of both claimant's and respondent's attorneys for legal validity.
Notarization guidance
This form does not typically require notarization unless specified by local law. It's advisable to check for any particular requirements that may apply to your specific situation in Oklahoma.
Get your form ready online
Our built-in tools help you complete, sign, share, and store your documents in one place.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.
Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.
Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.

Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.

Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Typical mistakes to avoid
- Failing to fill out all required fields, which can delay the approval process.
- Not reviewing the form for accuracy before submission.
- Submitting the form without the necessary signatures from all parties involved.
- Overlooking specific instructions regarding treatment authorization when applicable.
Why complete this form online
- Immediate access to the latest legal form templates drafted by licensed attorneys.
- Convenient digital download and printing options for ease of use.
- Editability allows users to customize the form to fit their specific needs before submission.
- Ensured compliance with Oklahoma laws through regularly updated content.