Pennsylvania Release and Authorization
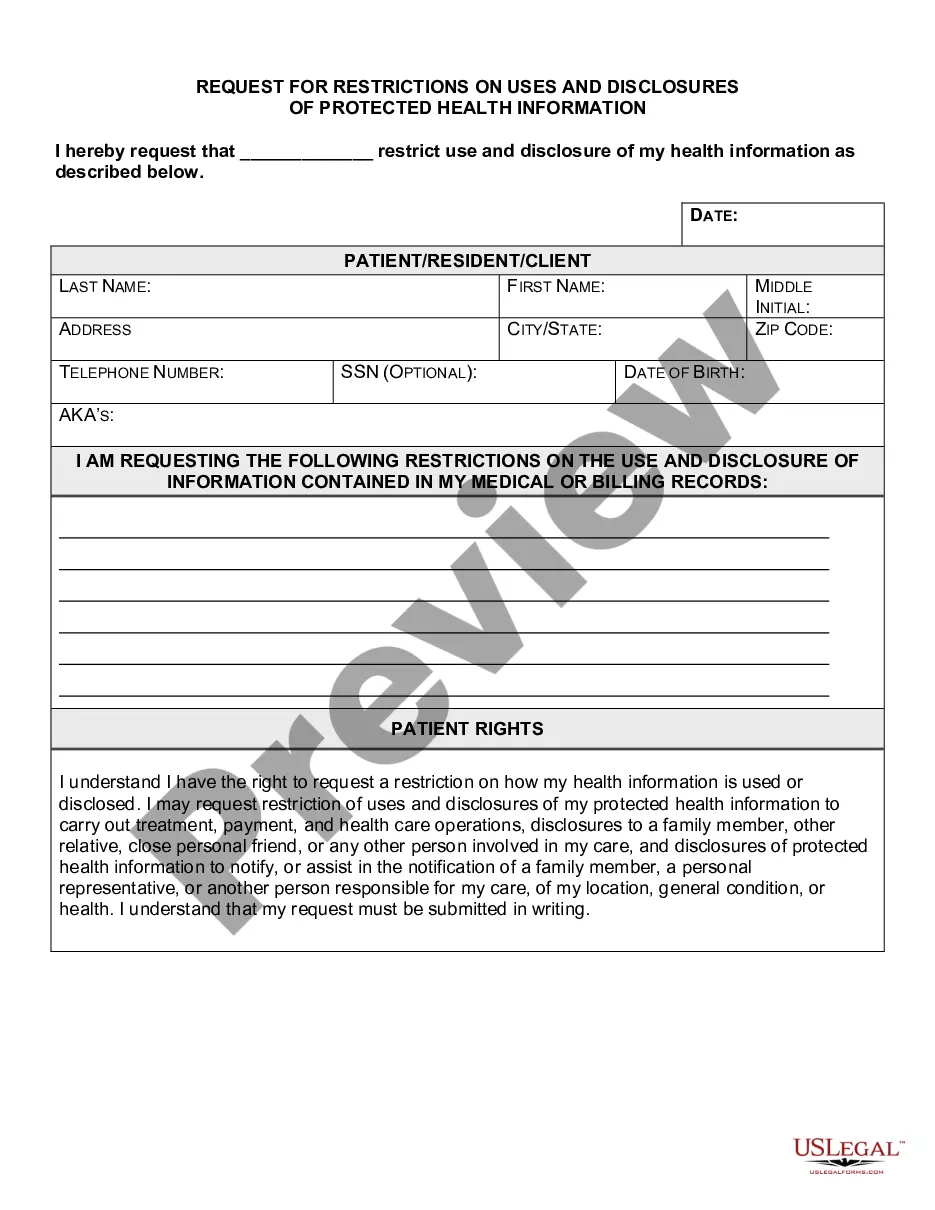
About this form
The Pennsylvania Release and Authorization is a HIPAA authorization form specifically designed for the state of Pennsylvania. This document allows individuals to grant their healthcare providers permission to use and disclose their protected health information. The form is distinct from other medical releases because it adheres to federal and state privacy regulations, ensuring that sensitive health records are shared only with authorized individuals or entities.
Main sections of this form
- Authorization: Grants healthcare providers the right to disclose protected health information.
- Effective Period: Covers all past, present, and future healthcare treatment.
- Extent of Authorization: Authorizes the release of a complete health record.
- Use: Specifies how the disclosed information may be used by authorized individuals.
- Termination: The authorization remains effective until the death of the patient.
- Revocation Rights: Details the patientâs right to revoke authorization at any time.
- Patient Information: Section for personal details such as name, address, and date of birth.






Situations where this form applies
This form is typically used when a patient needs to authorize their healthcare provider to disclose their medical information to another individual or entity. Common scenarios include sharing health records with family members, legal representatives, insurance companies, or other medical professionals for treatment, billing, or consultation purposes.
Who this form is for
- Patients seeking to share their medical information with family members or caregivers.
- Individuals who need to authorize healthcare providers to release their health records to another medical professional.
- Those involved in legal matters requiring health information disclosure.
- Anyone wanting to provide their insurance company with necessary health records for claims processing.
Completing this form step by step
- Fill out the authorization section with your healthcare provider's details, including name and address.
- Designate the individual or entity to whom your health information will be disclosed.
- Specify the extent of information being authorized for release.
- Provide your personal information, including name, address, and date of birth.
- Sign and date the form verifying that you are the authorized patient or representative.
Is notarization required?
This form does not typically require notarization unless specified by local law.
Get your form ready online
Our built-in tools help you complete, sign, share, and store your documents in one place.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.
Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.
Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.

Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.

Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Common mistakes
- Failing to provide complete information about the healthcare provider.
- Not specifying the extent of information being authorized for disclosure.
- Omitting the patient's signature or date on the form.
- Leaving out important personal information like date of birth and contact information.
Why use this form online
- Convenient download and access from anywhere, at any time.
- Editability allows you to fill in necessary information easily.
- Reliability, knowing the form is drafted by licensed attorneys and meets legal standards.
Legal use & context
- This authorization complies with HIPAA regulations for the use and disclosure of protected health information.
- It remains effective until the death of the patient, ensuring long-term validity.
- Revocation rights are included to give control back to the patient.
Main things to remember
- The Pennsylvania Release and Authorization is essential for sharing medical information legally.
- It allows patients to control who can access their health records.
- The form must be completed accurately to ensure the protection of personal health information.
Looking for another form?










Form popularity
FAQ
??Requesting Pennsylvania Tax Records Requests for tax records must be submitted using the REV-467, Authorization for Release of Tax Records. The form should be submitted electronically by using the following fax number: 717-783-4355.
Content for a valid authorization includes: The name of the person or entity authorized to make the request (usually the patient) The complete name of the person or entity to receive the protected health information (PHI) A specific description of the information to be used or disclosed, including the dates of service.
A HIPAA authorization form, also known as a HIPAA release form, is a document that individual signs for their health provider before the entity may use or disclose their protected health information (PHI).
Description. The Third Party Authorization form authorizes a person other than the payor or recipient to act on the payor's or recipient's behalf. A Family Responsibility Office (FRO) support payor or support recipient may designate this person to request and receive information from the FRO regarding their case.
I understand that this information is protected by law and cannot be released/requested without my written consent unless otherwise provided by law. I further understand that this consent may be revoked by me, in writing at any time, except if the information has already been released or obtained.




