Nevada Authorization To Obtain Medical Treatment For Minor Child - Horse Equine Forms
What is this form?
The Authorization To Obtain Medical Treatment For Minor Child is a legal document specifically designed for equine activities. This form serves as a crucial authorization that allows farm management to procure necessary medical treatment for a child who may sustain injuries during equestrian events. It ensures that parents or guardians are responsible for the medical costs, enabling timely care in emergencies. Unlike general medical consent forms, this document addresses equine activities and the unique circumstances surrounding them.
Key components of this form
- Identification of the farm management and parent or guardian involved.
- A clause permitting management to seek medical treatment deemed necessary for the minor child.
- Agreement from the parent or guardian to cover any costs related to medical treatment.
- Details for the child or children, including names and health insurance information.
- Signature lines for the parent or guardian and notarial officer.

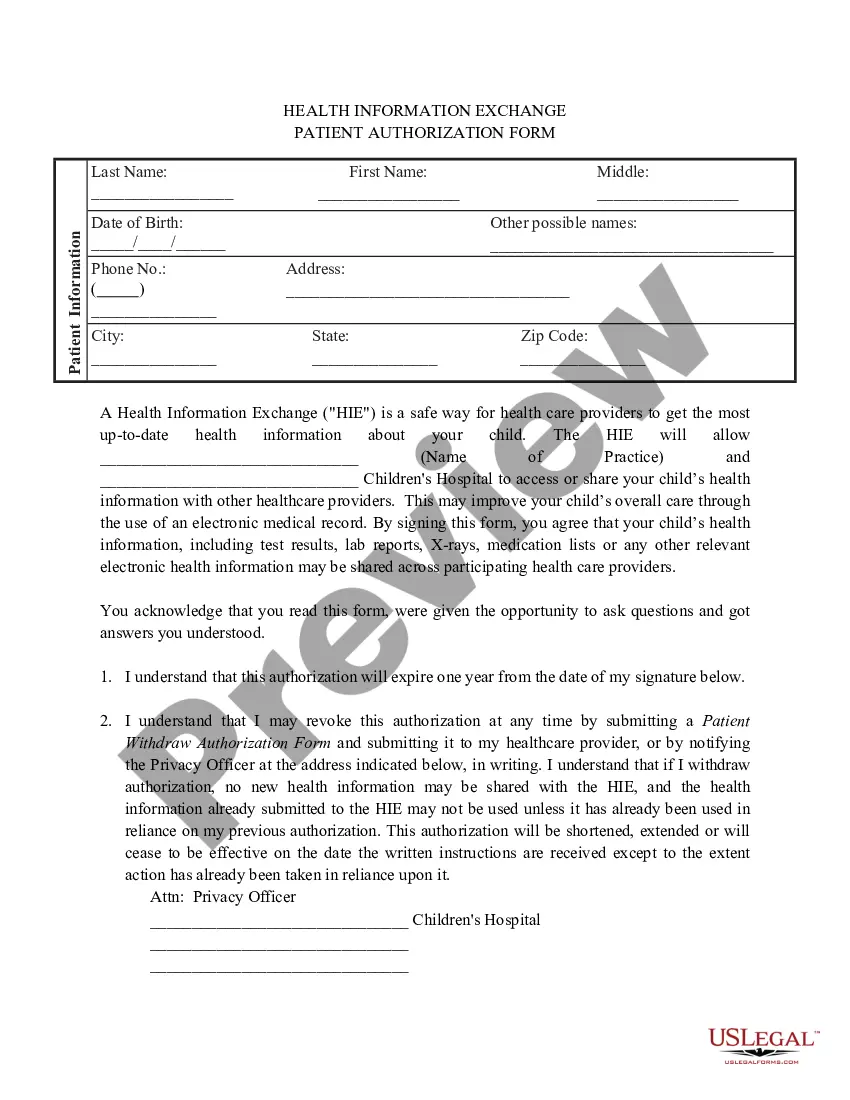
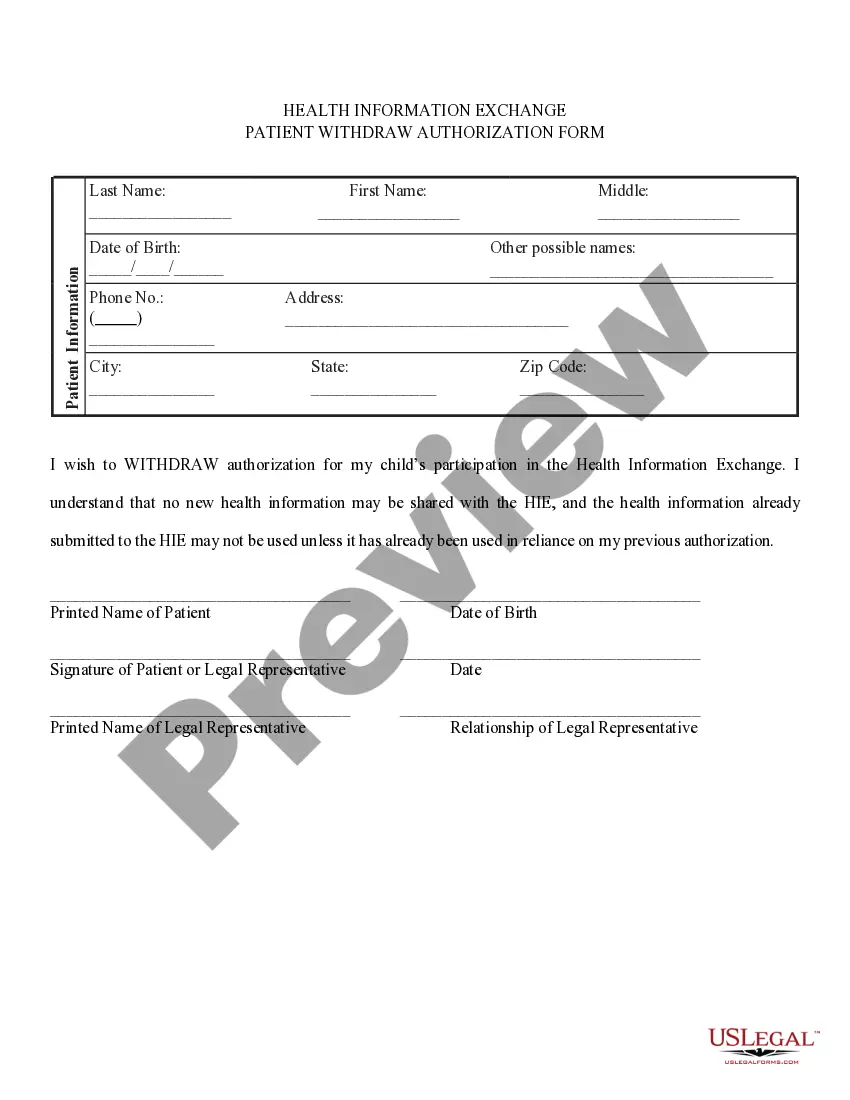

Situations where this form applies
This form should be utilized when a minor child is participating in equestrian activities organized by a farm or ranch. Parents or guardians need to complete this authorization to ensure that, in the event of an injury, the farm management can obtain necessary medical treatment without delays. This is particularly important in emergency situations where immediate medical action is required.
Who can use this document
- Parents or guardians of minor children participating in equine activities.
- Farm management or equestrian event organizers seeking authorizations for minor participants.
- Healthcare providers needing consent for emergency medical treatment for minors in equestrian settings.
Completing this form step by step
- Identify the parties involved: fill in the farm name and parent or guardianâs name.
- List the names and Social Security numbers of the child or children for whom the authorization is given.
- Provide details of the child's health insurance carrier and plan identification number.
- Include the name of the primary healthcare provider in the designated field.
- Sign and date the form as the parent or guardian, and have it notarized if required.
Notarization guidance
This form does not typically require notarization unless specified by local law. However, having it notarized can increase its legal validity. US Legal Forms offers integrated online notarization, available 24/7 through secure video calls, ensuring a seamless and trustworthy process.
Get your form ready online
Our built-in tools help you complete, sign, share, and store your documents in one place.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.
Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.
Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.

Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.

Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Typical mistakes to avoid
- Failing to include all necessary identification details for each child.
- Not providing complete insurance information, which can delay treatment.
- Overlooking the need for signatures from both the guardian and a notarial officer.
Benefits of using this form online
- Convenience of completing and downloading the form from anywhere.
- Editable fields allow for easy customization to fit specific needs.
- Reliable templates created by licensed attorneys, ensuring legal compliance.
Looking for another form?








Form popularity
FAQ
If you share legal custody with your child's other parent or parents, you will want to arrange to have the form notarized together.Once the covered time period is up, a new medical release form will need to be notarized for a caregiver's authority to make medical decisions to continue.
To Whom It May Concern: I, Name of Legal Guardian, am the lawful guardian of the female child named below. I give permission and consent to Name, Address and Phone Number of Temporary Caregiver to authorize medical treatment for Full Name of Child and date of birth.
The top left-hand corner of the page should include name, address, and the date. The name of the recipient and address would come below this information. The opening of the letter should be with Dear, Mr/Ms, or To whom it may concern
Ensure that the formal letter/ email has a clear heading regarding the consent. Explain the requirements (if any) from the respondents. Mention the duration of the program or participation.
A care provider may perform a routine test or treatment on a minor who is over the age of 14 without parental consent and without accompaniment, on condition that the minor him/herself gives informed consent for the medical procedure.
Since the 1990s, California law has afforded minors the right to consent to certain types of medical care, such as the diagnosis and treatment of sexually transmitted diseases, without the consent of their parent or guardian.
The grandparents' medical consent form allows a parent or legal guardian to hand over all responsibility regarding their child's health care decisions to one of the child's grandparents.
Identify yourself by yourself as accurately as possible. Introduce the person or entity to whom you wish to grant authority. Mention their name, their ID number, and how they relate to you. Specify the scope of the authority, that is the allowed actions. Specify any exclusions if any.
MINOR MUST BE EMANCIPATED (GENERALLY 14 YEARS OF AGE OR OLDER) LAW/DETAILS MAY/MUST THE HEALTH CARE PROVIDER INFORM A PARENT ABOUT THIS CARE OR DISCLOSE RELATED MEDICAL INFORMATION TO THEM? An emancipated minor may consent to medical, dental and psychiatric care.





