Tennessee Physician Orders for Scope of Treatment
Overview of this form
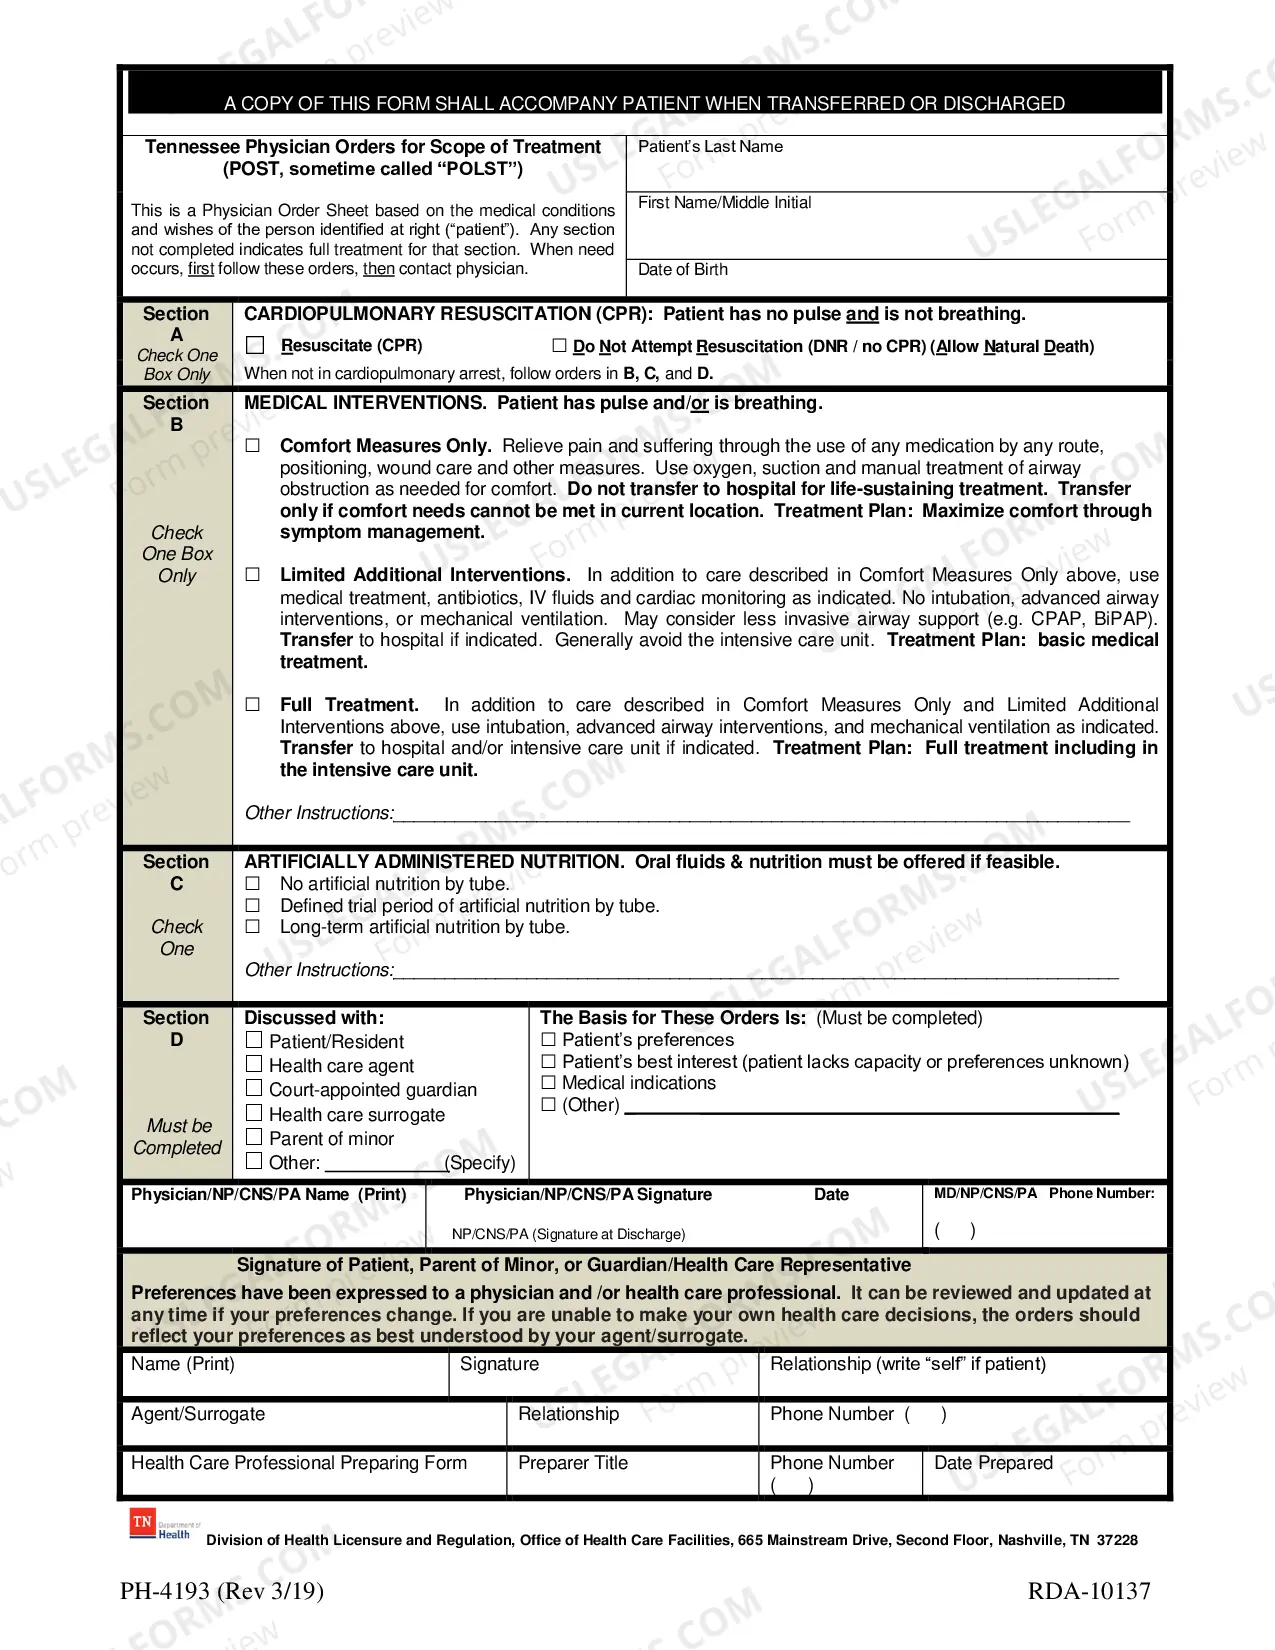
The Tennessee Physician Orders for Scope of Treatment (POST) is a medical form that allows patients to document their preferences regarding end-of-life care. This form is essential for ensuring that healthcare providers understand a patient's wishes related to conditions such as cardiopulmonary resuscitation (CPR), intubation, and artificial nutrition. Unlike other types of medical directives, the POST form is designed to provide specific medical orders that healthcare professionals must follow, making it a critical tool for enhancing patient autonomy in serious health situations.
Key parts of this document
- Patient Information: Section for entering the patient's name and date of birth.
- Cardiopulmonary Resuscitation (CPR) Orders: Indicates whether to resuscitate or to do not attempt resuscitation (DNR).
- Medical Interventions: Outlines the extent of medical treatment preferences, from comfort measures only to full treatment.
- Nutrition Preferences: Specifies choices regarding artificial nutrition.
- Discussion Documentation: Records who discussed the orders with the patient and the basis for these orders.

When this form is needed
This form is used in situations where individuals are facing serious health issues or end-of-life decisions. It is essential when patients wish to communicate their treatment preferences clearly to healthcare providers, especially in emergencies or during transfers between healthcare facilities. The POST form is suitable for patients with chronic or terminal illnesses who want a clear directive regarding their medical treatment options.
Who needs this form
- Patients with chronic or terminal illnesses who want to document their end-of-life care preferences.
- Healthcare agents or surrogates acting on behalf of individuals who may not have the capacity to express their wishes.
- Family members involved in care planning for a loved one facing serious health decisions.
- Healthcare providers seeking to ensure compliance with a patientâs treatment preferences.
How to complete this form
- Provide the patient's personal information, including their name and date of birth.
- Select one option for CPR orders, indicating whether to attempt resuscitation or not.
- Choose medical intervention preferences by selecting one of the approaches listed in Section B.
- Indicate preferences for artificial nutrition in Section C.
- Document who discussed the orders with the patient and the basis for these decisions in Section D.
- Ensure that the form is signed by the appropriate healthcare professional.
Does this document require notarization?
This form does not typically require notarization unless specified by local law.
Get your form ready online
Our built-in tools help you complete, sign, share, and store your documents in one place.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.
Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.
Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.

Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.

Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Typical mistakes to avoid
- Leaving sections blank, which may default to full treatment, contrary to the patientâs intentions.
- Failing to provide a copy of the POST when transferring or discharging the patient.
- Not ensuring that the form is properly signed and dated by a licensed health care professional.
- Neglecting to review and update the POST if the patientâs health status changes.
Why use this form online
- Convenience: Forms can be easily accessed and downloaded at any time.
- Editability: Users can fill in the forms digitally, reducing errors from handwritten texts.
- Reliability: Legal forms drafted by licensed attorneys ensure compliance with state laws.