Dispute Claim Form For Billing Insurance Carriers In Cook
Description

Get your form ready online
Our built-in tools help you complete, sign, share, and store your documents in one place.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.
Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.
Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
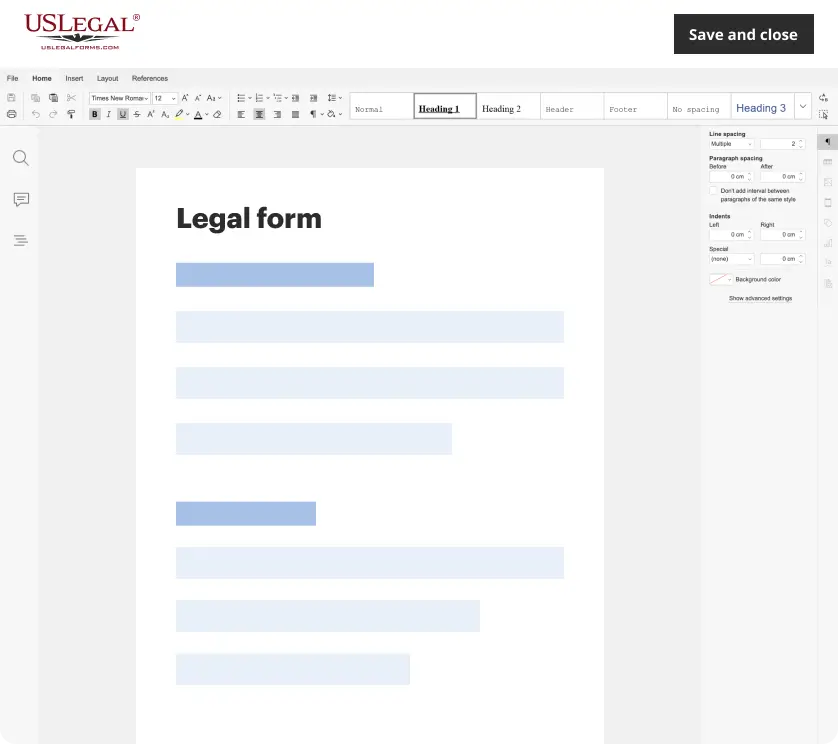
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.

Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.

Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Looking for another form?










Form popularity
FAQ
Example of a Denial of Coverage Letter Dear Policyholder's Name, We are writing to you regarding your recent claim submitted on Date with the claim number Claim Number. After a thorough review of your claim and policy, we regret to inform you that we are unable to approve your claim for Reason for Claim.
To Whom It May Concern: I am writing to request a review of your denial of the claim for treatment or services provided by name of provider on date provided. The reason for denial was listed as (reason listed for denial), but I have reviewed my policy and believe treatment or service should be covered.
To Whom It May Concern: I am writing to request a review of your denial of the claim for treatment or services provided by name of provider on date provided. The reason for denial was listed as (reason listed for denial), but I have reviewed my policy and believe treatment or service should be covered.
Things to Include in Your Appeal Letter Patient name, policy number, and policy holder name. Accurate contact information for patient and policy holder. Date of denial letter, specifics on what was denied, and cited reason for denial. Doctor or medical provider's name and contact information.
How to Write a Letter to a Health Insurance Company for a Claim? Identify Your Basic Information. Compose a Formal Greeting. Express the Purpose of Your Letter. Brief Description of Medical Treatment. Provide Details of the Costs Involvement. Attach Required Documents. Prompt Processing Request. Closing Statement.
5 TIPS FOR GETTING YOUR CLAIM ISSUES RESOLVED MORE QUICKLY Involve your agent at the beginning and throughout the life of your claim. When appropriate, and if possible, try to send emails. If phone contact is necessary, allow between 24 and 48 hours for a response.
Disputing a rejected or declined insurance claim Inform your insurance company in writing that you wish to dispute the decision and why. The insurance company is required to review the decision and inform you of any new decision or changes to their original decision.

