Accidental Injury Claim Form Aflac In Oakland
Description



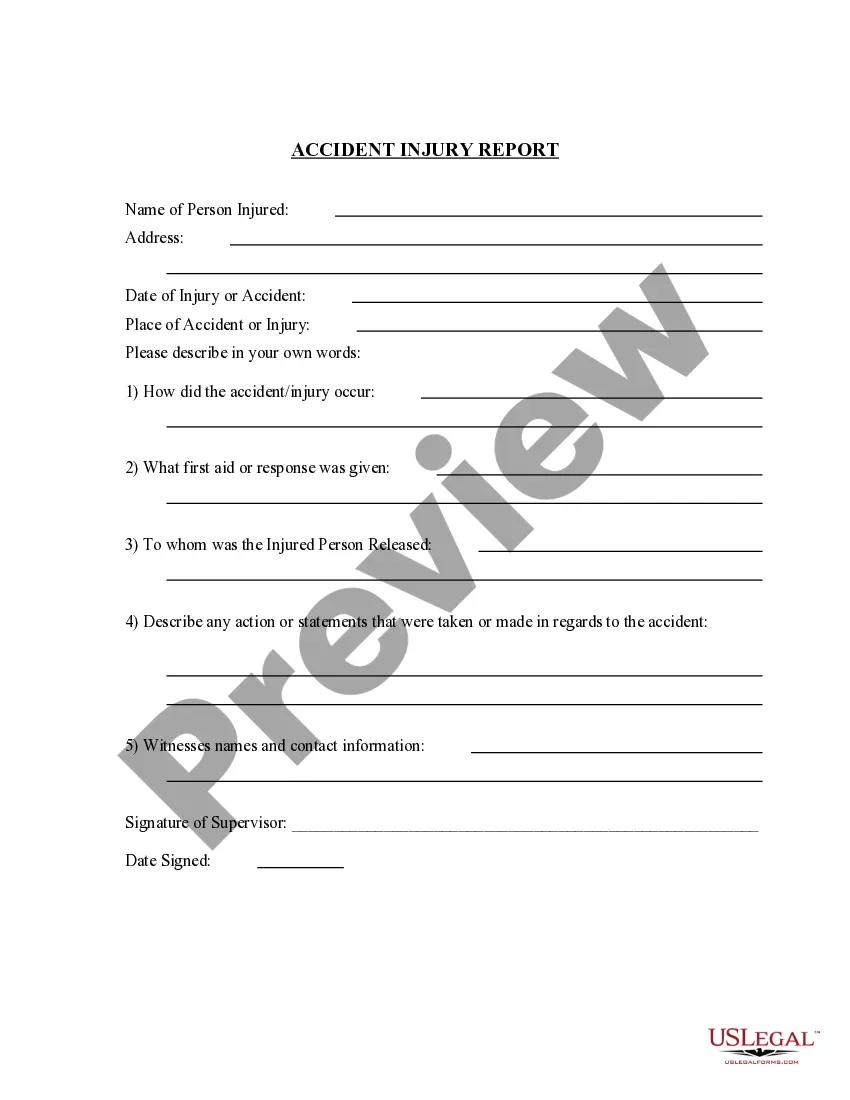
Get your form ready online
Our built-in tools help you complete, sign, share, and store your documents in one place.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.
Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.
Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.

Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.

Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Looking for another form?



Form popularity
FAQ
To file a claim, simply select the appropriate claim form for your specific product and mail or fax it to us at the address on the form. Download the form. Fill it out. Send it in to: PO Box 60676, Worcester, MA 01606.
Q. How long do I have to file a claim? A. There is a one-year timely filing provision in your certificate.
Claims for all other benefits covered under this policy must be filed separately using the claim forms available at aflac or by calling 1-800-99-AFLAC (1-800-992-3522).
Accident Claims Checklist. Z2201218R1. Identify your policy. Policyholder's address. What you need to file a claim. HCFA 1500 (non-hospital bill). ER report or operative report. (Please obtain the supporting documents for the corresponding benefit.) ... Proof of services. My Claims. MyAflac® helpful tips: ▪
POLICYHOLDER'S EMAIL ADDRESS. POLICYHOLDER'S MAJOR MEDICAL INSURANCE PROVIDER. MAJOR MEDICAL ID# ... POLICY NO. SOCIAL SECURITY NO. STREET. CHECK BOX IF THIS IS A PERMANENT ADDRESS CHANGE. ZIP CODE. PATIENT'S NAME (PERSON WHO IS SICK OR INJURED) DATE OF BIRTH GENDER POLICYHOLDER'S TELEPHONE NO. RELATIONSHIP TO POLICYHOLDER. Self.
Aflac will deny your claim if you do not meet your policy's terms and conditions. Review your policy to determine what Aflac expects of you as a policyholder and fulfill all obligations to be eligible for benefits.
Policy number. Policyholder's name. Policyholder's address. Approximate conception date for pregnancy. HCFA 1500 (non-hospital bill). Motor vehicle accident (MVA). Hospital confinement - IHB or UB04. Prior year's tax records - Needed if self-employed or the policy is less than 2 years old. My Claims.
POLICYHOLDER'S EMAIL ADDRESS. POLICYHOLDER'S MAJOR MEDICAL INSURANCE PROVIDER. MAJOR MEDICAL ID# ... POLICY NO. SOCIAL SECURITY NO. STREET. CHECK BOX IF THIS IS A PERMANENT ADDRESS CHANGE. ZIP CODE. PATIENT'S NAME (PERSON WHO IS SICK OR INJURED) DATE OF BIRTH GENDER POLICYHOLDER'S TELEPHONE NO. RELATIONSHIP TO POLICYHOLDER. Self.
Q. How long do I have to file a claim? A. There is a one-year timely filing provision in your certificate.
Q. How long do I have to file a claim? A. There is a one-year timely filing provision in your certificate.
