Release Of Information Form Colorado In Wake
Description


Get your form ready online
Our built-in tools help you complete, sign, share, and store your documents in one place.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.
Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.
Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Make edits, fill in missing information, and update formatting in US Legal Forms—just like you would in MS Word.

Download a copy, print it, send it by email, or mail it via USPS—whatever works best for your next step.

Sign and collect signatures with our SignNow integration. Send to multiple recipients, set reminders, and more. Go Premium to unlock E-Sign.
If this form requires notarization, complete it online through a secure video call—no need to meet a notary in person or wait for an appointment.
We protect your documents and personal data by following strict security and privacy standards.
Looking for another form?
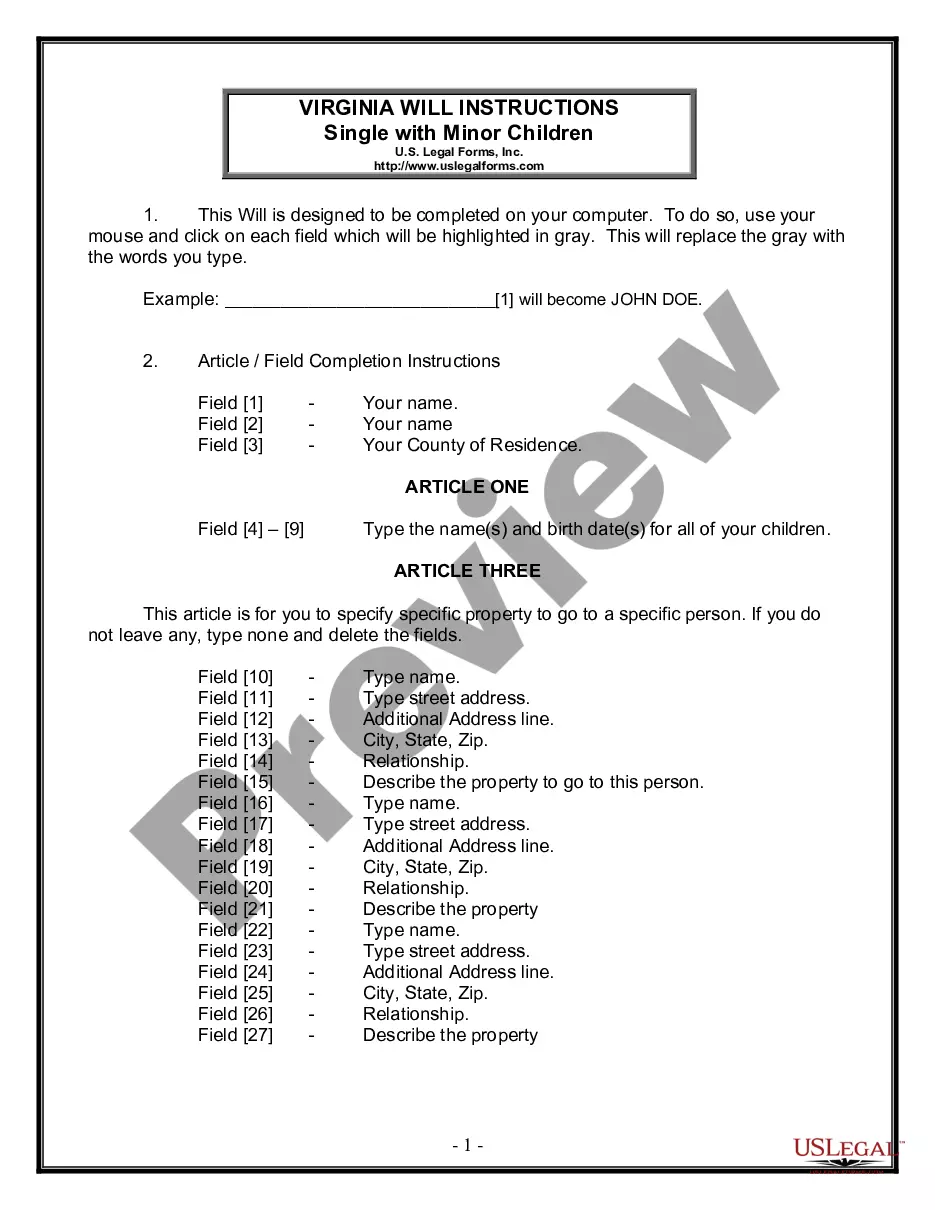









Form popularity
FAQ
: a politically organized body of people usually occupying a definite territory. especially : one that is sovereign. b. : the political organization of such a body of people.
Begin by specifying your name, the entity authorized to disclose information, and the individuals or entities you authorize to receive it. Indicate the specific information and purpose for which it will be disclosed, add an expiration date or event, and sign and date the form to confirm your consent.
Providers: The Medical Board of Colorado recommends retaining all patient records for a minimum of seven years after the last date of treatment.
Providers: The Medical Board of Colorado recommends retaining all patient records for a minimum of seven years after the last date of treatment.
If you are requesting your own health and/or behavioral health records or a designated representative is requesting on your behalf, the following will need to be provided: A valid authorization form that specifies what records are being requesting. A copy of your current, valid photo ID.
Authorization letters are written in order to authorize or approve someone on your behalf to perform an action that should have been done by you. You are allowed to authorize someone else to carry out the respective task on your behalf under certain unavoidable circumstances.
For legal professionals and healthcare providers, understanding the primary purpose of a Release of Information (ROI) form is vital for managing sensitive data responsibly.
This Disclosure Authorisation Letter (previously known as an “Authorisation to Release Confidential Information") refers to a Confidentiality Agreement and authorises a party to that agreement to release certain information to a named party. This document is suitable for basic disclosure situations only.
Authorization is the security process that determines a user or service's level of access. In technology, we use authorization to give users or services permission to access some data or perform a particular action.
Generally, an authorization provides the authority for a doctor's release of PHI for specified purposes, which are generally other than treatment, payment, or healthcare operations, or, to disclose protected health information to a third party specified by the individual.

