Loading
Get Nm Group Benefits Plan Disability Claim Physician Form 2018
How it works
-

Open form follow the instructions
-

Easily sign the form with your finger
-

Send filled & signed form or save
How to fill out the NM Group Benefits Plan Disability Claim Physician Form online
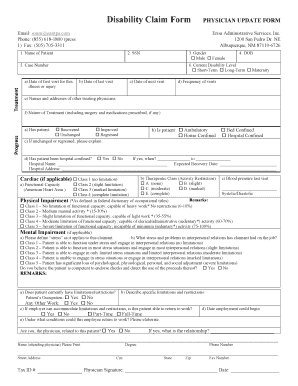
Filling out the NM Group Benefits Plan Disability Claim Physician Form online is a critical step in documenting a patient's claim for disability benefits. This guide provides clear and comprehensive instructions to ensure the form is completed accurately and efficiently.
Follow the steps to complete the form online with ease.
- Click ‘Get Form’ button to obtain the NM Group Benefits Plan Disability Claim Physician Form and open it in the editor.
- Begin filling out the patient’s information: Enter the patient’s name, social security number (SSN), date of birth (DOB), and select their gender. Ensure all details are accurate.
- Provide treatment information: Include the case number, current disability level (short-term, long-term, or maternity), and relevant dates for visits including the first, last, and next scheduled visit.
- Indicate the frequency of visits and supply the names and addresses of other treating physicians. Specify the nature of treatment, including any surgeries or medications prescribed.
- In the progress section, choose the patient’s current condition: recovered, improved, unchanged, or regressed. If unchanged or regressed, provide an explanation.
- Detail the patient’s hospitalization status: select whether the patient is ambulatory, house confined, bed confined, or hospital confined. If confined, fill in the hospital name, dates of hospitalization, and expected recovery date.
- Complete the cardiac classification section (if applicable) and provide blood pressure readings from the last visit.
- Address the physical and mental impairments: fill in the applicable classes and provide details on the patient’s functional capacity and mental stress capacity.
- Affirm whether the patient has limitations or restrictions in their occupation. Clearly describe the specific limitations and indicate if the employer can accommodate these restrictions.
- Conclude by specifying the conditions under which the patient could return to work, along with the expected start date of employment.
- Have the attending physician complete their information, including name, degree, phone number, address, tax ID, and fax number. The physician must sign and date the form.
- Review the completed form for accuracy. Save any changes, then download, print, or share the form as necessary.
Complete your NM Group Benefits Plan Disability Claim Physician Form online today.
Get form
Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Related links form
The State of New Mexico Disability has self-insured a supplemental income plan to provide financial assistance to those that lose income due to a sickness or injury and are unable to work for a period of time. The Disability plan is comprised of two benefits; Short Term Disability and Long Term Disability.
Get This Form Now!
Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.