Loading
Form preview
  • US Legal Forms
  • Other Templates
  • More Forms
  • More Multi-State Forms
  • Pr Triple-s Advantage Patients Request For Medical Payment

Get Pr Triple-s Advantage Patients Request For Medical Payment

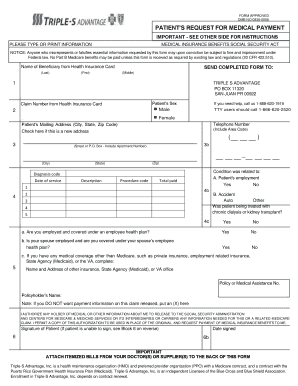
NOTICE: Anyone who misrepresents or falsifies essential information requested by this form may upon conviction be subject to fine and imprisonment under Federal law. No Part B Medicare benefits may be paid unless this form is received as required by existing law and regulations (20 CFR 422.510). SEND COMPLETED FORM TO: Name of Beneficiary from Health Insurance Card (Last) (First) (Middle) 1 TRIPLE S ADVANTAGE PO BOX 11320 SAN JUAN PR 00922 Patient s Sex Male Claim Number from Healt.

How it works

  1. Open form

    Open form follow the instructions

  2. Easily sign form

    Easily sign the form with your finger

  3. Share form

    Send filled & signed form or save

How to fill out the PR Triple-S Advantage Patients Request For Medical Payment online

This guide provides clear and concise instructions on filling out the PR Triple-S Advantage Patients Request For Medical Payment online. It is designed to assist users in navigating the form efficiently while ensuring that all necessary information is included.

Follow the steps to successfully complete your medical payment request.

  1. Click ‘Get Form’ button to obtain the form and open it in the editor.
  2. In Block 1, provide your name as it appears on your health insurance card, ensuring you include your last name, first name, and middle name.
  3. In Block 2, enter your Health Insurance Claim Number exactly as it is displayed on your Medicare card and select the appropriate box for the patient’s sex.
  4. In Block 3, input your mailing address. Include your street address, city, state, and zip code. Additionally, provide a telephone number in Block 3b.
  5. For Block 4, describe the condition related to your treatment. Indicate whether it was associated with employment or an accident and provide relevant diagnosis code and date of service where applicable.
  6. Block 5a requires you to confirm if you are employed and covered under an employee health plan, while Block 5b pertains to your spouse’s employment coverage. Complete Block 5c if you have any other medical coverage, ensuring to provide the necessary policy information.
  7. In Block 6, sign your name. If you are unable to sign, mark an (X) and have a witness sign as well. If you are filling out the form on behalf of another individual, indicate your relationship to them in this section.
  8. Finally, in Block 6b, indicate the date you are completing the form.
  9. Attach itemized bills from your healthcare provider that outline the services received along with any other supporting documentation to the back of the form.
  10. After reviewing all the information for accuracy, save the changes, then download or print the completed form for submission.

Complete your PR Triple-S Advantage Patients Request For Medical Payment document online today.

Get form

Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Get form

Related content

1490S-Patient's Request for Medical Payment
Simply circle his/her name on the bill. • Mark out any services on the itemized bill(s)...
Learn more
Medicare Benefit Policy Manual Chapter 15
Payment may not be made under Part B for services furnished an individual if the...
Learn more
Reimbursement of Paid Medical Expenses Under 18...
Attachment II: Sample Wording to Request a Claim Form. Attachment III: Claim Transmittal...
Learn more

Related links form

Gems Formulary 2020 Mga Kapahayagan Ng Langit At Impiyerno Sa 7 Kabataan Ng Agsimula Ang Lahat Sa Mga Bangus Ni Sonia Kumbukumbu

Questions & Answers

Get answers to your most pressing questions about US Legal Forms API.

Contact support

Your specific Medicare claims mailing address can be found on your Medicare Summary Notice (MSN). Your MSN is sent out every three months and details the Medicare services you've received, and how much Medicare has agreed to pay for them.

How do I file a claim? You can download and fill out a form, called the Patient Request for Medical Payment form (CMS-1490S). This form is also available in Spanish.

CMS 1490S: Patient's Request For Medical Payment. DEPARTMENT OF HEALTH AND HUMAN SERVICES. CENTERS FOR MEDICARE & MEDICAID SERVICES. Form Approved OMB.

The Form CMS-1450, also known as the UB-04, is the standard claim form to bill Medicare Administrative Contractors (MACs) when a paper claim is allowed.

The Health Insurance Claim Form (CMS-1500) is used by Allied Health professionals, physicians, laboratories and pharmacies to bill supplies and services to the Medi-Cal program.

CMS 1490S: Patient's Request For Medical Payment. DEPARTMENT OF HEALTH AND HUMAN SERVICES. CENTERS FOR MEDICARE & MEDICAID SERVICES. Form Approved OMB.

Get This Form Now!

Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
Get form
If you believe that this page should be taken down, please follow our DMCA take down processhere.
Get PR Triple-S Advantage Patients Request For Medical Payment
Get form
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
  • Real Estate Handbook
  • All Guides
  • Notarize
  • Incorporation services
  • For Consumers
  • For Small Business
  • For Attorneys
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Form Packages
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
Form Categories
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
Customer Service
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
Legal Guides
  • Real Estate Handbook
  • All Guides
Prepared for you
  • Notarize
  • Incorporation services
Our Customers
  • For Consumers
  • For Small Business
  • For Attorneys
Our Sites
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Social Media
Call us now toll free:
+1 833 426 79 33
As seen in:
© Copyright 1999-2026 airSlate Legal Forms, Inc. 17 Station Street, Ste. 203, Brookline, MA 02445
  • Your Privacy Choices
  • Terms of Service
  • Privacy Notice
  • Content Takedown Policy
  • Bug Bounty Program