Loading
Form preview
  • US Legal Forms
  • Other Templates
  • Industry Forms
  • Industry Insurance & Medical Forms
  • Woman's Hospital Authorization To Release Protected Health Information (phi) 2014

Get Woman's Hospital Authorization To Release Protected Health Information (phi) 2014-2026

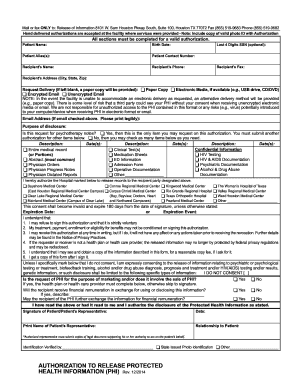
where services were provided - Note: Include copy of valid photo ID with Authorization All sections must be completed for a valid authorization. Patient Name: Birth Date: Patient Alias(s): Patient Contact Number: Recipient’s Name: Recipient’s Phone: Last 4 Digits SSN (optional): Recipient’s Fax: Recipient’s Address (City, State, Zip): Request Delivery (If left blank, a paper copy will be provided):  Paper Copy  Electronic Media, if available (e.g., USB drive, CD/DVD) .

How it works

  1. Open form

    Open form follow the instructions

  2. Easily sign form

    Easily sign the form with your finger

  3. Share form

    Send filled & signed form or save

How to fill out the Woman's Hospital authorization to release protected health information (PHI) online

Filling out the Woman's Hospital authorization to release protected health information form online is an essential step in ensuring that your medical records are shared appropriately and securely. This guide provides clear instructions on how to complete the form efficiently.

Follow the steps to fill out the authorization form correctly

  1. Click 'Get Form' button to obtain the authorization form and open it in your preferred document editor.
  2. Complete the patient information section by entering your name, birth date, any aliases, and your contact number. Ensure all fields are filled out for a valid authorization.
  3. Fill in the recipient's information. Provide the name, phone number, last four digits of the Social Security number (optional), fax number, and the complete address including city, state, and zip code.
  4. Indicate your preferred request delivery method by selecting one of the options: paper copy, electronic media, encrypted email, or unencrypted email. Note the risks associated with electronic formats.
  5. If you chose electronic delivery, include your email address legibly in the specified field.
  6. Specify the purpose of disclosure in the designated field and indicate whether the request pertains to psychotherapy notes. Check the appropriate boxes regarding the information to be disclosed.
  7. Select the medical records or documentation you wish to release by checking the corresponding boxes in the confidential information section.
  8. Indicate which facility is authorized to release records by selecting from the list provided.
  9. Provide an expiration date or event for the authorization unless you wish it to remain valid for 180 days from the date of signature.
  10. Read and acknowledge the information regarding the authorization, including your rights and the potential risks involved.
  11. Sign and date the form in the provided fields, and ensure to print your name and the relationship if you are signing on behalf of another person.
  12. Include information about identification verification, selecting an appropriate identification type if required.
  13. Once all sections are completed, save your changes and consider downloading a copy for your records. You can also choose to print or share the form as necessary.

Complete your authorization to release protected health information online today for quicker record sharing.

Get form

Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Get form

Related content

HIPAA Privacy Rule and Disclosures of Information...
Jun 18, 2025 — The Privacy Rule permissions for disclosing PHI without an individual's...
Learn more
Using & Disclosing Protected Health Information...
May 4, 2018 — HIPAA does not require a covered entity to get an individual to sign a...
Learn more
Payment Error Rate Measurement Manual
Oct 15, 2013 — Under PERM, States submit documentation that contains protected health...
Learn more

Related links form

Software For Form Pt 100 Nys Petroleum Tax Returns Hocking College Overage Checks Form Union Eye Care Reimbursement Form Rac Toolkit Form

Questions & Answers

Get answers to your most pressing questions about US Legal Forms API.

Contact support

When Can PHI Be Released without Authorization? The major exception to the need for specific authorization for the release of PHI is that medical care providers may release information to other providers and entities who are participating in the patient's care, and to business that provide services for those providers.

A Privacy Rule Authorization is an individual's signed permission to allow a covered entity to use or disclose the individual's protected health information (PHI) that is described in the Authorization for the purpose(s) and to the recipient(s) stated in the Authorization.

Authorization. A covered entity must obtain the individual's written authorization for any use or disclosure of protected health information that is not for treatment, payment or health care operations or otherwise permitted or required by the Privacy Rule.

A HIPAA authorization is a detailed document in which specific uses and disclosures of protected health are explained in full. By signing the authorization, an individual is giving consent to have their health information used or disclosed for the reasons stated on the authorization.

Emergency Treatment If you need emergency care, an ER doctor may need to request and view your medical records in order to make the best possible treatment decisions.

Should I sign this “HIPAA Authorization” for release of my medical records? No, you should not sign the HIPAA authorization for the release of your medical records. Often, the insurance company will act as though they cannot begin to decide how much money to offer you until they have all of your medical records.

The HIPAA Privacy Rule expressly requires an authorization for uses or disclosures of protected health information for ALL marketing communications, except in two circumstances: When the communication occurs in a face-to-face encounter between the covered entity and the individual; or.

I hereby authorize use or disclosure of protected health information about me as described below. I understand that the information used or disclosed may be subject to re-disclosure by the person or class of persons or facility receiving it, and would then no longer be protected by federal privacy regulations.

Get This Form Now!

Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
Get form
If you believe that this page should be taken down, please follow our DMCA take down processhere.
Get Woman's Hospital Authorization to Release Protected Health Information (PHI)
Get form
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
  • Real Estate Handbook
  • All Guides
  • Notarize
  • Incorporation services
  • For Consumers
  • For Small Business
  • For Attorneys
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Form Packages
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
Form Categories
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
Customer Service
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
Legal Guides
  • Real Estate Handbook
  • All Guides
Prepared for you
  • Notarize
  • Incorporation services
Our Customers
  • For Consumers
  • For Small Business
  • For Attorneys
Our Sites
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Social Media
Call us now toll free:
+1 833 426 79 33
As seen in:
© Copyright 1999-2026 airSlate Legal Forms, Inc. 17 Station Street, Ste. 203, Brookline, MA 02445
  • Your Privacy Choices
  • Terms of Service
  • Privacy Notice
  • Content Takedown Policy
  • Bug Bounty Program