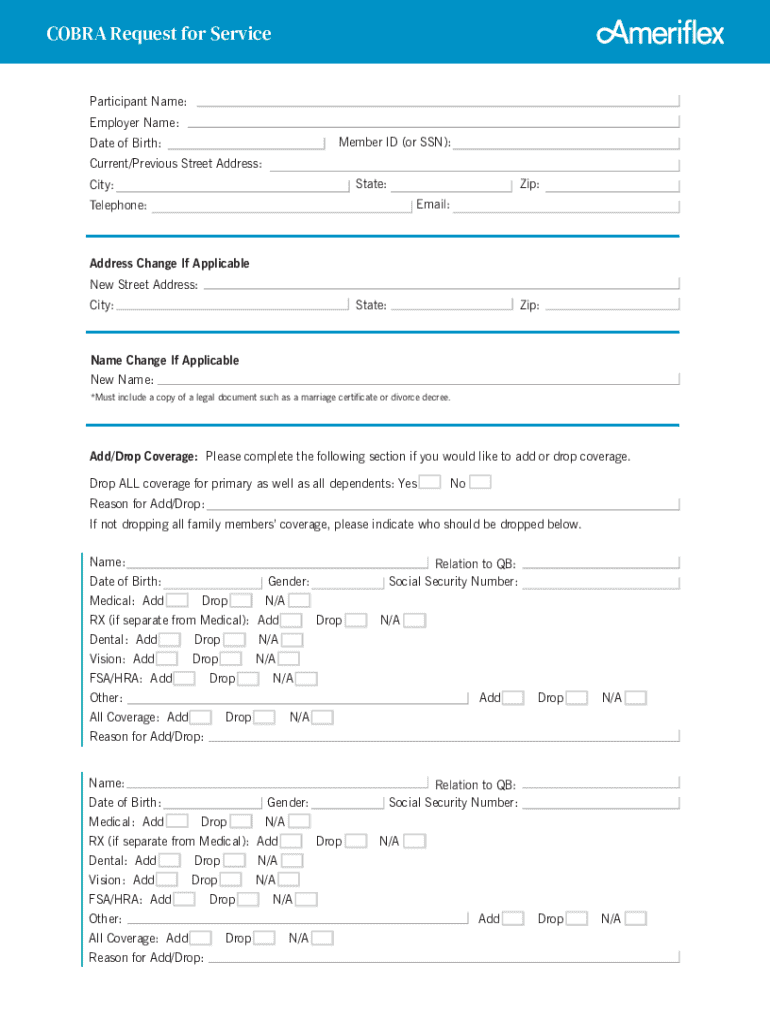
ADDRESS CHANGE IF APPLICABLE. New Address: City: State: Zip: Add/Drop Dependent (Check One): Add* Drop. Dependent Name: Dependent D.O.B.:.
Loading

Open form follow the instructions

Easily sign the form with your finger

Send filled & signed form or save
How to fill out the Ameriflex COBRA Request For Service online
Filling out the Ameriflex COBRA Request For Service online is an essential step in managing your COBRA benefits. This guide will provide you with a clear, step-by-step process to ensure you complete the form accurately and efficiently.
Follow the steps to complete your Ameriflex COBRA Request for Service form.
- Click ‘Get Form’ button to obtain the Ameriflex COBRA Request for Service form online.
- Provide your participant name and employer name in the designated fields. Ensure that your Member ID or Social Security Number is accurately recorded for identification purposes.
- Enter your date of birth and current or previous street address, including the state, city, and zip code for accurate correspondence.
- Fill out your email address and telephone number to ensure you can be contacted regarding your request.
- If applicable, indicate any address changes by completing the new street address, city, state, and zip fields.
- If there has been a name change, please provide the new name and include a copy of a legal document, such as a marriage certificate or divorce decree.
- To add or drop coverage, complete the appropriate section. If dropping all coverage for yourself and dependents, indicate 'Yes' or 'No' and provide the reason for the change.
- If you are not dropping coverage for all dependents, specify who should be dropped by providing their name, date of birth, gender, and the types of coverage to add or drop (Medical, RX, Dental, Vision, FSA/HRA, etc.).
- If you need to add or drop more than three family members, complete a second COBRA Request for Service form.
- If you're adding a newborn, ensure to attach a copy of the crib card or documentation from the hospital including the baby's name, date of birth, height, and weight.
- Indicate whether you are providing Medicare eligibility documentation, and ensure to include a photocopy of the Medicare ID card if applicable.
- If requesting a disability extension, mark 'Yes' and attach the photocopy of the Award Letter from the Social Security Administration.
- Fill in the effective date of your requested changes in the relevant field.
- Sign the form where indicated and provide the date of signing.
- Submit your completed form by email to service@myameriflex.com.
Complete your Ameriflex COBRA Request For Service form online to manage your health benefits today.
Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Related content
Dec 31, 2019 — It would be our privilege to be selected to provide Contractual Services...
For purposes of pre-taxing COBRA coverage for , certain Employees may be able to continue...
Note: The original Monthly Operating Report is to be filed with the court and a copy...
Get answers to your most pressing questions about US Legal Forms API.
How to apply for COBRA in California?
Applying for COBRA begins with the employer who provided the health plan to notify you of your right to continuation. The employer has 30 days to notify the group health plan of the qualifying event. After that, the employer has 14 days to notify you of your COBRA right to keep your work health insurance.
Am I eligible for COBRA if I have an FSA?
COBRA only applies to FSAs which are said to be underspent. * This means that the amount available for reimbursement for the remainder of the plan year exceeds the COBRA premium for that same time period. Figuring out if the FSA is underspent involves a bit of math, so it's best illustrated with an example.
How to cancel Ameriflex COBRA?
To cancel COBRA: Download and fill out our COBRA Request for Service Form. When filling out the form, indicate that you would like to Drop Coverage for the primary account holder as well as dependents, or use the appropriate fields to indicate the specific family members for who you would like to cancel coverage.
How do I cancel my cobra?
There are three ways to do so: Terminate coverage on your online account. For instructions, see How to terminate coverage in your COBRA online account. Submit a completed COBRA Benefits Termination Form. Do not remit the premium payment for the month you no longer want coverage.
Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
If you believe that this page should be taken down, please follow our DMCA take down process here.