Loading
Form preview
  • US Legal Forms
  • Other Templates
  • More Forms
  • More Multi-State Forms
  • Wellcare Direct Member Reimbursement Form 2009

Get Wellcare Direct Member Reimbursement Form 2009-2026

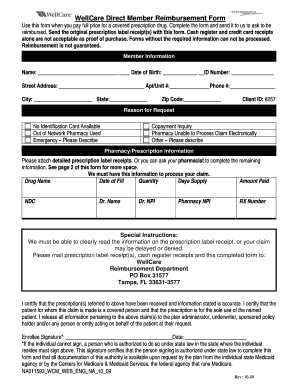
NPI Pharmacy NPI RX Number If you need help with this form, please call us. Call the Customer Service phone number listed on the back of your membership card. NA011593 WCM WEB ENG NA 10 09 Rev: 10-09.

How it works

  1. Open form

    Open form follow the instructions

  2. Easily sign form

    Easily sign the form with your finger

  3. Share form

    Send filled & signed form or save

How to fill out the WellCare Direct Member Reimbursement Form online

Filling out the WellCare Direct Member Reimbursement Form online can be straightforward if you understand the necessary components and process. This guide will walk you through each section of the form to ensure your reimbursement request is accurately submitted.

Follow the steps to complete the form effectively.

  1. Press ‘Get Form’ button to access the WellCare Direct Member Reimbursement Form and open it in your preferred editing tool.
  2. Begin by providing your member information in the designated fields. Include your full name, date of birth, ID number, street address, apartment or unit number (if applicable), phone number, city, state, and zip code.
  3. In the 'Reason for Request' section, select one of the options that best explains your reimbursement request. Options include 'No Identification Card Available', 'Out of Network Pharmacy Used', 'Emergency', 'Copayment Inquiry', or 'Other'. If your reason falls under 'Emergency' or 'Other', be sure to describe it clearly.
  4. Next, fill out the 'Pharmacy/Prescription Information' section. You will need to attach detailed prescription label receipts. If any details are missing, contact your pharmacist for assistance. Fill in the following fields: Drug Name, Date of Fill, Quantity, Days Supply, Amount Paid, NDC, Doctor's Name, Doctor's NPI, Pharmacy NPI, and RX Number.
  5. Ensure that the information on the prescription label receipts is clear and legible, as this is crucial for processing your claim.
  6. After completing the form, read the certification statement carefully. By signing, you affirm that the information provided is accurate and that the prescription is for the intended patient.
  7. Once all sections are completed, ensure that you have included the original prescription label receipts, as well as any additional documentation if required. Mail the completed form and receipts to WellCare at the address provided on the form.
  8. Finally, consider saving changes, downloading a copy, printing the form for your records, or sharing it with relevant parties if necessary.

Get started on your WellCare Direct Member Reimbursement Form now!

Get form

Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Get form

Related content

medicaid provider manual - WellCare
Mar 27, 2019 — Non-Participating Provider Reimbursement . ... WellCare in the form of...
Learn more
WellCare-Quick-Reference-Guide-Claims-Submissions-1-29...
December 2018 www.wellcare.com/Florida/Providers/Medicaid. ENCE GUIDE ... 1-866-698-5437...
Learn more
Provider Manual - Health First Network
12 to 18 Month Child Health Check-Up Tracking Form 36. 18 Month to 3 Year ... Prestige...
Learn more

Related links form

Mailing Address Change Form - Lackawanna County - Lackawannacounty Lackawanna County Cover Sheet Form Form OC-07 - Rev. 10-13-06 - Notice Of Claim.pdf - Lackawannacounty Lackawanna County Tax Appeal Forms

Questions & Answers

Get answers to your most pressing questions about US Legal Forms API.

Contact support

What is a Direct Member Reimbursement? A Direct Member Reimbursement (DMR) is when you ask us to pay you back for prescription drugs you paid for out-of-pocket. When can I submit a request for reimbursement? If you pay out-of-pocket for a prescription that is covered by your plan, you can submit a.

All together now. In Texas, WellCare and WellCare Texan Plus and Superior HealthPlan are bringing our health plans together to better serve you.

Claim payment disputes must be submitted in writing to WellCare within 90 calendar days of the date on the EOP.

Only WellCare submissions are free of charge. Please ensure you use vendor code 212750 when you register.

If you need assistance in making a connection with Availity or have any questions, please contact Availity client services at 1-800-282-4548. Providers should submit Fee For Service claims to Wellcare Payer ID 14163.

Providers must use the WellCare payer id 14163 if choosing to use Connect Center free DDE or batch upload services. WellCare encourages electronic (EDI) claim submissions. However, WellCare also accepts paper CMS-1500 and UB-04 claim forms.

Get This Form Now!

Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
Get form
If you believe that this page should be taken down, please follow our DMCA take down processhere.
Get WellCare Direct Member Reimbursement Form
Get form
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
  • Real Estate Handbook
  • All Guides
  • Notarize
  • Incorporation services
  • For Consumers
  • For Small Business
  • For Attorneys
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Form Packages
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
Form Categories
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
Customer Service
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
Legal Guides
  • Real Estate Handbook
  • All Guides
Prepared for you
  • Notarize
  • Incorporation services
Our Customers
  • For Consumers
  • For Small Business
  • For Attorneys
Our Sites
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Social Media
Call us now toll free:
+1 833 426 79 33
As seen in:
© Copyright 1999-2026 airSlate Legal Forms, Inc. 17 Station Street, Ste. 203, Brookline, MA 02445
  • Your Privacy Choices
  • Terms of Service
  • Privacy Notice
  • Content Takedown Policy
  • Bug Bounty Program