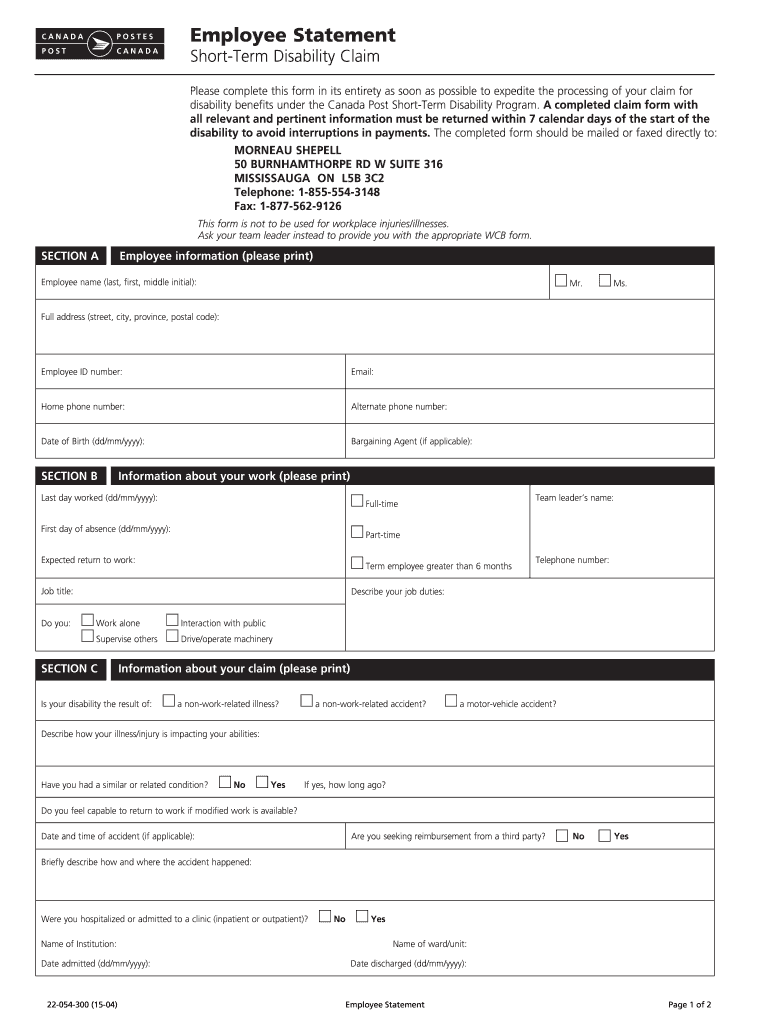
T-Term Disability Program. A completed claim form with all relevant and pertinent information must be returned within 7 calendar days of the start of the disability to avoid interruptions in payments. The completed form should be mailed or faxed directly to: MORNEAU SHEPELL 50 BURNHAMTHORPE RD W SUITE 316 MISSISSAUGA ON L5B 3C2 Telephone: 1-855-554-3148 Fax: 1-877-562-9126 This form is not to be used for workplace injuries/illnesses. Ask your team leader instead to provide you with the appropria.
Loading

Open form follow the instructions

Easily sign the form with your finger

Send filled & signed form or save
How to fill out the Canada 22-054-300 online
This guide provides step-by-step instructions for filling out the Canada 22-054-300 form online, ensuring a smooth submission process for your short-term disability claim. By following these instructions, you can efficiently complete the form and expedite your claim processing.
Follow the steps to complete your disability claim form online.
- Press the ‘Get Form’ button to access the Canada 22-054-300 online form.
- In Section A, enter your personal information. This includes your full name, address, employee ID number, email, home phone number, alternate phone number, date of birth, and, if applicable, your bargaining agent.
- Proceed to Section B to provide information about your work. Fill in details such as your last day worked, first day of absence, job title, expected return date, and whether you work full-time or part-time.
- Navigate to Section C, where you will state the nature of your disability, how it affects your abilities, and if a similar condition occurred previously. Provide details about the incident, if applicable, and whether you have been hospitalized.
- In Section D, fill out your income or benefit information. Indicate any employment insurance, worker's compensation, or other benefits you are receiving, including the start and end dates and the corresponding amounts.
- Complete Section E by entering details about your primary physician or healthcare professional. Include their name, specialty, treatment start date, contact information, and confirm if you are following the recommended treatment.
- Review your form for accuracy and completeness. Confirm that you have provided true information as given and authorize the necessary information exchange.
- After ensuring all sections are filled correctly, save your changes, and download or print the completed form for your records. Ensure to submit it to the appropriate address as instructed.
Start your claim submission process by completing the Canada 22-054-300 online today.
Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
If you believe that this page should be taken down, please follow our DMCA take down process here.
This form is available in several versions. Select the version you need from the drop-down list below.