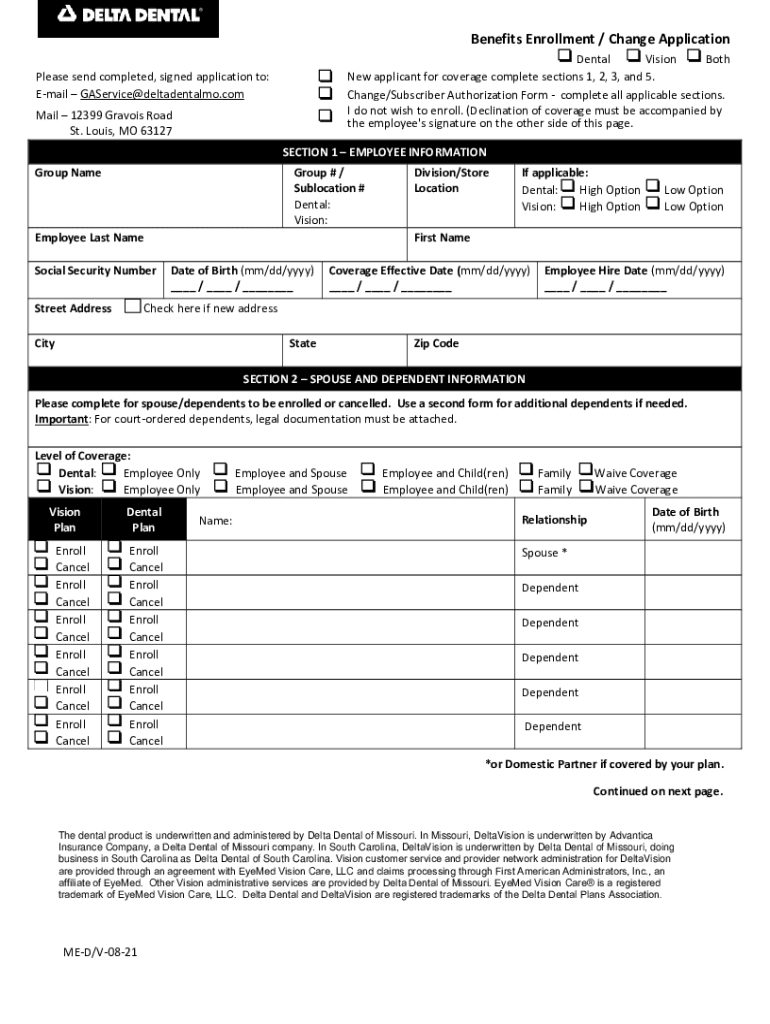
Benefits Enrollment / Change Application Dental Vision Both New applicant for coverage complete sections 1, 2, 3, and 5. Change/Subscriber Authorization Form complete all applicable sections.
Loading

Open form follow the instructions

Easily sign the form with your finger

Send filled & signed form or save
How to fill out the MO Delta Dental Benefits Enrollment/Change Application online
Completing your MO Delta Dental Benefits Enrollment/Change Application online is a straightforward process. This guide will walk you through each section of the form, ensuring that you have all the necessary information to successfully submit your application.
Follow the steps to accurately complete your application.
- Click ‘Get Form’ button to access the form and open it in the editor.
- Begin with Section 1, where you will enter your employee information, including your name, social security number, and date of birth. Ensure that you complete all required fields before moving on.
- In Section 2, fill out the spouse and dependent information. Include names, relationships, and dates of birth, and indicate whether you are enrolling or cancelling coverage for each dependent.
- Proceed to Section 3 to answer questions regarding coordination of benefits. This involves confirming whether your spouse has other group coverage and providing any necessary details.
- Move to Section 4 for any change of coverage information. Specify if you are adding or cancelling coverage and provide effective dates and reasons for the changes.
- Conclude with Section 5, where you must provide your authorization by signing and dating the form. Ensure all information is accurate as no action can be taken without your signature.
- Finally, save your changes and choose to download, print, or share the form as needed. Ensure that you send the completed and signed application to the appropriate email or mailing address provided.
Complete your MO Delta Dental Benefits Enrollment/Change Application online today to secure your benefits.
Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Related content
change of information form. Dual Dental (1 – 99). Dental coverage. Dental plans in...
New Application for Coverage. I do not wish to enroll. Complete Section 1, 2, and 4. COBRA...
However, you must request enrollment within 30 days after your or your dependents' other...
Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
If you believe that this page should be taken down, please follow our DMCA take down process here.