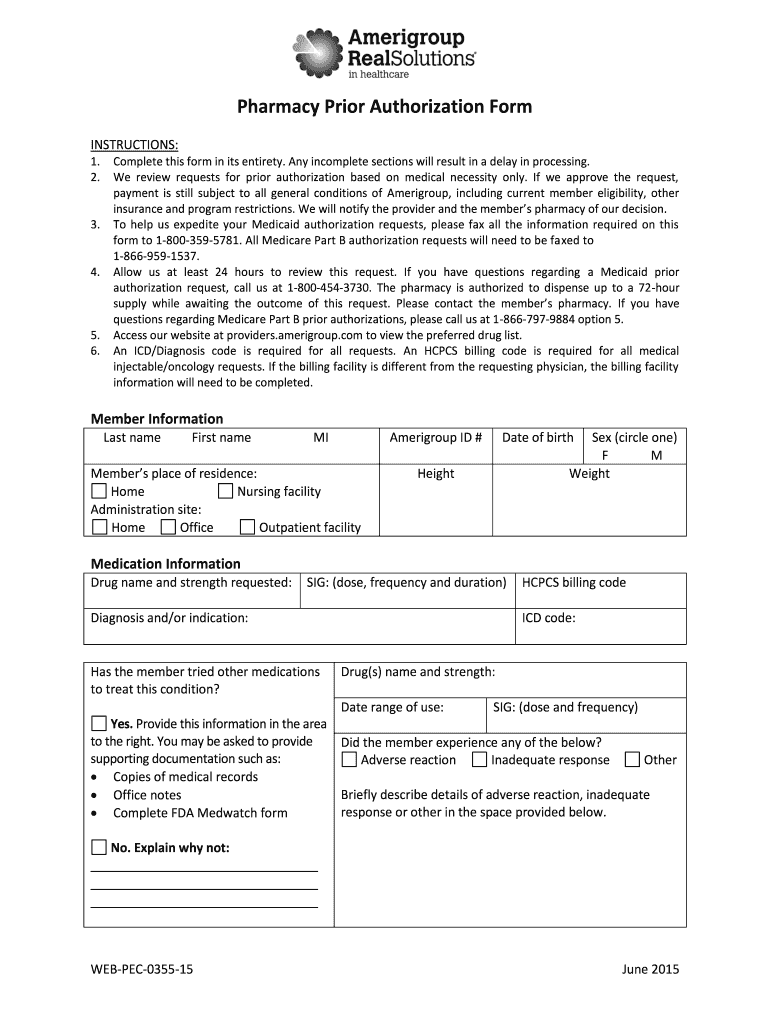
City Telephone number ( ) DEA/License # State Fax number Office contact name Pharmacy Information Name Pharmacy NPI # Telephone number ( ) Fax Number ( ) Signature I certify that the information provided is accurate and complete to the best of my knowledge, and I understand that any falsification, omission or concealment of material may be subject to c.

Open form follow the instructions

Easily sign the form with your finger

Send filled & signed form or save
How to fill out the Amerigroup Pharmacy Prior Authorization Form online
Filling out the Amerigroup Pharmacy Prior Authorization Form online is essential for ensuring timely processing of medication requests. This guide provides step-by-step instructions to help users accurately complete the form, thus facilitating smoother communication with Amerigroup.
Follow the steps to complete the Amerigroup Pharmacy Prior Authorization Form online
- Click ‘Get Form’ button to obtain the form and open it in the editor.
- Begin by filling out the member information section. Include the member’s last name, first name, middle initial, Amerigroup ID number, date of birth, height, weight, and their place of residence. Select from options such as ‘Home,’ ‘Nursing Facility,’ or others as applicable.
- Next, provide medication information. Enter the drug name and strength requested, along with dosing instructions (SIG) detailing dose, frequency, and duration. Include the HCPCS billing code as required.
- Document the diagnosis or indication for the medication. An ICD code is mandatory for all requests. If the member has tried other medications, specify the names and strengths, along with the date ranges of use.
- Answer whether the member experienced any adverse reactions or inadequate responses to previous medications. If yes, briefly describe the details in the provided area and include any necessary supporting documentation.
- Detail the medical necessity for using nonpreferred medications or prescribing outside of FDA labeling, if applicable. This should include a list of all current medications along with their doses and frequencies.
- Complete the section for diagnostic studies and laboratory tests performed within the past 30 days relevant to the medication requested. Provide detailed information about tests, dates, and results.
- Fill in prescriber information, including last name, first name, NPI number, address, contact details, and DEA/license number.
- If applicable, complete the billing facility information. Include the name, address, NPI/Tax ID, and contact details.
- Provide the pharmacy information, including the pharmacy name, NPI number, and contact details.
- Finally, review all entries for accuracy and completeness. The prescriber or authorized representative must sign and date the form to certify that the information is true and complete.
- Once completed, you may save changes, download, print, or share the form as necessary.
Begin filling out your Amerigroup Pharmacy Prior Authorization Form online today to ensure your requests are processed efficiently.
Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Related content
Bayou Health Pharmacy Prior Authorization Form. □ Amerigroup ①. LA Healthcare...
Team to assist with insurance benefits investigation prior authorization and patient...
Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
If you believe that this page should be taken down, please follow our DMCA take down process here.
This form is available in several versions. Select the version you need from the drop-down list below.