Loading
Form preview
  • US Legal Forms
  • Other Templates
  • Industry Forms
  • Industry Insurance & Medical Forms
  • Bright Health Member Claim Form

Get Bright Health Member Claim Form

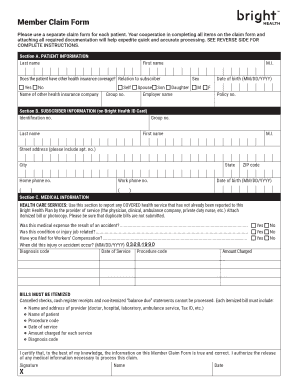
Accurate processing. SEE REVERSE SIDE FOR COMPLETE INSTRUCTIONS. Section A. PATIENT INFORMATION Last name First name Does the patient have other health insurance coverage? Relation to subscriber Yes No Name of other health insurance company Self Group no. Spouse Son Daughter Employer name M.I. Sex M Date of birth (MM/DD/YYYY) F Policy no. Section B. SUBSCRIBER INFORMATION (on Bright Health ID Card) Identi cation no. Group no. Last name First name M.I. Street address (please include.

How it works

  1. Open form

    Open form follow the instructions

  2. Easily sign form

    Easily sign the form with your finger

  3. Share form

    Send filled & signed form or save

How to fill out the Bright Health Member Claim Form online

This guide provides clear and practical steps for completing the Bright Health Member Claim Form online. By following these instructions, users can ensure a smooth submission process for their claims.

Follow the steps to successfully fill out the Member Claim Form.

  1. Press the ‘Get Form’ button to access the Bright Health Member Claim Form and open it in your preferred editor.
  2. In Section A, provide the patient information. Fill in the last name, first name, and middle initial. Indicate if the patient has any other health insurance by selecting 'Yes' or 'No,' and list the name of the other health insurance company if applicable.
  3. Continue in Section A by specifying the relation to the subscriber, selecting from options such as 'Self,' 'Spouse,' 'Son,' or 'Daughter.' Include the patient’s date of birth and sex, and provide the policy number and group number.
  4. In Section B, fill out the subscriber information using the details found on the Bright Health ID card. Include the identification number, group number, last name, first name, middle initial, and complete street address with apartment number if needed.
  5. Next, provide the city, state, and ZIP code for the subscriber. Ensure to include both home and work phone numbers.
  6. Move to Section C to report medical information. Indicate whether the health care services received have been reported already and attach itemized bills. Specify if any of the medical expenses were the result of an accident or job-related injury.
  7. Document the date when the injury or accident occurred, along with the diagnosis code, date of service, procedure code, and amount charged. Remember to itemize bills and ensure all required information is provided.
  8. Lastly, complete the certification section. Sign and date the form, affirming that the information provided is true and correct.
  9. Once all sections are filled out completely, users can save their changes, download, print, or share the form as needed before submission.

Complete your claim form online to ensure efficient processing of your health care services.

Get form

Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Get form

Related content

bright health insurance company of alabama, inc.
Dec 31, 2018 — Closed without Payment/ Denied Claims. ... I have the authority to...
Learn more
Member Claim Form
HEALTH CARE SERVICES: Use this section to report any COVERED health service that has not...
Learn more
ProviderManual_KY.pdf - Molina Healthcare
Members regarding Member Claims, benefits, eligibility/identification, ... at (800)...
Learn more

Related links form

WA T-Clocs Motorcycle Inspection Form WA TD-420-001 2016 WA TD-420-047 2011 WA TD-420-549 2014

Questions & Answers

Get answers to your most pressing questions about US Legal Forms API.

Contact support

A: Once contracted, facilities must complete the Facility Credentialing Application in order to become credentialed and begin seeing Bright HealthCare members. Download the application and submit the fully completed application. The credentialing process may take 60-90 days once your application is received.

Integrated ERA/EFT Payer List Payer NamePayer IDBright HealthCareBRGHTBrown & Toland Brown & Toland Physicians PPO94316 BTSS1CalOptimaCALOPClarion Health3545661 more rows

How to find your 1095-A online Log in to your HealthCare.gov account. Under "Your Existing Applications," select your 2022 application — not your 2023 application. Select “Tax Forms” from the menu on the left. Download all 1095-As shown on the screen.

Claims for Covered Health Services from a Non-Network or Non-Participating Provider must be submitted to Us within one year (365 days) from the date of service.

All the listed documents should be original: Claim application Form - Duly filled and signed. Doctors' prescription. Treatment papers. investigation/diagnostic reports/X-Ray. Original medical bills and scripts. Invoice for medicines. Hospital discharge card. Copy of FIR in case of an accidental emergency.

Get This Form Now!

Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
Get form
If you believe that this page should be taken down, please follow our DMCA take down processhere.
Get Bright Health Member Claim Form
Get form
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
  • Real Estate Handbook
  • All Guides
  • Notarize
  • Incorporation services
  • For Consumers
  • For Small Business
  • For Attorneys
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Form Packages
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
Form Categories
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
Customer Service
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
Legal Guides
  • Real Estate Handbook
  • All Guides
Prepared for you
  • Notarize
  • Incorporation services
Our Customers
  • For Consumers
  • For Small Business
  • For Attorneys
Our Sites
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Social Media
Call us now toll free:
+1 833 426 79 33
As seen in:
© Copyright 1999-2026 airSlate Legal Forms, Inc. 17 Station Street, Ste. 203, Brookline, MA 02445
  • Your Privacy Choices
  • Terms of Service
  • Privacy Notice
  • Content Takedown Policy
  • Bug Bounty Program