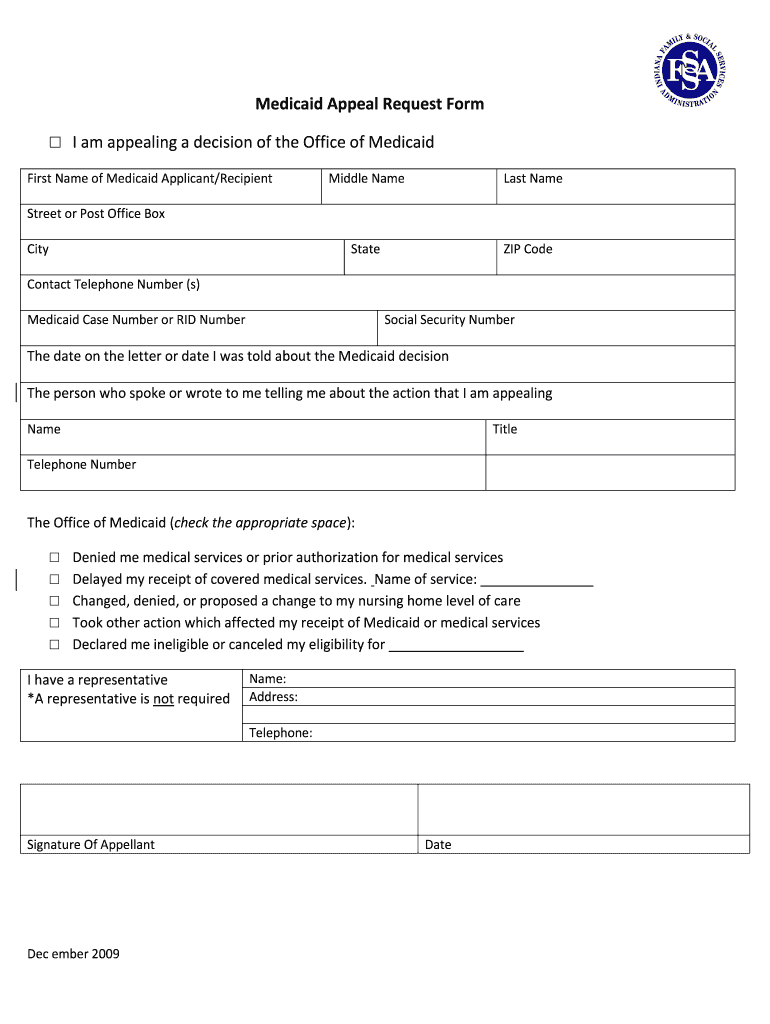
Medicaid Appeal Request Form I am appealing a decision of the Office of Medicaid First Name of Medicaid Applicant/Recipient Street or Post Office Box City Contact Telephone Number (s) Medicaid Case.

Open form follow the instructions

Easily sign the form with your finger

Send filled & signed form or save
How to fill out the IN Medicaid Appeal Request Form online
This guide provides a step-by-step process for filling out the IN Medicaid Appeal Request Form online. It aims to assist users in navigating the form efficiently, ensuring that all necessary information is accurately provided.
Follow the steps to complete your appeal request form online:
- Click ‘Get Form’ button to access the form and open it for completion.
- Fill in the first section with the applicant's or recipient's information. This includes their first name, middle name, last name, address, city, state, zip code, contact telephone numbers, Medicaid case number or RID number, and social security number.
- Enter the date you received the decision letter or were informed about the Medicaid decision, and provide the name, title, and telephone number of the person who communicated this information.
- Indicate the specific action you are appealing by checking the appropriate box. Options include denial of medical services, delays in receiving services, changes to nursing home care, or cancellations of Medicaid eligibility.
- If applicable, provide information about your representative, including their name, address, and telephone number. Note that having a representative is not required.
- Sign the form where indicated, and ensure to include the date of your signature. If unable to sign, provide an explanation of why you are the appropriate representative, along with any necessary supporting documents like a Power of Attorney.
- Review the entire form for accuracy and completeness before submission.
- Once completed, save the changes to the form and proceed to download or print it for mailing.
- Mail the completed form to the Appeals and Hearings Section at the specified address. Ensure it is postmarked within 30 days of the agency's action.
Complete your IN Medicaid Appeal Request Form online today to ensure your appeal is processed promptly.
Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Related content
Please make sure your name, the reason for the appeal request and the dates of the action...
I am writing, on behalf of [name of plan member if other than yourself], to appeal the...
Oct 8, 2024 — Contact the eMedNY Call Center with questions concerning: ➢ ePACES...
Get answers to your most pressing questions about US Legal Forms API.
What percentage of Medicare appeals are successful?
Research indicates that approximately 30 percent of Medicare appeals are successful. This success rate can depend on various factors, including the nature of the appeal and the quality of the submitted evidence. To enhance your chance for a favorable outcome, ensure you provide comprehensive documentation with the IN Medicaid Appeal Request Form. A clear presentation of your case can significantly influence the decision of the reviewing party.
What is the timely filing limit for Medicaid appeal in Oregon?
In Oregon, the timely filing limit for a Medicaid appeal generally falls within 90 days from the date you receive the notice of denial. It is essential to adhere to this timeline to ensure your appeal is considered. If you need assistance navigating this process, consider referencing the IN Medicaid Appeal Request Form for guidance. Be proactive in submitting your appeal to avoid missing this important deadline.
How long after being denied Medicaid can you reapply?
Typically, you can reapply for Medicaid immediately after a denial. However, it is crucial to understand the reasons for the original denial before reapplying. Address any issues raised in your denial to enhance your chances for approval. Using the IN Medicaid Appeal Request Form can also demonstrate your intent to appeal the previous decision.
How to file a Medicaid appeal?
To file a Medicaid appeal, start by obtaining the correct IN Medicaid Appeal Request Form from your state’s Medicaid office or through reliable platforms like uslegalforms. Fill out the form with detailed information about the denial and any supporting documents. Submit your appeal to the appropriate agency within the required timeframe to ensure it is processed efficiently. Follow up to confirm receipt and inquire about the status of your appeal.
What are the 5 steps of the Medicare appeal process?
The Medicare appeal process consists of five key steps: first, review the denial notice and understand the reasons for the denial. Next, gather all necessary documents and complete the appeal form, specifically the IN Medicaid Appeal Request Form. Third, submit your appeal within the specified time frame. Fourth, wait for a decision, which usually comes within 60 days. Lastly, if denied again, you may pursue further appeal options, which could include requesting a hearing.
How to fill out a Medicare appeal form?
Filling out a Medicare appeal form involves gathering all necessary information, including details about your previous claim and the reason for the denial. Follow the guidelines carefully on the form to ensure all required sections are completed. Use the IN Medicaid Appeal Request Form as a reference to ensure accuracy and thoroughness. Once completed, review your submission to confirm all information is correct before sending it.
What is a good cause for Medicare appeal?
A good cause for a Medicare appeal includes situations like receiving a late notice, misunderstanding the process, or experiencing serious illness that affected your ability to respond. Ensure to clearly articulate these reasons within the IN Medicaid Appeal Request Form. Providing relevant supporting documents can strengthen your case. Demonstrating good cause can significantly improve your chances of a successful appeal.
How do I fill out an appeal form?
To fill out an appeal form, first ensure you have all necessary documentation, including your original claim and denial letter. Carefully read the instructions provided with the IN Medicaid Appeal Request Form to understand the requirements. Provide thorough and accurate information, being specific about your reasons for the appeal. Finally, double-check your form for completeness before submitting.
What is a good cause for a Medicare appeal?
A good cause for a Medicare appeal may include situations where a claim was denied due to errors in filing or misunderstanding of coverage criteria. Additional circumstances like missed deadlines for documentation, or changes in medical status, can also provide valid reasons. Be sure to highlight these points in your IN Medicaid Appeal Request Form to strengthen your case.
How do I write an appeal letter for medical assistance?
When writing an appeal letter for medical assistance, begin with your personal details and the specifics of your situation. Clearly state your case, referencing the IN Medicaid Appeal Request Form, and explain why you believe the original decision was incorrect. Including additional documentation, if necessary, can support your points and strengthen your appeal.
Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
If you believe that this page should be taken down, please follow our DMCA take down process here.