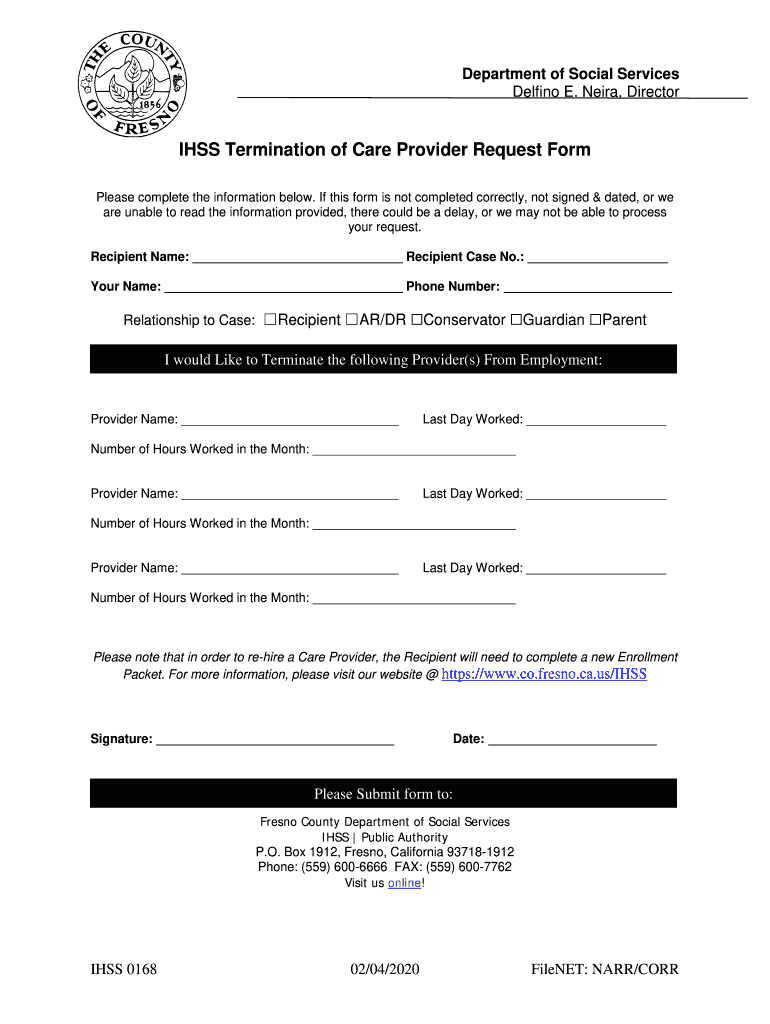
Department of Social Services Delfino E. Neira, DirectorIHSS Termination of Care Provider Request Form Please complete the information below. If this form is not completed correctly, not signed &.

Open form follow the instructions

Easily sign the form with your finger

Send filled & signed form or save
How to fill out the IHSS Termination Of Care Provider Request Form online
The IHSS Termination Of Care Provider Request Form is essential for formally notifying the necessary authorities about the termination of a care provider's employment. This guide provides clear, step-by-step instructions to help you complete the form accurately and efficiently online.
Follow the steps to complete the IHSS Termination Of Care Provider Request Form online
- Click ‘Get Form’ button to gain access to the IHSS Termination Of Care Provider Request Form and open it in the online editor.
- Begin filling out the form by entering the recipient's name and recipient case number in the designated fields.
- Next, input your name and phone number to ensure the authorities can contact you for any necessary follow-up.
- Select your relationship to the case by checking the appropriate box. Options include recipient, authorized representative or designated representative, conservator, guardian, or parent.
- For each care provider you wish to terminate, provide their name, last day worked, and the number of hours worked for the month in the corresponding fields. If there are multiple providers, repeat this process for each.
- When you have completed all necessary fields, sign the form in the designated signature area and include the date.
- Once the form is filled out completely, you may save your changes, then choose to download, print, or share the completed form as needed.
Complete your IHSS Termination Of Care Provider Request Form online for a streamlined submission process.
Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Related content
Q Forms. QR 2103 (11/11) - Reminder For Teens Turning 18 Years Old ... Services (IHSS)...
Health Care Certification (SOC 873) Form. During COVID-19. • Must be completed by...
Aug 22, 2016 — Molina Healthcare of Texas, Inc. Medicare Advantage Provider Manual...
Get answers to your most pressing questions about US Legal Forms API.
Provider Enrollment « Personal Assistance Services Council
Call the PASC Information and Referral Office at 877-565-4477 to locate the Regional Center in your area.
Live-in provider self-certification
To add or change a provider, please call your provider clerk. All new IHSS providers (i.e., providers who are not currently working for any consumers) must be enrolled with the county before they are eligible for payment through the IHSS Program.
How do I cancel my IHSS provider?
If you must quit a job or take time off, please tell your employer(s) first, then call the IHSS office. The Humboldt County IHSS program currently pays California State minimum wage. Effective January 1, 2017, Humboldt County providers will be paid an hourly rate of $10.50.
What is PASC IHSS?
The PASC Homecare Registry is arguably the largest In-Home Supportive Services (IHSS) provider referral service in California. Registry staff members respond to hundreds of service request calls and inquiries on a daily basis.
In-Home Supportive Services PASC Homecare Registry - Personal ...
It took about a full month to get completely started. You start by going to your local ihss in your city and fill out all the paper work and then follows with a background check and fingerprints and also followed with a 3 hour class. Then they find you a patient care for if you don't have one already.
In-Home Supportive Services Handbook - Humboldt County, CA
Beginning January 2017, you have the option to self-certify your living arrangements to exclude IHSS/WPCS wages from FIT and SIT by sending the Live-In Self-Certification Form (SOC 2298). All requested information on the form must be provided and the form must include your signature and the date you signed the form.
California's In-Home Support Program - Public Policy Institute of ...
Do you want to know if your payment has been issued yet? Now you can utilize the ESP to access this information 24 hours a day! IHSS Care Providers and IHSS Recipients can now access the California Department of Social Services' Electronic Services Portal to get real-time timesheet and payment status information!
PASC Registry « Personal Assistance Services Council
To add or change a provider, please call your provider clerk. All new IHSS providers (i.e., providers who are not currently working for any consumers) must be enrolled with the county before they are eligible for payment through the IHSS Program.
How do I quit IHSS?
If you must quit a job or take time off, please tell your employer(s) first, then call the IHSS office. The Humboldt County IHSS program currently pays California State minimum wage. Effective January 1, 2017, Humboldt County providers will be paid an hourly rate of $10.50.
Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
If you believe that this page should be taken down, please follow our DMCA take down process here.