Loading
Form preview
  • US Legal Forms
  • Other Templates
  • More Forms
  • More Uncategorized Forms
  • This Form Must Be Completed By A Physician Or Clinician.

Get This Form Must Be Completed By A Physician Or Clinician.

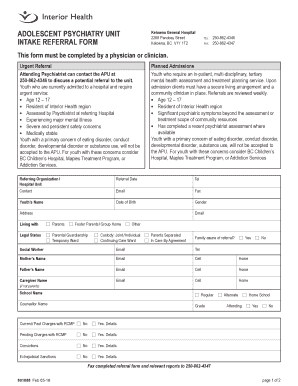
ADOLESCENT PSYCHIATRY UNIT INTAKE REFERRAL FORM Kelowna General Hospital 2268 Pandosy Street Kelowna, BC V1Y 1T2 tel 2508624346 fax 2508624347 This form must be completed by a physician or clinician.

How it works

  1. Open form

    Open form follow the instructions

  2. Easily sign form

    Easily sign the form with your finger

  3. Share form

    Send filled & signed form or save

How to use or fill out the This Form Must Be Completed By A Physician Or Clinician. online

Filling out the This Form Must Be Completed By A Physician Or Clinician accurately is essential for ensuring that youth receive the necessary mental health support. This guide provides step-by-step instructions to help physicians and clinicians complete the form efficiently and correctly.

Follow the steps to fill out the form online:

  1. Use the ‘Get Form’ button to access the form and open it in your preferred online document editor.
  2. Start by entering the referring organization or hospital unit details. Make sure you provide accurate referral date, telephone number, contact name, and email.
  3. Input the youth’s name, date of birth, gender, and address. Provide the youth's email and specify who they are living with.
  4. Specify the legal status selecting options from parental guardianship, temporary ward, or other categories as applicable.
  5. Indicate if the family is aware of the referral by checking 'Yes' or 'No'.
  6. Complete the fields regarding the social worker if applicable, and fill in the details of the youth's parents or caregivers.
  7. Provide the school name and the grade the youth is attending, marking if they are in a regular, alternate, or home school.
  8. Indicate any current or past charges with the RCMP and provide details if applicable.
  9. Check if the youth has seen a psychiatrist and provide their name, while indicating previous appointments and any significant medical concerns.
  10. Detail the presenting concerns and provide a description of the issues the youth is facing.
  11. State the reasons for referral, selecting from diagnostic clarification, treatment planning, or other specified reasons.
  12. List any medications the youth is currently taking or has taken in the past, including dosage and duration.
  13. Indicate if relevant reports or assessments will be included and explain if any are missing.
  14. Once the form is fully completed, save your changes, and choose to download, print, or share the form as needed.

Complete the necessary documents online today to ensure timely support for youth in need.

Get form

Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Get form

Related content

Basics for Physicians-Practitioners - EDD - CA.gov
Both you and the patient must certify that the information provided is complete and...
Learn more
medical record format - NC State College of...
It is the responsibility of the senior faculty clinician to ensure the completion of the...
Learn more
certificate of medical necessity cms-484 —...
I certify that I am the treating physician identified in Section A of this form. ... While...
Learn more

Related links form

Name PERSUASIVE SPEECH Date Of Speech INFOMERCIAL ORGANIZER Solicitation Letter For Basketball Uniform US Form 1040 And 1040NR Line 21 Other Income Worksheet 2015 - Montanacun Secure Cusolutionsgroup Form CT1 - Application By Trustees For Incorporation As A - Societies Govt

Questions & Answers

Get answers to your most pressing questions about US Legal Forms API.

Contact support

How to fill out a CMS-1500 form The type of insurance and the insured's ID number. The patient's full name. The patient's date of birth. The insured's full name, if applicable. The patient's address. The patient's relationship to the insured, if applicable. The insured's address, if applicable. Field reserved for NUCC use.

The Form CMS-1500 is the standard paper claim form to bill Medicare Fee-For-Service (FFS) Contractors when a paper claim is allowed. In addition to billing Medicare, the 837P and Form CMS-1500 may be suitable for billing various government and some private insurers.

The CMS-1500 claim form is used to submit non-institutional claims for health care services to many private payers, Medicare, Medicaid and other government health insurance programs.

In general, the UB-04 form is used by institutional healthcare providers, such as hospitals, nursing homes, and rehabilitation centers, while the CMS 1500 form is used by individual healthcare providers, such as physicians, therapists, and dietitians.

If you're incapacitated and unable to participate in your own plan selection process, someone else can act on your behalf as long as you've created a power of attorney (POA) and named that person as your legal representative.

CENTERS FOR MEDICARE & MEDICAID SERVICES. INSTRUCTIONS FOR THE MEDICARE PARTICIPATING PHYSICIAN. AND SUPPLIER AGREEMENT (CMS-460) To sign a participation agreement is to agree to accept assignment for all covered services that you provide to Medicare patients.

What is the 855B? ❖ The CMS form used for the enrollment of Clinic/Group practices and Certain Other Suppliers. This form is also used to submit changes to your enrollment data.

The Centers for Medicare and Medicaid Services (CMS) provides health coverage to more than 100 million people through Medicare, Medicaid, the Children's Health Insurance Program, and the Health Insurance Marketplace.

Get This Form Now!

Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
Get form
If you believe that this page should be taken down, please follow our DMCA take down processhere.
Get This Form Must Be Completed By A Physician Or Clinician.
Get form
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
  • Real Estate Handbook
  • All Guides
  • Notarize
  • Incorporation services
  • For Consumers
  • For Small Business
  • For Attorneys
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Form Packages
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
Form Categories
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
Customer Service
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
Legal Guides
  • Real Estate Handbook
  • All Guides
Prepared for you
  • Notarize
  • Incorporation services
Our Customers
  • For Consumers
  • For Small Business
  • For Attorneys
Our Sites
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Social Media
Call us now toll free:
+1 833 426 79 33
As seen in:
© Copyright 1999-2026 airSlate Legal Forms, Inc. 17 Station Street, Ste. 203, Brookline, MA 02445
  • Your Privacy Choices
  • Terms of Service
  • Privacy Notice
  • Content Takedown Policy
  • Bug Bounty Program