Loading
Form preview
  • US Legal Forms
  • Other Templates
  • More Forms
  • More Uncategorized Forms
  • Ibx Out Of Network Claim Form

Get Ibx Out Of Network Claim Form

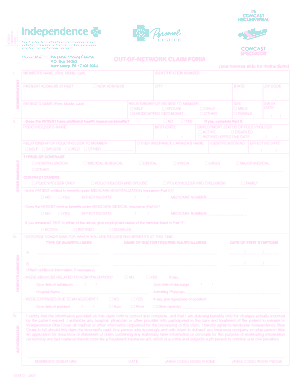
Ce Company, a subsidiary of Independence Blue Cross independent licensees of the Blue Cross and Blue Shield Association. OUT-OF-NETWORK CLAIM FORM MEMBER S NAME (First, Middle, Last) IDENTIFICATION NUMBER PRESENT ADDRESS STREET NEW ADDRESS PATIENT S NAME (First, Middle, Last) CITY STATE RELATIONSHIP OF PATIENT TO MEMBER SELF SPOUSE HANDICAPPED DEPENDENT Does the PATIENT have additional health insurance benefits? NO POLICYHOLDER S NAME YES BIRTH DATE / RELATIONSHIP OF.

How it works

  1. Open form

    Open form follow the instructions

  2. Easily sign form

    Easily sign the form with your finger

  3. Share form

    Send filled & signed form or save

How to fill out the Ibx Out Of Network Claim Form online

Filing an out-of-network claim can be a straightforward process when you have the right guidance. This guide will walk you through each section of the Ibx Out Of Network Claim Form, ensuring that you understand how to complete it correctly and efficiently.

Follow the steps to successfully complete your claim form.

  1. Click ‘Get Form’ button to obtain the form and open it in your document editor.
  2. Fill in your member and patient information. Start by entering the member's name, identification number, present address, and any new address if applicable.
  3. Provide the patient's name and their relationship to the member. You can select from options such as self, spouse, or dependent.
  4. Indicate whether the patient has additional health insurance benefits by selecting 'Yes' or 'No'. If 'Yes', complete the relevant sections for the policyholder's details.
  5. If applicable, complete the sections regarding Medicare coverage. Indicate whether the patient is entitled to benefits under Medicare Hospitalization Insurance (Part A) and Medicare Medical Insurance (Part B). Include the Medicare numbers if available.
  6. Describe the patient's condition for which you are requesting benefits. Provide specific details on the type of injury or illness, the name of the treating doctor, and the date of first symptoms.
  7. In the authorization section, review the statement, and ensure it is correct before signing and dating the form.
  8. Attach all necessary itemized bills, ensuring they include required information such as provider details, patient name, service descriptions, dates, amounts charged, and diagnosis.
  9. Once you have completed the form and attached the necessary documents, save your changes. You can then download or print your filled form for submission.

Begin filling out your Ibx Out Of Network Claim Form online today for a seamless claims experience.

Get form

Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Get form

Related content

[PDF] Keystone Health Plan East - Pennsylvania...
Our goal at Independence Blue Cross is to provide you with health care coverage that can...
Learn more
MEDICAL CLAIM FORM TO BE COMPLETED BY PATIENT ...
This claim form should be submitted only when you use a non-network provider who does not...
Learn more
[PDF] EDC User's Manual V2 - Estun
Don't connect the servo motor directly to local electric network. It's prohibited to...
Learn more

Related links form

A Werewolf The Apocalypse Supplement By Steven Markley Vampire The Masquerade Fillable Character Sheet Vampire 2nd Edition Character Sheet Mage The Awakening Pdf

Questions & Answers

Get answers to your most pressing questions about US Legal Forms API.

Contact support

Important telephone numbers Philadelphia areaCarelon Medical Benefits Management [formerly AIM Specialty Health® (AIM)]Provider Automated System1-800-ASK-BLUE (option 2) (1-800-275-2583, option 2) .ibx.com/providerautomatedsystemProvider Services Mon. – Fri., 8 a.m. – 5 p.m.1-800-ASK-BLUE (1-800-275-2583)49 more rows

During the grace period a member can make outstanding premium payments without losing coverage. If a member fails to make payment in full within 90 days, coverage will be terminated. Claims received during the first 30 days of the grace period will be paid on schedule.

Independence Blue Cross is the leading health insurance company in southeastern Pennsylvania, and with our affiliates we serve more than 8 million people nationwide.

You can also call Customer Service at 1-800-ASK-BLUE (1-800-275-2583) to find out if the prior authorization has been approved. Once your record shows the drug has been approved, the pharmacist can fill the prescription. 5.

Get This Form Now!

Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
Get form
If you believe that this page should be taken down, please follow our DMCA take down processhere.
Get Ibx Out Of Network Claim Form
Get form
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
  • Real Estate Handbook
  • All Guides
  • Notarize
  • Incorporation services
  • For Consumers
  • For Small Business
  • For Attorneys
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Form Packages
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
Form Categories
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
Customer Service
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
Legal Guides
  • Real Estate Handbook
  • All Guides
Prepared for you
  • Notarize
  • Incorporation services
Our Customers
  • For Consumers
  • For Small Business
  • For Attorneys
Our Sites
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Social Media
Call us now toll free:
+1 833 426 79 33
As seen in:
© Copyright 1999-2026 airSlate Legal Forms, Inc. 17 Station Street, Ste. 203, Brookline, MA 02445
  • Your Privacy Choices
  • Terms of Service
  • Privacy Notice
  • Content Takedown Policy
  • Bug Bounty Program