Loading
Form preview
  • US Legal Forms
  • Other Templates
  • Industry Forms
  • Industry Insurance & Medical Forms
  • First Choice Health Medical Claim Form

Get First Choice Health Medical Claim Form

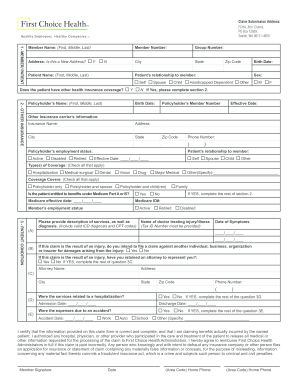
Middle, Last) Member Number: Group Number: City State Birth Date: Zip Code Patient s relationship to member: Self Does the patient have other health insurance coverage? Child Sex: Handicapped Dependent Other M F N If Yes, please complete section 2. Y 2 - OTHER INSURANCE Policyholder s Name: (First, Middle, Last) Spouse Birth Date: Policyholder s Member Number Effective Date: Other Insurance carrier s information: Insurance Name: Address: City State Zip Code Ph.

How it works

  1. Open form

    Open form follow the instructions

  2. Easily sign form

    Easily sign the form with your finger

  3. Share form

    Send filled & signed form or save

How to fill out the First Choice Health Medical Claim Form online

Completing the First Choice Health Medical Claim Form accurately is essential for ensuring that your claims are processed efficiently. This guide offers step-by-step instructions to help you navigate the form with ease, ensuring you provide all necessary information.

Follow the steps to submit your medical claim online.

  1. Press the ‘Get Form’ button to access the First Choice Health Medical Claim Form and open it in your chosen editor.
  2. Begin by filling in the member and patient information. Enter the member's name, including their first, middle, and last names, followed by their address. Indicate if this is a new address by selecting 'Yes' or 'No'. Provide the patient's name, member number, group number, city, state, birth date, and zip code.
  3. Specify the patient's relationship to the member by selecting one of the available options: 'Self', 'Child', or 'Handicapped Dependent'. Indicate the patient’s sex by checking the appropriate box for 'Male' or 'Female'. If the patient has other health insurance coverage, select 'Yes' or 'No', and if applicable, complete Section 2.
  4. In Section 2, provide details about the other insurance. Fill in the policyholder's name, relationship to the patient, and their effective date. Input the other insurance carrier's name, address, city, state, zip code, and phone number.
  5. Indicate the policyholder's employment status and the types of coverage available by checking all applicable boxes. Specify if the patient is entitled to benefits under Medicare and provide the Medicare ID and effective date, if relevant.
  6. In Section 3, describe the patient's condition. Provide a detailed description of services received, including valid ICD diagnosis and CPT codes. Fill in the date of symptoms onset and the name and tax ID number of the treating doctor.
  7. If the claim is due to an injury, indicate if you plan to file against another party and whether you have retained an attorney. If applicable, provide the attorney's contact information.
  8. Indicate whether the services are related to a hospitalization or accident. Fill in relevant dates and specify the circumstances of the incident, if applicable.
  9. Review all entries for accuracy and completeness. Sign and date the form, and provide your home phone number for contact purposes.
  10. Once you have completed the form, you can save changes, download, print, or share the form as needed.

Submit your completed First Choice Health Medical Claim Form online for prompt processing.

Get form

Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Get form

Related content

First Choice Medical Staffing
Claims and Billing · Dental Providers · Electronic Visit Verification ... Tax Forms ·...
Learn more
College Claim Form.21.2.indd
Completely and legibly fill out Part B (missing fields will cause delays) provide...
Learn more
Medicare
This transmittal introduces Chapter 40, Hospital and Hospital Health Care Complex Cost...
Learn more

Related links form

COLORADO CENTENNIAL FARM APPLICATION - History Colorado - Historycolorado Jefferson County Block Party Permit Fee Form Dr 2421 DOG LICENSE REGISTRATION - Jefferson County, Colorado - Co Jefferson Co

Questions & Answers

Get answers to your most pressing questions about US Legal Forms API.

Contact support

Filling out a medical authorization form starts with entering essential patient and healthcare provider information. Clearly indicate which medical records patients authorize to share and the purpose for this sharing. This detailed approach will support your First Choice Health Medical Claim Form and ensure your medical information is handled correctly.

To fill out a medical necessity form, provide detailed information about the medical condition, treatment, and supporting documentation from your healthcare provider. Be specific about how the proposed services are necessary and beneficial. Accurate details will strengthen your First Choice Health Medical Claim Form and increase the likelihood of approval.

When filling out a medical consent form, begin by entering the patient’s details and the specific treatment for which consent is given. It’s important to read the form carefully and check all provided information. This ensures that your First Choice Health Medical Claim Form reflects accurate consent documentation, which is essential for claim approval.

Filling out a medical release form requires you to provide vital patient information, including name, address, and date of birth. Clearly specify what medical records you want released and to whom the records will be sent. Using this approach will help facilitate quick processing of your First Choice Health Medical Claim Form.

To complete a patient authorization form, start by identifying the patient and the specifics of the information being released. Clearly state who is allowed to access the information and the purpose for which it is being used. By including these details, you ensure that your First Choice Health Medical Claim Form is processed without unnecessary delays.

Filling out a health insurance claim form involves collecting your insurance details and the specifics of your medical treatment. Begin by accurately completing your personal information, including your policy number and the provider's information. Finally, attach the required documents and submit your First Choice Health Medical Claim Form to your insurance company for prompt processing.

To fill out a reimbursement claim form, start by gathering all necessary documentation, including receipts and any relevant medical records. Next, enter your personal information, policy number, and details about the services you received. Ensure you provide a clear description of each claim, and submit the form along with supporting documents to ensure proper processing of your First Choice Health Medical Claim Form.

The most common insurance claim form used for outpatient and some inpatient claims is the CMS-1500 form. Healthcare providers often utilize this form, and it is crucial for accurately filing claims, including the First Choice Health Medical Claim Form. Understanding how to fill this form correctly ensures that your claims are processed quickly and efficiently.

To file a claim with Health First Insurance, start by gathering your medical documents along with the required form. Complete the First Choice Health Medical Claim Form, making sure all information is entered accurately and clearly. Along with the form, include any bills or statements from your healthcare provider, and submit everything according to Health First's guidelines for proper processing.

First Choice Health is a regional health insurance organization that provides a variety of health plans, including individual and employer-sponsored plans. Their offerings typically include PPO and HMO options, allowing members to choose their healthcare providers. Understanding the type of plan you have will help you utilize the First Choice Health Medical Claim Form effectively to get reimbursements for your medical expenses.

Get This Form Now!

Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
Get form
If you believe that this page should be taken down, please follow our DMCA take down processhere.
Get First Choice Health Medical Claim Form
Get form
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
  • Real Estate Handbook
  • All Guides
  • Notarize
  • Incorporation services
  • For Consumers
  • For Small Business
  • For Attorneys
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Form Packages
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
Form Categories
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
Customer Service
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
Legal Guides
  • Real Estate Handbook
  • All Guides
Prepared for you
  • Notarize
  • Incorporation services
Our Customers
  • For Consumers
  • For Small Business
  • For Attorneys
Our Sites
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Social Media
Call us now toll free:
+1 833 426 79 33
As seen in:
© Copyright 1999-2026 airSlate Legal Forms, Inc. 17 Station Street, Ste. 203, Brookline, MA 02445
  • Your Privacy Choices
  • Terms of Service
  • Privacy Notice
  • Content Takedown Policy
  • Bug Bounty Program