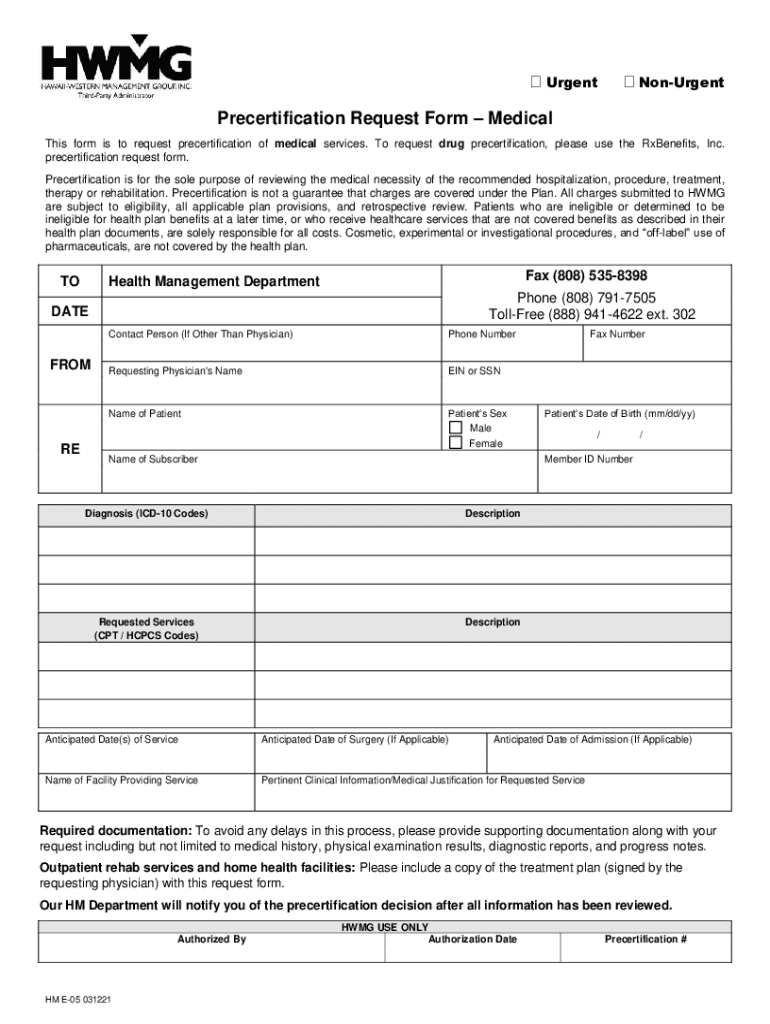
Precertification request form. Precertification is for the sole purpose of reviewing the medical necessity of the recommended hospitalization, procedure, treatment, therapy or rehabilitation. Precertification is not a guarantee that charges are covered under the Plan. All charges submitted to HWMG are subject to eligibility, all applicable plan provisions, and retrospective review. Patients who are ineligible or determined to be ineligible for health plan benefits at a later time, or who receiv.
Loading

Open form follow the instructions

Easily sign the form with your finger

Send filled & signed form or save
How to fill out the HWMG Precertification Request Form online
The HWMG Precertification Request Form is designed for users to request precertification of medical services efficiently. This guide will walk you through each section of the form to ensure accurate completion and submission online.
Follow the steps to complete the HWMG Precertification Request Form online
- Click ‘Get Form’ button to obtain the form and open it in your preferred online editor.
- Enter the date in the designated field to indicate when the request is being submitted.
- Fill in the 'FROM' section with your details if you are the person making the request.
- Under 'RE', provide the name of the contact person if it is not the physician making the request.
- Input the requesting physician’s name in the relevant section.
- Enter the EIN or SSN in the appropriate field.
- Provide the name of the patient for whom the precertification is being requested.
- Select the patient's sex by marking either 'Male' or 'Female'.
- Fill in the name of the subscriber responsible for the patient’s health plan.
- Add the patient's fax number in the specified field.
- Enter the patient's date of birth using the format mm/dd/yy.
- Input the member ID number associated with the patient's health plan.
- Write down the diagnosis using the corresponding ICD-10 codes.
- Specify the requested services by including the relevant CPT or HCPCS codes.
- Provide anticipated date(s) of service in the fields provided.
- If applicable, enter the anticipated date of surgery.
- If applicable, fill in the anticipated date of admission.
- Designate the name of the facility providing the requested service.
- Include pertinent clinical information or medical justification for the requested service in the specified area.
- To minimize delays, ensure you attach all necessary supporting documentation, such as medical history and treatment plans.
- Once all fields are completed and reviewed for accuracy, you can save the changes, download, print, or share the form as needed.
Complete your HWMG Precertification Request Form online today!
Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Related content
Welcome to the official website of the U.S. Department of Veterans Affairs. Discover...
Eastern Arizona College is The Smart Higher Education Destination for small class sizes...
You have received this form because your employer (or transfer agent) transferred your...
Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
If you believe that this page should be taken down, please follow our DMCA take down process here.