Loading
Form preview
  • US Legal Forms
  • Other Templates
  • More Forms
  • More Multi-State Forms
  • Or Ohsu Pediatric Patient Referral Form 2017

Get Or Ohsu Pediatric Patient Referral Form 2017-2026

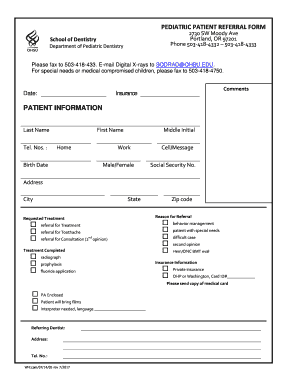
Digital X-rays to SODRAD OHSU.EDU. For special needs or medical compromised children, please fax to 503-418-4750. Date: Comments Insurance PATIENT INFORMATION Last Name Tel. Nos. : First Name Home Middle Initial Work Birth Date Male/Female Cell/Message Social Security No. Address City State Reason for Referral Requested Treatment referral for Treatment referral for Toothache nd referral for Consultation (2 opinion) Treatment Completed Zip code.

How it works

  1. Open form

    Open form follow the instructions

  2. Easily sign form

    Easily sign the form with your finger

  3. Share form

    Send filled & signed form or save

How to use or fill out the OR OHSU Pediatric Patient Referral Form online

Filling out the OR OHSU Pediatric Patient Referral Form online is a straightforward process. This guide will help you understand each section of the form to ensure that all necessary information is provided accurately and efficiently.

Follow the steps to easily complete your online referral form.

  1. Click ‘Get Form’ button to obtain the form and open it in the editor.
  2. Begin by entering the date at the top of the form. This date helps in organizing referrals properly.
  3. Fill in the patient information section, which includes the last name, first name, middle initial, and birth date of the patient. Ensure the information is accurate for identification purposes.
  4. Provide the patient's gender by selecting 'Male' or 'Female' and enter their Social Security number for insurance purposes.
  5. Complete the address section, which requires the street address, city, state, and zip code to locate the patient.
  6. In the reason for referral section, select the appropriate options that describe the referral type, such as referral for treatment or consultation.
  7. Indicate any completed treatments by checking relevant boxes, including behavior management or second opinion.
  8. Add the insurance information by selecting whether the patient has private insurance or participates in OHP or Washington programs. Ensure you enter the Card ID number if applicable.
  9. If there are special requests such as needing an interpreter, indicate the preferred language in the designated area.
  10. Fill in the referring dentist's information, including their name, address, and telephone number for follow-up.
  11. Once all information is completed, review the form for accuracy. After confirming that all details are correct, you can save changes, download, print, or share the form as necessary.

Complete the online OR OHSU Pediatric Patient Referral Form now for a seamless referral process.

Get form

Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Get form

Related content

Novel Interventions in Children's Healthcare...
Enrollment: To ask about joining the NICH program, please contact Samareh Shadbeh at...
Learn more
OHSU Knight Cancer Institute Your 2017 Guide to...
This referral guide is designed to help you easily connect with our adult oncology...
Learn more
Core Entrustable Professional Activities for...
1.8 Provide appropriate referral of patients, including ensuring continuity of care...
Learn more

Related links form

GA GPCSF 36 2011 GA GPCSF 4 2016 GA GPCSF 4 2015 GA GPCSF 4 2013

Questions & Answers

Get answers to your most pressing questions about US Legal Forms API.

Contact support

Provide information on the patient's current situation, as well as other medical records, test results, and documents to avoid duplicate effort. Agree on the urgency of the referral, how long the process might take, how often to communicate, and who will manage the patient during the referral timeframe.

For help with a referral, call our Physician Advice and Referral Service at 503-494-4567 between 7 a.m. and 7 p.m.

If you don't see your referral or need help: Call 503-494-4567 and choose option 4. If you need an OHSU Connect account: Visit ohsuhealth.com/connect.

Registration helps each clinic correctly identify you and your medical information and entails collecting basic information from you and creating your medical record. Registration (before first appointment only): For a clinic appointment, call 503-494-8505. For a hospital stay, call 503-494-8311.

Currently, our minimum qualifiers are: Cumulative total GPA of 2.80, as reported by AMCAS. Cumulative score of 497 on an eligible MCAT.

General information: 503-494-8311 Find direct phone numbers for care clinics, patient support, billing and insurance and other services.

How to Make an Appointment For a clinic appointment, call 503-494-8505. For a hospital stay, call 503-494-8311.

Get This Form Now!

Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
Get form
If you believe that this page should be taken down, please follow our DMCA take down processhere.
Get OR OHSU Pediatric Patient Referral Form
Get form
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
  • Real Estate Handbook
  • All Guides
  • Notarize
  • Incorporation services
  • For Consumers
  • For Small Business
  • For Attorneys
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Form Packages
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
Form Categories
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
Customer Service
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
Legal Guides
  • Real Estate Handbook
  • All Guides
Prepared for you
  • Notarize
  • Incorporation services
Our Customers
  • For Consumers
  • For Small Business
  • For Attorneys
Our Sites
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Social Media
Call us now toll free:
+1 833 426 79 33
As seen in:
© Copyright 1999-2026 airSlate Legal Forms, Inc. 17 Station Street, Ste. 203, Brookline, MA 02445
  • Your Privacy Choices
  • Terms of Service
  • Privacy Notice
  • Content Takedown Policy
  • Bug Bounty Program