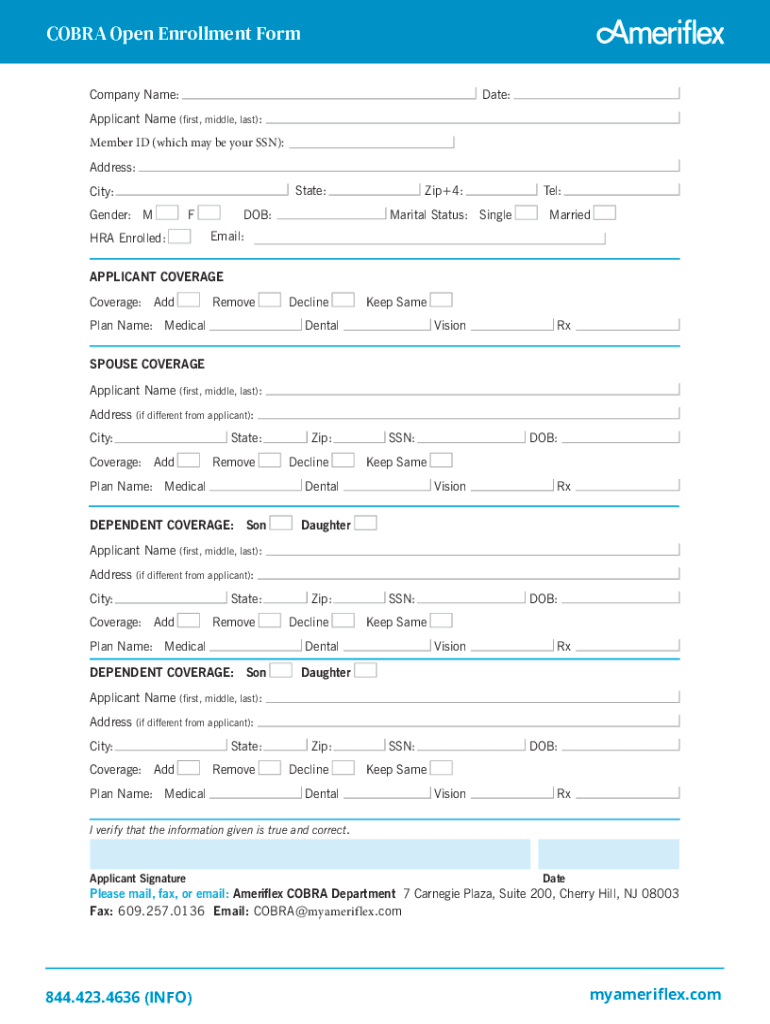
Arried Email: HRA Enrolled: APPLICANT COVERAGE Coverage: Add Remove Plan Name: Medical Decline Keep Same Dental Vision Rx SPOUSE COVERAGE Applicant Name Address (first, middle, last): (if different from applicant): City: State: Coverage: Add Remove Plan Name: Medical Address DOB: Keep Same Vision Rx Daughter (first, middle, last): (if different from applicant): City: State: Coverage: Add Remove Plan Name: Medical Applicant Name Zip: Decline SSN: DOB: Keep Same.

Open form follow the instructions

Easily sign the form with your finger

Send filled & signed form or save
How to fill out the Ameriflex COBRA Open Enrollment Form online
Filling out the Ameriflex COBRA Open Enrollment Form online is an important step in managing your healthcare benefits. This guide provides clear instructions to help you complete the form accurately and efficiently.
Follow the steps to complete your form online.
- Press the ‘Get Form’ button to access the Ameriflex COBRA Open Enrollment Form and open it in your preferred document editor.
- Begin by entering your company name in the designated field. Make sure this reflects the name of the organization you are enrolled with.
- Next, fill in your full name, including your first, middle, and last name. This information should accurately reflect your legal identification.
- Provide your Member ID, which may be your Social Security Number, in the appropriate field. Ensure this number is correct for seamless processing.
- Enter your complete address, including your state and city. Be sure to include the zip code, ensuring accuracy with the +4 digits if applicable.
- Indicate your gender by selecting the appropriate option provided on the form.
- Fill in your date of birth in the specified format requested.
- Select your marital status by marking the relevant choice, either 'Single' or 'Married.'
- Provide your primary telephone number and email address for future correspondence regarding your enrollment.
- Indicate if you are enrolled in a Health Reimbursement Arrangement (HRA) by selecting the appropriate response.
- For applicant coverage, choose to add, remove, or keep the same for the coverage options available, such as Medical, Dental, Vision, and Rx.
- If applicable, fill in details for any dependents you wish to enroll, including name, address, date of birth, and their relationship to you.
- Verify that all information provided is true and correct. Sign and date the form in the spaces provided.
- Upon completion of the form, you can save any changes, download the document for your records, print it, or share it as needed.
Complete your Ameriflex COBRA Open Enrollment Form online today for effective management of your health benefits.
Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Related content
COBRA enrollment form, carrier forms, and rate matrix for applicable plans ... • Open...
The child's COBRA coverage begins when the child is enrolled in the Plan, whether through...
Do Not mail this form directly to Ameriflex. City employees should Mail the form to the...
Get answers to your most pressing questions about US Legal Forms API.
How do I check my Ameriflex balance?
Through your online account and Ameriflex mobile app, you can check your balance, reimburse yourself for out-of-pocket spending, check the status of a claim, set up direct deposit, and more.
How do I get a new Ameriflex card?
Order a replacement card From your Ameriflex app, go to Menu > Debit Card. Select family member whose card is being replaced. Tap Report Card as Lost or Stolen and Issue Replacement. Check to make sure the address listed is correct, then tap Confirm Replacement.
What is Ameriflex COBRA?
The Consolidated Omnibus Budget Reconciliation Act (COBRA) of 1985 requires employers with 20 or more employees who provide healthcare benefits to offer the option of continuing this coverage to individuals who would otherwise lose their benefits due to termination of employment.
Do COBRA participants go through open enrollment?
Open enrollment isn't just for your active employees. Your COBRA members also go through an open enrollment period each year.
Why did I receive a Ameriflex card?
HRAs are funded by the employer to help offset out-of-pocket healthcare costs. Funds are tax-free for the employer and employee. Employees will receive an Ameriflex Debit Mastercard® linked to their HRA. Employees can use their card for eligible purchases everywhere Mastercard® is accepted.
How do I contact Ameriflex?
Questions? To learn more about how you can easily manage your healthcare benefit account from your mobile phone, contact Ameriflex at 888.868. 3539 or visit myameriflex.com.
What is covered by Ameriflex?
Employees can save up to 40% on thousands of eligible everyday expenses such as prescriptions, doctor's visits, dental services, glasses, over-the-counter medicines, and copays. Every dollar an employee contributes to an FSA lowers their taxable income.
Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
If you believe that this page should be taken down, please follow our DMCA take down process here.