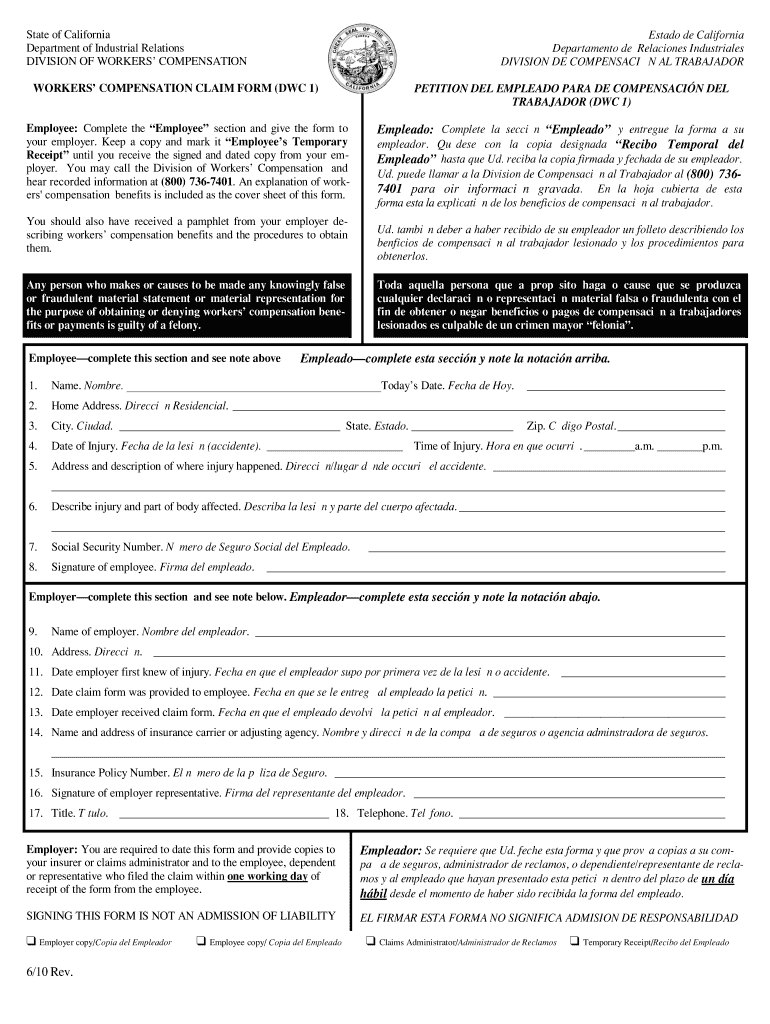
Or become ill, either physically or mentally, because of your job, including injuries resulting from a workplace crime, you may be entitled to workers compensation benefits. Attached is the form for filing a workers compensation claim with your employer. You should read all of the information below. Keep this sheet and all other papers for your records. You may be eligible for some or all of the benefits listed depending on the nature of your claim. If required you will be notified by the.

Open form follow the instructions

Easily sign the form with your finger

Send filled & signed form or save
How to fill out the DWC 1 online
The DWC 1 form is essential for individuals seeking workers' compensation benefits due to job-related injuries or illnesses. This guide provides clear, step-by-step instructions to assist users in completing the form online efficiently.
Follow the steps to complete the DWC 1 form accurately.
- Press the ‘Get Form’ button to access the DWC 1 document and open it in your preferred editor.
- Begin by completing the ‘Employee’ section. This includes entering your name, today's date, home address, city, state, zip code, and your Social Security Number.
- Next, fill in the date and time of your injury and provide a detailed description of where the injury occurred.
- Describe the nature of your injury and indicate which part of the body was affected.
- After completing the employee section, retain a copy marked 'Employee’s Temporary Receipt' until you receive the signed and dated copy from your employer.
- Submit the form to your employer. They will complete the ‘Employer’ section, which includes their name, address, and information regarding the claim.
- Once the employer section is complete, finish the form process by saving, downloading, or printing a copy for your records.
Take action by filling out your DWC 1 form online to begin the claims process and secure your benefits.
Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Related content
Jan 1, 2016 — To file a claim, complete the “Employee” section of the form, keep one...
WORKERS' COMPENSATION CLAIM FORM (DWC 1). Employee: Complete the “Employee” section...
1. Read these Instructions. - All these safety and operating instructions should be read...
Get answers to your most pressing questions about US Legal Forms API.
What is the EMPLOYERS wage statement DWC form 003?
The purpose of the form is to provide the employee's wage information to the carrier for calculating the employee's Average Weekly Wage (AWW) to establish benefits due to the employee or a beneficiary.
What is a form DWC 1?
DWC-1 Workers Compensation Claim Form. This is the form you will complete and send to EMPLOYERS to initiate the claim process for your employee. This form must be completed and provided to EMPLOYERS within one working day from you becoming aware of a work-related injury or occupational disease.
What does DWC claim mean?
Division of Workers' Compensation (DWC)
Who completes the DWC 1?
Your employer should fill out the “employer” section and forward the completed claim form to the insurance company. You should receive a copy of the completed claim form from your employer. If you don't, request a copy and keep it for your records.
Who fills out a dwc1?
Your employer should fill out the “employer” section and forward the completed claim form to the insurance company. You should receive a copy of the completed claim form from your employer. If you don't, request a copy and keep it for your records.
How do I fill out a CA 1 form?
Form CA-1 must be complete in a detailed manner; that is, you are expected to describe how you sustained your injuries, what you were doing and so on, or how you fell sick. You are also required to input the date, or, if you gradually became sick, indicate the time period.
How to fill out a DWC 1 form?
What Do I Include On My DWC-1 Form? Name, date, and address. Date and location of injury. Brief description of injury. List of injured body parts. Social Security Number.
What is the purpose of the DWC 1 form?
Your DWC-1 claim form is your declaration that you have been injured while working, and that you believe you require compensation while you recover. A common misconception is that going to the doctor – something you should doas soon as possible – essentially creates a workers' comp claim for you.
Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
If you believe that this page should be taken down, please follow our DMCA take down process here.