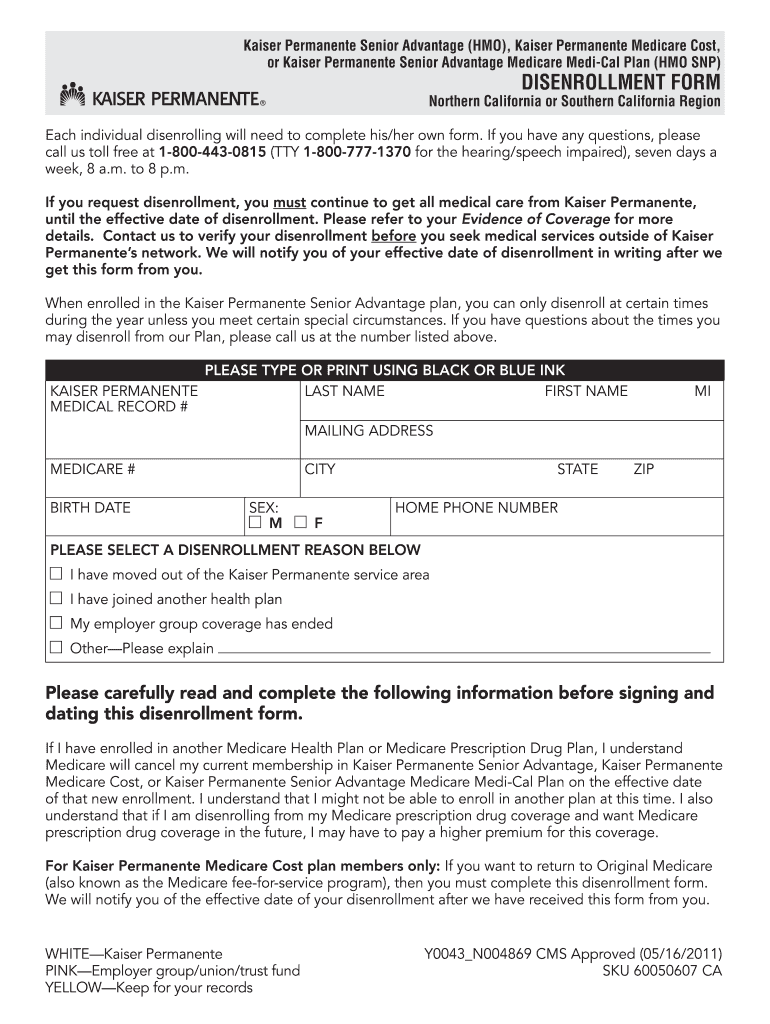
Ern California Region Each individual disenrolling will need to complete his/her own form. If you have any questions, please call us toll free at 1-800-443-0815 (TTY 1-800-777-1370 for the hearing/speech impaired), seven days a week, 8 a.m. to 8 p.m. If you request disenrollment, you must continue to get all medical care from Kaiser Permanente, until the effective date of disenrollment. Please refer to your Evidence of Coverage for more details. Contact us to verify your disenrollment before yo.

Open form follow the instructions

Easily sign the form with your finger

Send filled & signed form or save
How to fill out the KPSA SKU 60050607 CA online
This guide provides a comprehensive overview of how to fill out the KPSA SKU 60050607 CA disenrollment form online. By following these steps, you can ensure that your disenrollment process is efficient and accurate.
Follow the steps to complete the disenrollment form successfully.
- Click the ‘Get Form’ button to access the KPSA SKU 60050607 CA form and open it in the designated online form editor.
- Begin by filling out your personal information. Enter your last name, first name, middle initial, and medical record number in the appropriate fields. Ensure accuracy to avoid complications.
- Provide your mailing address, including city, state, and ZIP code. This information is crucial for communication regarding your disenrollment.
- Enter your Medicare number and birth date in the specified fields. This helps verify your identity and enrollment in Kaiser Permanente.
- Indicate your sex by selecting the appropriate option (M or F) in the designated section.
- Choose a disenrollment reason from the provided options: moving out of the service area, joining another health plan, employer group coverage ending, or other (with an explanation).
- Read the important information regarding the impact of disenrollment on your medical services. Acknowledge that you must continue to receive care from Kaiser Permanente until the effective date.
- Provide your signature and the date to certify your request for disenrollment. If someone else is signing on your behalf, ensure they include their name, address, phone number, and relationship to you.
- Follow instructions for returning the form. Send the signed white copy to Kaiser Permanente's Medicare Unit, and keep the yellow copy for your records. If applicable, send the pink copy to your employer group.
- Once completed, save any changes made to your form. Then proceed to download, print, or securely share the form as needed.
Complete your disenrollment form online today to ensure a smooth transition.
Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Related content
... California Region. Each individual disenrolling will need to complete his/her own...
Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
If you believe that this page should be taken down, please follow our DMCA take down process here.