Loading
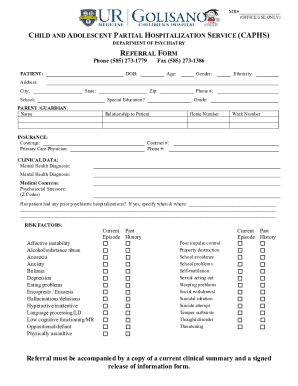
Get Ur Medicine Caphs Referral Form 2021-2026
How it works
-

Open form follow the instructions
-

Easily sign the form with your finger
-

Send filled & signed form or save
How to fill out the UR Medicine CAPHS Referral Form online
This guide provides clear instructions for filling out the UR Medicine Child and Adolescent Partial Hospitalization Service (CAPHS) Referral Form online. Follow these steps to ensure that all necessary information is accurately submitted for referral.
Follow the steps to successfully complete the referral form.
- Click ‘Get Form’ button to access the UR Medicine CAPHS Referral Form and open it in your preferred editing tool.
- Begin by providing the patient's information, including their name, date of birth, age, gender, ethnicity, and address. Ensure all details are accurate and clearly printed.
- Next, fill in the parent or guardian's details. Include their name, relationship to the patient, and whether the patient is in special education. Additionally, include the patient's school information.
- In the insurance section, indicate coverage information, primary care physician details, and contact numbers for home and work. Provide the contract number if applicable.
- For clinical data, specify the mental health diagnosis, any medical concerns, and psychosocial stressors. If applicable, document previous psychiatric hospitalizations.
- Assess and indicate any risk factors related to the patient's current episode and past history. This includes a range of affective or behavioral issues.
- Complete the psychotropic medications section, detailing past trials or current regimens, including medication names, dosages, target symptoms, and responses.
- Indicate any medical issues such as diabetes or asthma, including details of the medical condition and associated providers.
- Provide information regarding any legal involvement or child protective services (CPS) issues that may be relevant.
- Describe the patient's experience in group settings and document their chief complaint.
- Clearly articulate the therapist's or provider's reason for referral and current treatment providers, including names, phone numbers, addresses, and duration of treatment.
- Finally, enter the referring person's contact details and confirm whether the patient is in agreement with the referral. Ensure all required forms, including a clinical summary and a signed release of information, are attached.
- Once all sections are complete, save your changes, download, print, or share the completed referral form as necessary.
Complete your documents online now to ensure efficient processing of your referral.