Loading
Form preview
  • US Legal Forms
  • Other Templates
  • More Forms
  • More Multi-State Forms
  • Mercy Care () Authorization Form 2018

Get Mercy Care () Authorization Form 2018-2026

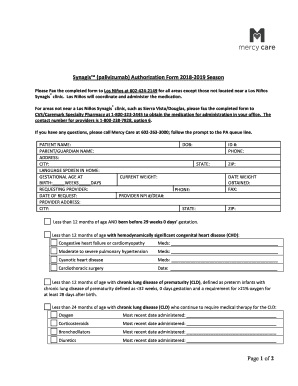
() Authorization Form 20182019 Season Please Fax the completed form to Los BIOS at 6024242149 for all areas except those not located near a Los BIOS clinic. Los BIOS will coordinate and administer.

How it works

  1. Open form

    Open form follow the instructions

  2. Easily sign form

    Easily sign the form with your finger

  3. Share form

    Send filled & signed form or save

How to fill out the Mercy Care Authorization Form online

Filling out the Mercy Care Authorization Form correctly is essential to ensure that requests for services are processed efficiently. This guide provides clear, step-by-step instructions on how to complete the form online to support your healthcare needs.

Follow the steps to successfully complete the form.

  1. Click the ‘Get Form’ button to obtain the authorization form and open it in your preferred online editor.
  2. Begin by filling in the patient’s full name in the 'Patient Name' field. Make sure to enter this information accurately, as it is crucial for identification.
  3. Next, in the 'Parent/Guardian Name' field, provide the full name of the individual responsible for the patient if applicable.
  4. Fill out the 'Address', 'City', and 'State' fields with the patient's current residential address to ensure correspondence can be sent correctly.
  5. Indicate the 'Language Spoken in Home' to assist in language preferences for communication.
  6. Enter the 'Gestational Age at Birth' in weeks and days, which helps assess eligibility based on age.
  7. Provide details about the 'Requesting Provider', filling in their name, contact information, and any other requested identifiers.
  8. Complete the 'Date of Request' field to indicate when this authorization request is being submitted.
  9. Include the patient's 'Date of Birth' (DOB) to confirm their identity and age.
  10. Fill in the 'ID #', which may be the patient’s insurance or identification number, required for processing.
  11. Add in 'Current Weight' details, as this information is often required for medication dosing.
  12. In the 'Expected Date of First/Next Injection' field, specify when the patient is expected to receive treatment.
  13. Indicate whether an injection has already been given by selecting 'Yes' or 'No' and, if applicable, note the date(s) of prior injections.
  14. Ensure you sign and date the document in the 'Prescriber’s Signature' field, as this is required for authenticity and acceptance.
  15. Once all sections are filled out, review the form for accuracy. You can then save changes, download the completed document, print, or share it as needed.

Complete your Mercy Care Authorization Form online today to ensure timely access to services.

Get form

Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Get form

Related content

1ROI
Mercy Health Hospital or Physician office health information requested from: ... Abstract...
Learn more
Medical Records | Children's Mercy Kansas City
The Children's Mercy Health Information Management (HIM) department ... by filling out an...
Learn more
Dell DataIQ Best Practices Guide
Aug 23, 2022 — It surfaces current cluster health status along with tools to ... For all...
Learn more

Related links form

Denneroll Time Chart 2020 FLAVIUS MAREKA TVET COLLEGE - ANNUAL REPORT 2020 Department Of Education Eastern Cape 2020 Intake Form For Day Care Service 2020

Questions & Answers

Get answers to your most pressing questions about US Legal Forms API.

Contact support

Mercy Care RBHA's timely filing limitations are as follows: New claim submissions: Claims must be filed on a valid claim form within 150 days from the date services were performed or from the date of eligibility posting, whichever is later, unless there is a contractual exception.

About Mercy Care Mercy Care is a not-for-profit health plan offering integrated care to children, adults and seniors eligible for AHCCCS benefits.

Mercy Care is a not-for-profit health plan serving AHCCCS members throughout Arizona. Owned by Dignity Health and Ascension Health, Mercy Care has served Medicaid members since 1985.

Mercy Care serves AHCCCS members in Maricopa, Pima, Pinal and Gila counties. You have your own health needs. And our health plan is designed to help meet those needs.

Mercy Care has been serving Medicaid members across Arizona since 1985.

Payer Name: Mercy Care Plan (AHCCCS)|Payer ID: 86052|Professional (CMS1500)/Institutional (UB04)[Hospitals]

AHCCCS is Arizona's State Medicaid Program. AHCCCS Members who also have Medicare are called Dual Eligible Members. Being enrolled in the same health plan for Medicare and Medicaid is called “alignment.”

The Mercy Care Department of Child Safety Comprehensive Health Plan (Mercy Care DCS CHP) is the single, statewide health plan, responsible for the physical, dental, and behavioral health services for all Arizona children in foster care.

Get This Form Now!

Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
Get form
If you believe that this page should be taken down, please follow our DMCA take down processhere.
Get Mercy Care () Authorization Form
Get form
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
  • Real Estate Handbook
  • All Guides
  • Notarize
  • Incorporation services
  • For Consumers
  • For Small Business
  • For Attorneys
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Form Packages
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
Form Categories
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
Customer Service
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
Legal Guides
  • Real Estate Handbook
  • All Guides
Prepared for you
  • Notarize
  • Incorporation services
Our Customers
  • For Consumers
  • For Small Business
  • For Attorneys
Our Sites
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Social Media
Call us now toll free:
+1 833 426 79 33
As seen in:
© Copyright 1999-2026 airSlate Legal Forms, Inc. 17 Station Street, Ste. 203, Brookline, MA 02445
  • Your Privacy Choices
  • Terms of Service
  • Privacy Notice
  • Content Takedown Policy
  • Bug Bounty Program