Loading
Form preview
  • US Legal Forms
  • Other Templates
  • More Forms
  • More Multi-State Forms
  • Ar Bcbs Group Employee Vision Application And Change Form ...

Get Ar Bcbs Group Employee Vision Application And Change Form ...

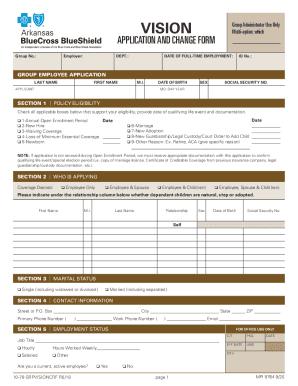
VISIONGroup Administrator Use Only Multi option: whichAPPLICATION AND CHANGE FORM Group No.:Employer:DEPT.:DATE OF FULL TIME EMPLOYMENT:ID No.:GROUP EMPLOYEE APPLICATION LAST NAMEFIRST NAME. I.DATE.

How it works

  1. Open form

    Open form follow the instructions

  2. Easily sign form

    Easily sign the form with your finger

  3. Share form

    Send filled & signed form or save

How to fill out the AR BCBS Group Employee Vision Application And Change Form online

This guide provides you with a structured approach to completing the AR BCBS Group Employee Vision Application And Change Form online. By following these instructions, you will be able to accurately fill out the necessary information and submit your application with confidence.

Follow the steps to successfully complete the application form.

  1. Click ‘Get Form’ button to obtain the form and open it in the editor.
  2. Complete the group employee application section by filling in your last name, first name, middle initial, date of birth, sex, and social security number. Ensure that all details are accurate.
  3. For section 1, policy eligibility, check all applicable boxes that indicate your eligibility, along with the date of the qualifying life event. Provide necessary documentation if the application is submitted outside the open enrollment period.
  4. In section 2, indicate the coverage desired by selecting one of the options: employee only, employee and spouse, employee and children, or employee, spouse, and children. List the relationship of dependent children as natural, step, or adopted.
  5. In section 3, select the appropriate marital status: single (including widowed or divorced) or married (including separated).
  6. Provide contact information in section 4 by filling in your street address, city, state, zip code, primary phone number, work phone number, and email address.
  7. In section 5, confirm your employment status by noting your job title, work classification (hourly, salaried, or other), and whether you are a current, active employee.
  8. Complete section 6 by providing current and previous vision insurance information. Include details for each covered family member and indicate if any do not reside in your household.
  9. For section 7, if applicable, provide any change requests along with the corresponding reasons. Include necessary changes to dependent status as required.
  10. In section 8, read the authorization and signatures, fill in your printed name, signature, and the date. Ensure that the employer/group representative also signs and dates if required.
  11. Review all filled sections for accuracy. You can then save the completed changes, download, print, or share the form as needed.

Complete your documents online with ease and ensure all necessary information is provided.

Get form

Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Get form

Related content

Public School Employees
ENROLLING, CANCELING, AND MAKING CHANGES TO YOUR ARBENEFITS COVERAGE. Enrolling as a new...
Learn more
Your Vision Care Benefit Program The University of...
Blue Cross and Blue Shield EyeMed and/or your Group may change the Bene ... You can get...
Learn more
team member benefits guide - Morgan Olson
Vision. Financial. Protection. Additional. Benefits. Family. Support ... Changes in your...
Learn more

Related links form

Nomad Pro 2 Operator Exam 2020 Groote Schuur High School Fees 2020 2020 Vodafone Migration Form 2020 Registration Form Filmmaking Workshop - Barbican Centre 2020

Questions & Answers

Get answers to your most pressing questions about US Legal Forms API.

Contact support

Member Service Lines ServiceNumberCustomer Service (main line)800-238-8379Metallic Plan Members (Gold, Silver, Bronze and Catastrophic)800-800-4298 (TDD 501-502-1458)Dental - Benefits and Billing questions888-224-5213Dental - Claim questions888-223-499915 more rows

For more information, contact customer service at 800-800-4298.

Call us BlueAdvantage Customer Service. 888-872-2531. Special Delivery. 800-225-1891, ext. 20225. Hours: 8 a.m. to 4:30 p.m. Monday - Friday. Or a complete list. Email customer service.

Member Service Lines ServiceNumberCustomer Service (main line)800-238-8379Metallic Plan Members (Gold, Silver, Bronze and Catastrophic)800-800-4298 (TDD 501-502-1458)Dental - Benefits and Billing questions888-224-5213Dental - Claim questions888-223-499915 more rows

You may have in-network. health plan benefits outside the state of Arkansas only for medical emergencies while you are travelling. If your ID card displays an empty suitcase logo, you have BlueCard coverage called "Traditional BlueCard." You have access to the BlueCard Traditional provider network (not the PPO network) ...

Call My BlueLine for member information Participating providers may call My BlueLine at 800-827-4814 for eligibility, claim status and benefit information for members of Arkansas Blue Cross, Health Advantage and BlueAdvantage Administrators of Arkansas.

Get This Form Now!

Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
Get form
If you believe that this page should be taken down, please follow our DMCA take down processhere.
Get AR BCBS Group Employee Vision Application And Change Form ...
Get form
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
  • Real Estate Handbook
  • All Guides
  • Notarize
  • Incorporation services
  • For Consumers
  • For Small Business
  • For Attorneys
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Form Packages
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
Form Categories
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
Customer Service
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
Legal Guides
  • Real Estate Handbook
  • All Guides
Prepared for you
  • Notarize
  • Incorporation services
Our Customers
  • For Consumers
  • For Small Business
  • For Attorneys
Our Sites
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Social Media
Call us now toll free:
+1 833 426 79 33
As seen in:
© Copyright 1999-2026 airSlate Legal Forms, Inc. 17 Station Street, Ste. 203, Brookline, MA 02445
  • Your Privacy Choices
  • Terms of Service
  • Privacy Notice
  • Content Takedown Policy
  • Bug Bounty Program