Loading
Form preview
  • US Legal Forms
  • Other Templates
  • More Forms
  • More Multi-State Forms
  • Multicare Authorization To Use And Disclose Protected Health Information 2017

Get Multicare Authorization To Use And Disclose Protected Health Information 2017-2026

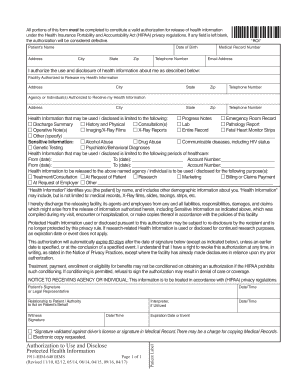
If any field is left blank, the authorization will be considered defective. Patient s Name Address Date of Birth City State Zip Telephone Number *ROI* Medical Record Number Email Address I authorize the use and disclosure of health information about me as described below: Facility Authorized to Release my Health Information Address City State Zip Telephone Number State Zip Telephone Number Agency or Individual(s) Authorized to Receive my Health Information Address City Hea.

How it works

  1. Open form

    Open form follow the instructions

  2. Easily sign form

    Easily sign the form with your finger

  3. Share form

    Send filled & signed form or save

How to fill out the MultiCare Authorization To Use And Disclose Protected Health Information online

Completing the MultiCare Authorization To Use And Disclose Protected Health Information is essential for managing your health information effectively. This guide will provide you with clear and supportive instructions on how to fill out this form online, ensuring that all necessary details are included for a valid authorization.

Follow the steps to complete your authorization form accurately.

  1. Click ‘Get Form’ button to access the MultiCare Authorization To Use And Disclose Protected Health Information and open it in the editor.
  2. Provide the patient’s name, address, date of birth, city, state, zip code, and telephone number in the designated fields. Ensure that all personal information is accurate and complete.
  3. Enter the medical record number and email address, if applicable. This information helps in identifying the correct health records.
  4. In the section titled 'I authorize the use and disclosure of health information about me as described below,' complete the information for the facility authorized to release health information. Fill in the name, address, city, state, zip code, and telephone number of the facility.
  5. Identify the agency or individual(s) authorized to receive health information and provide their respective details, including address and contact information.
  6. Specify the health information that may be used or disclosed by selecting the relevant types of records such as progress notes, lab results, or entire medical records. If there are additional types of information, indicate them in the 'Other' section.
  7. If applicable, indicate any sensitive information that may be disclosed, ensuring you check the appropriate boxes, which may include alcohol abuse or communicable diseases.
  8. Provide the periods of healthcare for which this authorization applies by entering the start and end dates along with any associated account numbers.
  9. Fill in the purpose for the release of information. Choose from options such as treatment, research, or billing. If it is for another purpose, please specify.
  10. Sign the document in the 'Patient’s Signature or Legal Representative' section. Ensure the date and time of signing are correctly recorded, and specify your relationship to the patient if you are signing on their behalf.
  11. If applicable, have a witness and an interpreter sign where indicated, making sure to include the date and time.
  12. Finally, review the completed form for accuracy. After confirming that all fields are filled out, you can save the changes, download, print, or share the completed authorization form.

Complete your MultiCare Authorization To Use And Disclose Protected Health Information online today for easier management of your health information.

Get form

Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Get form

Related content

MultiCare System-wide Hospital Non-discrimination...
under direct control of MHS, who access, use, disclose or come in contact with patient...
Learn more
MHS Intake Form (intended for info gathering to...
Information Services. User Registration. Applications/Systems. MultiCare Health System...
Learn more
2020 Kaiser Permanente WA Options Plan Guide...
Kaiser Permanente, Providence, and MultiCare ... You're taking a prescription drug or...
Learn more

Related links form

Amc Middle Primary Past Papers 2020 Alabama Drivers License Template 2020 Get The Prudential Life Insurance Surrender Form 2020 TDA Deferral Status Election Form (For Retiring Members) (code TD30). Form - Trsnyc 2020

Questions & Answers

Get answers to your most pressing questions about US Legal Forms API.

Contact support

Waiver of the HIPAA authorization requirement from the IRB. A waiver is a request to forgo the authorization requirement based on the fact that the disclosure of PHI involves minimal risk to the participant and the research cannot practically be done without access to/use of PHI.

An inadvertent disclosure is an event where a health professional unintentionally reveals protected health information (PHI) to an unauthorized person by mistake. Inadvertent disclosures and breach notifications. Generally, if PHI is disclosed to unauthorized personnel, a breach of PHI is presumed to have occurred.

A covered entity must obtain the individual's written authorization for any other use or disclosure of PHI, including the marketing and sale of PHI. Individual authorization must be received before using PHI for marketing communications that encourage recipients to purchase or use a product or service.

A HIPAA authorization is a detailed document in which specific uses and disclosures of protected health are explained in full. By signing the authorization, an individual is giving consent to have their health information used or disclosed for the reasons stated on the authorization.

Consent to Release Information The name of the person or entity authorized to make the request (usually the patient) The complete name of the person or entity to receive the protected health information (PHI) A specific description of the information to be used or disclosed, including the dates of service.

If you do decide to obtain consent, you have complete discretion to design a process that best suits your needs. By contrast, the Privacy Rule requires an "authorization" for uses and disclosure of protected health information not otherwise allowed by the rule.

More generally, HIPAA allows the release of information without the patient's authorization when, in the medical care providers' best judgment, it is in the patient's interest. Despite this language, medical care providers are very reluctant to release information unless it is clearly allowed by HIPAA.

The core elements of a valid authorization include: A meaningful description of the information to be disclosed. The name of the individual or the name of the person authorized to make the requested disclosure. The name or other identification of the recipient of the information.

Get This Form Now!

Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
Get form
If you believe that this page should be taken down, please follow our DMCA take down processhere.
Get MultiCare Authorization To Use And Disclose Protected Health Information
Get form
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
  • Real Estate Handbook
  • All Guides
  • Notarize
  • Incorporation services
  • For Consumers
  • For Small Business
  • For Attorneys
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Form Packages
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
Form Categories
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
Customer Service
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
Legal Guides
  • Real Estate Handbook
  • All Guides
Prepared for you
  • Notarize
  • Incorporation services
Our Customers
  • For Consumers
  • For Small Business
  • For Attorneys
Our Sites
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Social Media
Call us now toll free:
+1 833 426 79 33
As seen in:
© Copyright 1999-2026 airSlate Legal Forms, Inc. 17 Station Street, Ste. 203, Brookline, MA 02445
  • Your Privacy Choices
  • Terms of Service
  • Privacy Notice
  • Content Takedown Policy
  • Bug Bounty Program