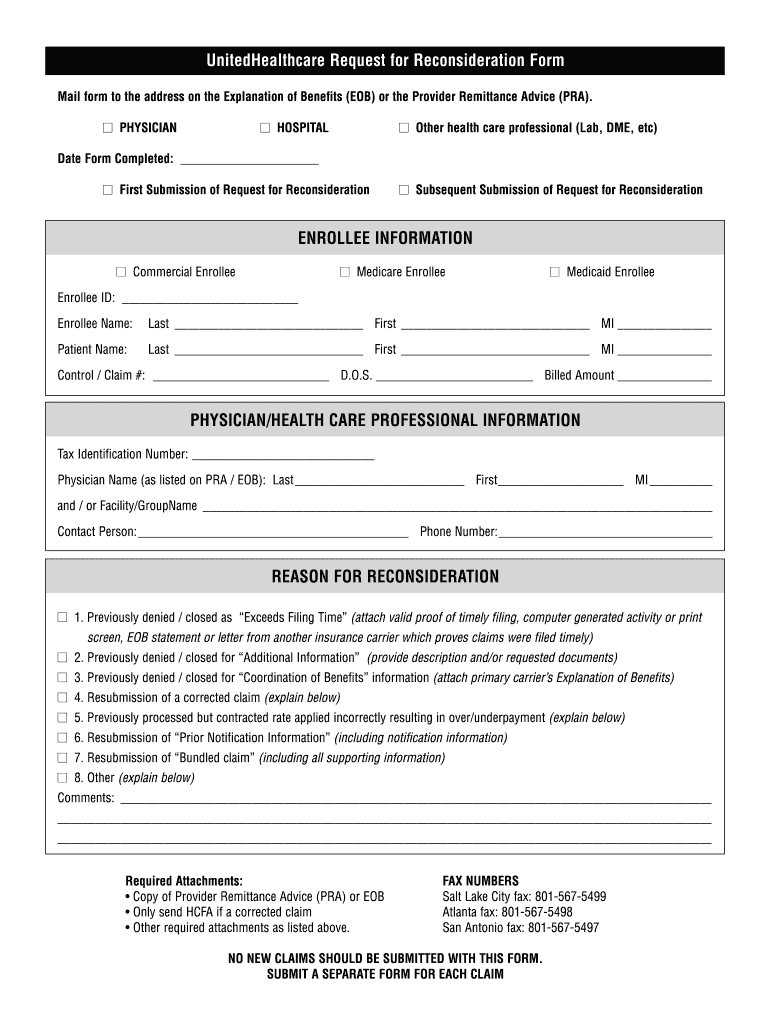
Lth care professional (Lab, DME, etc) Date Form Completed: First Submission of Request for Reconsideration Subsequent Submission of Request for Reconsideration ENROLLEE INFORMATION Commercial Enrollee Medicare Enrollee Medicaid Enrollee Enrollee ID: Enrollee Name: Last First MI Patient Name: Last First.
Loading

Open form follow the instructions

Easily sign the form with your finger

Send filled & signed form or save
How to fill out the UHC Request For Reconsideration Form - Cat Health Benefits online
Navigating the UHC Request For Reconsideration Form for Cat Health Benefits can be a straightforward process with the right guidance. This user-friendly guide will provide you with step-by-step instructions to ensure that your submission is accurate and complete.
Follow the steps to effectively complete your form online.
- Click ‘Get Form’ button to access the form and open it in the editor.
- Indicate the completion date of the form in the designated area.
- Select whether this is your first or subsequent submission of the request for reconsideration.
- Provide the enrollee information, including whether the enrollee is a commercial, Medicare, or Medicaid enrollee, along with their Enrollee ID and name details.
- Enter the patient’s name along with their relevant details.
- Fill in the control or claim number, date of service (D.O.S.), and billed amount.
- Complete the physician or health care professional information section, including the tax identification number and the name of the physician or facility group.
- Designate a contact person and their corresponding phone number for additional inquiries.
- Select the reason for the reconsideration from the provided options and provide any necessary details or explanations in the comments section.
- Attach the required documents as specified, such as a copy of the Provider Remittance Advice or Explanation of Benefits.
- Review all sections of the form to ensure completeness and accuracy before finalizing.
- Save changes to the form, download, print, or share it as needed before submitting.
Submit your completed UHC Request For Reconsideration Form online today.
Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Related content
When care is authorized at a participating Center of Excellence, you have paid-in-full...
Jan 1, 2011 — Advantage HMO Plan. Since 1978, we've been providing health care coverage...
Provider Reconsideration of Delegated Claims – Contracted Providers. 85. Fraud and Abuse...
Get answers to your most pressing questions about US Legal Forms API.
Why did UnitedHealthcare deny my claim?
Some of the reasons they provided for rejecting insurance claims include: the coverage requested isn't provided in the insurance policy agreement. questioning the necessity of the treatment. declaring the medication as an "experimental" drug.
How do I submit a reconsideration to UHC portal?
Getting set up for online submissions If you aren't registered, please go to UHCprovider.com/access. To submit a single claim reconsideration or corrected claim, you can use the Claims tool on the UnitedHealthcare Provider Portal. Please refer to the Claims Interactive Guide for instructions.
How do I submit a reconsideration for UHC?
Where do I send my United Healthcare reconsideration form? Send the letter or the Redetermination Request Form to the Medicare Part C and Part D Appeals and Grievance Department PO Box 6103, MS CA124-0197, Cypress CA 90630-0023.
Where do I send my UHC reconsideration form?
UnitedHealthcare Member Inquiry/Appeals PO Box 30432 Salt Lake City, UT 84130-0432. You will receive a written response to your submission within the timeframe required by law.
How long does an appeal process take from UHC?
If we deny an expedited appeal, the appeal is then processed through the normal appeal process which will be resolved within 30 calendar days from the day we receive your appeal.
How do I appeal an insurance denial UnitedHealthcare?
Mail or Fax. Write a letter describing your appeal or use the Redetermination Request Form (PDF) (67.62 KB). Mail or fax the letter or completed form to UnitedHealthcare.
How long does UHC reconsideration take?
Claim reconsideration You will receive a decision in writing within 60 calendar days from the date we receive your appeal. If you have a question about a pre-service appeal, see the section on Pre-Service Appeals section in Chapter 7: Medical Management.
How do I submit an appeal to UHC provider portal?
Electronic submission options Go to UHCprovider.com > Select Sign In at the top-right corner. Sign in to the portal with your One Healthcare ID and password. ... In the menu, click Claims & Payments > Look up a Claim to search by the claim number and click Act on Claim.
Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
If you believe that this page should be taken down, please follow our DMCA take down process here.