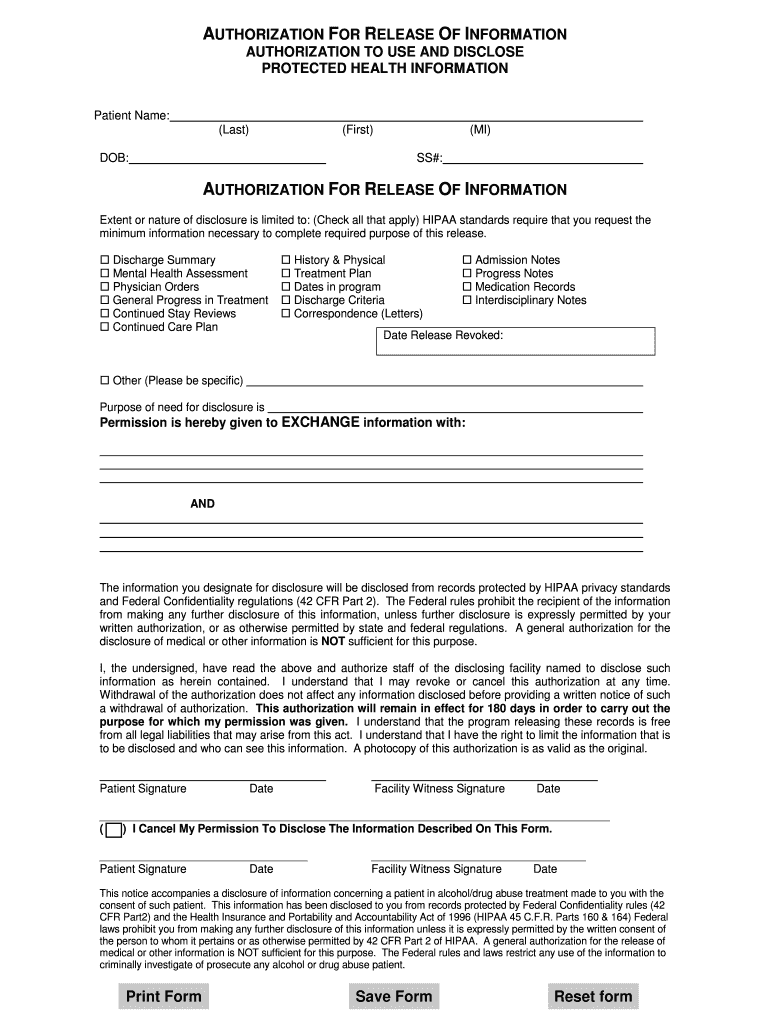
AUTHORIZATION FOR RELEASE OF INFORMATION AUTHORIZATION TO USE AND DISCLOSE PROTECTED HEALTH INFORMATION Patient Name: (Last)(First)DOB:(MI) SS#:AUTHORIZATION FOR RELEASE OF INFORMATION Extent or nature.

Open form follow the instructions

Easily sign the form with your finger

Send filled & signed form or save
How to fill out the MT DPHHS Authorization For Release Of Information online
The MT DPHHS Authorization For Release Of Information form allows individuals to authorize the disclosure of their protected health information in compliance with federal regulations. This guide provides clear, step-by-step instructions on how to fill out the form accurately online.
Follow the steps to easily complete your form online.
- Click ‘Get Form’ button to obtain the form and open it in the editor.
- Begin by entering the patient's name in the designated fields for last name, first name, and middle initial. Ensure that you input the correct date of birth and social security number for accurate identification.
- In the section for extent or nature of disclosure, check all applicable options to specify what information is being authorized for release, such as 'Discharge Summary' or 'Progress Notes'.
- Enter the purpose for the disclosure in the provided field. This helps clarify why the information is being requested.
- Provide the names of the parties with whom information will be exchanged. This section may require the names of individuals or organizations that will receive the information.
- Review the acknowledgments concerning HIPAA and federal confidentiality protections, ensuring you understand the limitations regarding further disclosure.
- Sign and date the form in the designated area to confirm your authorization. This signature serves as your consent for the disclosures mentioned.
- If applicable, a witness from the facility must sign and date the form as well.
- Once all fields are complete and checked for accuracy, you may download or print the completed form for your records or submission.
- After saving changes, ensure you share the completed document with the necessary parties as required.
Complete your MT DPHHS Authorization For Release Of Information online today for efficient processing.
Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Related content
The Montana Department of Public Health and Human Services (DPHHS) is a “hybrid...
STATE OF MONTANA. - RELEASE OF INFORMATION -. For Registered and Licensed Child Care...
Nov 11, 2019 — Benefits Information Line at 800-551-2333 to speak with a representative...
Get answers to your most pressing questions about US Legal Forms API.
How long does Montana Medicaid last?
Montana first enacted this policy for children covered under Medicaid/HMK. Since the start of Medicaid expansion in 2016, Montana's Medicaid program has had a policy of 12-month continuous eligibility for most adults receiving healthcare coverage.
What is the Montana State Dphhs phone number?
Public Health and Human Services General Information (406) 444-5622 111 North Sanders Helena, MT 59601-4520 PO Box 4210 Helena, MT 59604-4210 Department of Public Health and Human Services Organizational ChartFAX Number(406) 444-1970Websitedphhs.mt.govQuick Lookup:172 more rows
What is the income limit for Montana Medicaid?
Who is eligible for Montana Medicaid? Household Size*Maximum Income Level (Per Year)2$19,7203$24,8604$30,0005$35,1404 more rows
What is Medicaid called in Montana?
Montana's Medicaid program provides Montanans with low-incomes access to health care benefits and services based on their medical needs and life circumstances. Its Healthy Montana Kids program is the largest provider of health care for children in the state.
What is authorization to release information?
Generally, an authorization provides the authority for a doctor's release of PHI for specified purposes, which are generally other than treatment, payment, or healthcare operations, or, to disclose protected health information to a third party specified by the individual.
What is the medical privacy law in Montana?
Montana generally prohibits health care providers from disclosing a patient's health care information. There are important exceptions, however. Patients can authorize disclosure of health care information.
How do I contact Montana Medicaid?
Need help finding your local Office of Public Assistance, Enrolled Medicaid Provider, or Passport Provider? Call Montana Healthcare Programs, Member Help Line 1-800-362-8312, M-F, 8am-5pm, for assistance. Find a Montana Medicaid Provider.
What is the address for Montana Medicaid?
For electronic claims, the 160-M can either be faxed to 406.442. 4402 with the appropriate Paperwork Attachment Cover Sheet or mailed with the same cover sheet to Claims, P.O. Box 8000, Helena, MT 59604.
Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
If you believe that this page should be taken down, please follow our DMCA take down process here.