Loading
Form preview
  • US Legal Forms
  • Other Templates
  • More Forms
  • More Multi-State Forms
  • Health Claim Form 1500

Get Health Claim Form 1500

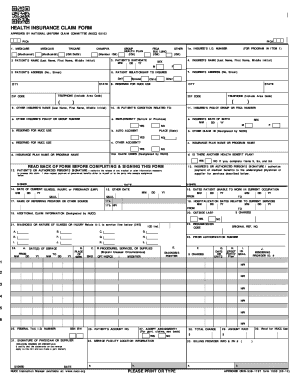
) (Member ID#) FECA BLK LUNG (ID#) 3. PATIENT'S BIRTHDATE MM DD YY 2 PATIENT'S NAME (Last Name, First Name, Middle Initial) 4. INSURED'S NAME (Last Name, First Name, Middle Initial) Self Spouse Child STATE 8. RESERVED FOR NUCC USE ( 7. INSURED'S ADDRESS (No, Street) Other CITY TELEPHONE (Include Area Code) ZIP CODE (FOR PROGRAM IN ITEM 1) F 6. PATIENT RELATIONSHIP TO INSURED CITY 1a. INSURED'S I.D. NUMBER (ID#) SEX M 5 PATIENT'S ADDRESS (No., Street) OTHER STATE TELEPHONE (.

How it works

  1. Open form

    Open form follow the instructions

  2. Easily sign form

    Easily sign the form with your finger

  3. Share form

    Send filled & signed form or save

How to fill out the Health Claim Form 1500 online

Filling out the Health Claim Form 1500 online can seem daunting, but it is an important step in processing your health insurance claims efficiently. This guide will walk you through each section of the form with clear and supportive instructions to help you complete it accurately.

Follow the steps to successfully fill out the Health Claim Form 1500 online.

  1. Click ‘Get Form’ button to obtain the form and open it in your preferred online editor.
  2. Begin by entering the patient’s name in the designated field for the Last Name, First Name, and Middle Initial.
  3. Fill in the patient’s birthdate using the MM, DD, YY format provided.
  4. Next, complete the purpose of insurance coverage, selecting from options such as Medicare, Medicaid, or other health plans in the appropriate section.
  5. Enter the insured person’s name in the Insured's Name field, as well as their relationship to the patient, selecting from options like Self, Spouse, or Child.
  6. Provide the insured's ID number, which may be found on their insurance card.
  7. Enter the insured's address, including the telephone number and ZIP code.
  8. If applicable, include information for any other insurance plans under the ‘Other Insured’s Name’ section, and indicate relationships to the patient.
  9. Continue filling out fields related to employment and accident details if the patient’s condition is related to any of these circumstances.
  10. Provide the dates related to any services; this includes dates of service and any hospitalization dates.
  11. Complete the section related to diagnosis, entering codes that correspond to the nature of the illness or injury.
  12. Make sure to sign the form in the designated signature fields, authorizing payment and release of information.
  13. Once all fields are completed, save your changes, then you can download, print, or share the form as needed.

Complete your Health Claim Form 1500 online today for efficient claims processing.

Get form

Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Get form

Related content

CMS-1500
payment of medical benefits to the undersigned physician or supplier for services...
Learn more
GHI Health Insurance Claim Form HCFA-1500
HEALTH INSURANCE CLAIM FORM. PICA. CHAMPVA. GROUP. FECA OTHER 19. INSURED'S I.D. NUMBER...
Learn more
Revised 1500 Claim Form Instructions - Molina...
by JB Doe — The National Uniform Claim Committee (NUCC) released a revised 1500 Claim...
Learn more

Related links form

TJ As A High School Option Interdisciplinary Scientist/Pharmacist , Division Of Dietary ... - Fda IBM Research Report Indexing Ontologies With Semantics-enhanced Keywords - Lirmm - Lirmm

Questions & Answers

Get answers to your most pressing questions about US Legal Forms API.

Contact support

A HCFA 1500 form is used by the Health Care Financing Administration. It is used for health care claims. It is used to submit a bill or charge for health insurance coverage.

The UB-04 (CMS 1450) is a claim form used by hospitals, nursing facilities, in-patient, and other facility providers. ... On the other hand, the HCFA-1500 (CMS 1500) is a medical claim form employed by individual doctors & practices, nurses, and professionals, including therapists, chiropractors, and out-patient clinics.

A health insurance claim is when you request reimbursement or direct payment for medical services that you have already obtained. ... The way to obtain benefits or payment is by submitting a claim via a specific form or request.

The UB-04 (CMS 1450) is a claim form used by hospitals, nursing facilities, in-patient, and other facility providers. ... On the other hand, the HCFA-1500 (CMS 1500) is a medical claim form employed by individual doctors & practices, nurses, and professionals, including therapists, chiropractors, and out-patient clinics.

The CMS-1500 form is the standard claim form used by a non-institutional provider or supplier to bill Medicare carriers and durable medical equipment regional carriers (DMERCs) when a provider qualifies for a waiver from the Administrative Simplification Compliance Act (ASCA) requirement for electronic submission of ...

In order to avail the cashless claim facility, the insured has to be treated in an empanelled hospital. ... Once the patient is discharged from the hospital, all the medical bills are sent to the insurance provider by the hospital. The insurance provider then evaluates the expenses and settles the payment.

A superbill is a detailed invoice outlining the services a client received. Therapists may need to generate a superbill when they are not on a client's insurance company's panel. The therapist or client submits the superbill directly to the insurer, giving the insurer all the information they need to pay the claim.

Form CMS-1500 is the standard paper claim form used to bill an insurance for rendered services and supplies. It provides information about the client, their corresponding insurance policy, and their diagnosis and treatment. Additionally, most insurances allow you to send an electronic version, called an 837 file.

A Superbill is used by healthcare providers as a primary source of data for creating claims. ... Essentially, a Superbill is an itemized list of all services provided to a client.

The CMS-1500 form is the standard claim form used by a non-institutional provider or supplier to bill Medicare carriers and durable medical equipment regional carriers (DMERCs) when a provider qualifies for a waiver from the Administrative Simplification Compliance Act (ASCA) requirement for electronic submission of ...

Get This Form Now!

Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
Get form
If you believe that this page should be taken down, please follow our DMCA take down processhere.
Get Health Claim Form 1500
Get form
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
  • Real Estate Handbook
  • All Guides
  • Notarize
  • Incorporation services
  • For Consumers
  • For Small Business
  • For Attorneys
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Form Packages
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
Form Categories
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
Customer Service
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
Legal Guides
  • Real Estate Handbook
  • All Guides
Prepared for you
  • Notarize
  • Incorporation services
Our Customers
  • For Consumers
  • For Small Business
  • For Attorneys
Our Sites
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Social Media
Call us now toll free:
+1 833 426 79 33
As seen in:
© Copyright 1999-2026 airSlate Legal Forms, Inc. 17 Station Street, Ste. 203, Brookline, MA 02445
  • Your Privacy Choices
  • Terms of Service
  • Privacy Notice
  • Content Takedown Policy
  • Bug Bounty Program