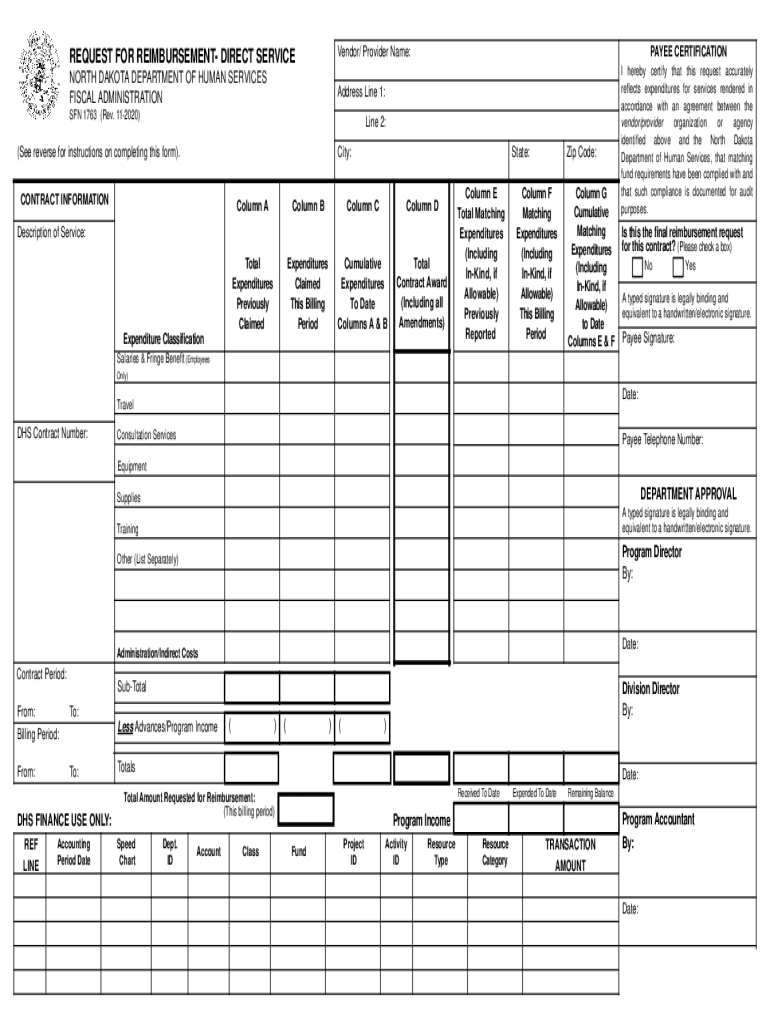
Vendor/ Provider Name REQUEST FOR REIMBURSEMENT- DIRECT SERVICE ND DEPARTMENT HUMAN SERVICES OF FISCAL ADMINISTRATION PAYEE CERTIFICATION Address Line 1 SFN 1763 Rev. 09-2005 Clear Fields Line 2 See reverse for instructions on completing this form. City CONTRACT INFORMATION State Column A Total Expenditures Previously Claimed This Billing Period Cumulative To Date Contract Award Including all Amendments Description of Service Total Matching In-Kind if Allowable Reported Zip Code Matching Salaries Fringe Benefit Employees I hereby certify that this request accurately reflects expenditures for services rendered in accordance with an agreement between the above and the North Dakota Department of Human Services that fund requirements have been complied with and that such compliance is documented for audit purposes. Is this the final reimbursement request Payee Signature Columns E F Date Only Payee Telephone Number Travel DHS Contract Number Consultation Services DEPARTMENT APPROVAL Equipme....

Open form follow the instructions

Easily sign the form with your finger

Send filled & signed form or save
How to fill out the ND SFN 1763 online
Filling out the ND SFN 1763 form online can streamline the reimbursement process for services provided under a contract with the North Dakota Department of Human Services. This guide offers a step-by-step approach to help users complete the form accurately and efficiently.
Follow the steps to fill out the ND SFN 1763 online.
- Click the ‘Get Form’ button to access the ND SFN 1763 form and open it in your preferred online editor.
- Begin by filling out the general information boxes. Enter the description of the services provided, the DHS contract number, contract period, billing period, vendor/provider name, and the complete mailing address. Make sure to input your city, state, and zip code accurately to ensure proper correspondence.
- In the columns, enter the total amounts previously claimed and the expenditures claimed for the current billing period. Ensure that you accurately total the amounts from columns A and B to provide a cumulative expenditure to date in column C.
- Record the total contract award encompassing all amendments in column D. Following that, enter any matching expenditures under columns E and F, inclusive of any in-kind contributions, if allowed.
- Input necessary adjustments such as advances and program income in the provided fields to reflect the net totals accurately. Sub-total your expenditures and adjust for any program income as indicated.
- Indicate whether this is your final reimbursement request for the contract by marking the appropriate box.
- Add your typed signature in the designated area, certifying that the request reflects accurate expenditures in line with your agreement with the North Dakota Department of Human Services. Include the date and contact number for follow-up.
- Once you have filled out all sections, review the information for accuracy, then save your changes. You can download, print, and share the completed form as needed.
Complete your ND SFN 1763 online today to ensure a smooth reimbursement process!
Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Related content
SFN 1763 (Rev. 12-2018). I hereby certify that this request accurately reflects...
The business cycle, also known as the economic cycle or trade cycle, is the downward and...
Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
If you believe that this page should be taken down, please follow our DMCA take down process here.