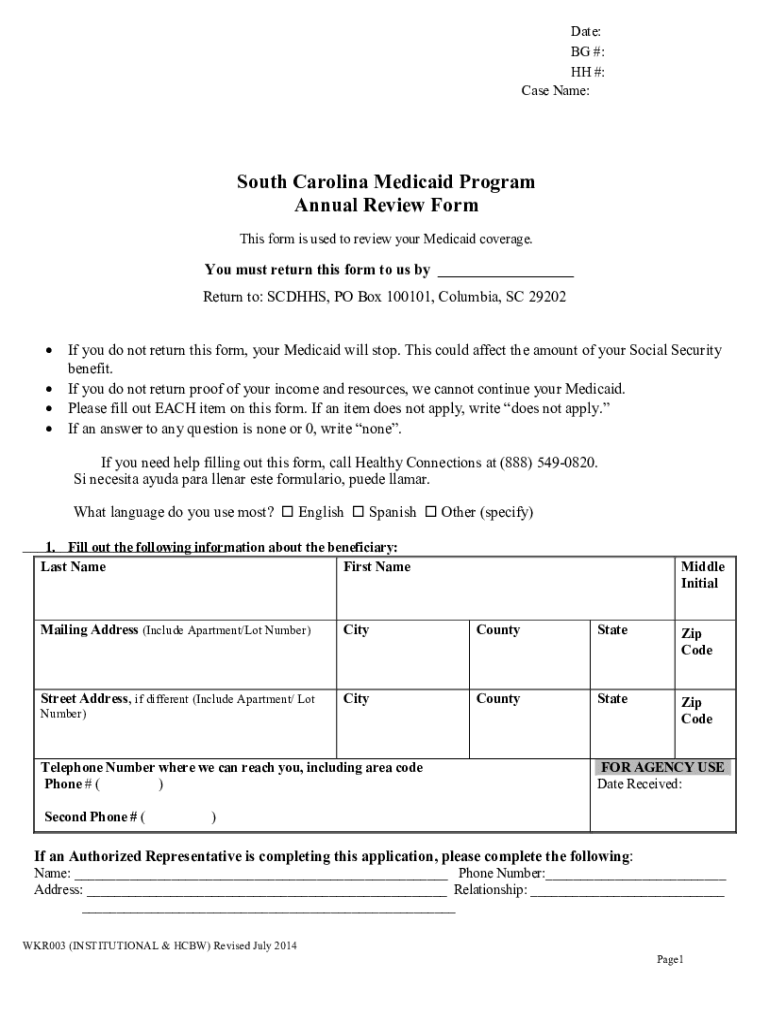
Date Worker Telephone BG HH Case Name South Carolina Medicaid Program Annual Review Form This form is used to review your Medicaid coverage. You must return this form to us by If you do not return this form your Medicaid will stop* This could affect the amount of your Social Security benefit. Please fill out EACH item on this form* If an item does not apply write does not apply. If an answer to any question is none or 0 write none. If you need help filling out this form call your worker listed above. Si necesita ayuda para llenar este formulario puede llamar a su trabajador cuyo nombre aparece arriba* What language do you use most English Spanish Other specify 1. Fill out the following information about the beneficiary Last Name First Name Middle Initial Mailing Address Include Apartment/Lot Number City County State Zip Code Street Address if different Include Apartment/ Lot Number Telephone Number where we can reach you including area code Phone Second Phone FOR AGENCY USE Date Receiv....
Loading

Open form follow the instructions

Easily sign the form with your finger

Send filled & signed form or save
How to fill out the SC WKR003 online
Filling out the SC WKR003 form online is an essential step in reviewing your Medicaid coverage. This guide provides detailed, step-by-step instructions to help users successfully complete the form.
Follow the steps to accurately complete the SC WKR003 form online.
- Press the ‘Get Form’ button to access the SC WKR003 document and open it in the online editor.
- Begin by filling out your personal information in the designated fields. This includes your last name, first name, middle initial, mailing address, city, county, state, and zip code. Ensure that your telephone number is also included.
- If an authorized representative is completing the application on your behalf, complete the section for that individual, including their name, phone number, address, and relationship.
- List your family members including your spouse and any dependent children. For each, provide their name, social security number, date of birth, and marital status.
- Indicate whether your spouse or dependent child works. If yes, fill in their gross pay before taxes and deductions. Remember to provide proof of income for the past four weeks.
- Detail any other income received by family members, including child support, alimony, social security income, and any additional sources. Make sure to attach proof of income listed.
- Answer questions about any adults in the home who are not currently working, and provide information about past bank account closures and any transfers of cash, property, or resources.
- Report on any assets or resources owned by family members, including bank accounts, property, and vehicles. Attach proof of the value of each item listed.
- Indicate any changes to private health insurance or long-term coverage and ensure you attach supporting documentation.
- Review all provided information for accuracy and completeness. Each item must be filled out; if a section does not apply to you, indicate 'does not apply'.
- After completing the form, save your changes and download or print a copy. Ensure you keep a record for your files, and return the completed form by the specified deadline.
Complete your SC WKR003 form online today to ensure continued Medicaid coverage.
Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Related content
Which Program are you receiving Medicaid for? Aged, Blind, or Disabled Individuals (ABD)...
Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
If you believe that this page should be taken down, please follow our DMCA take down process here.