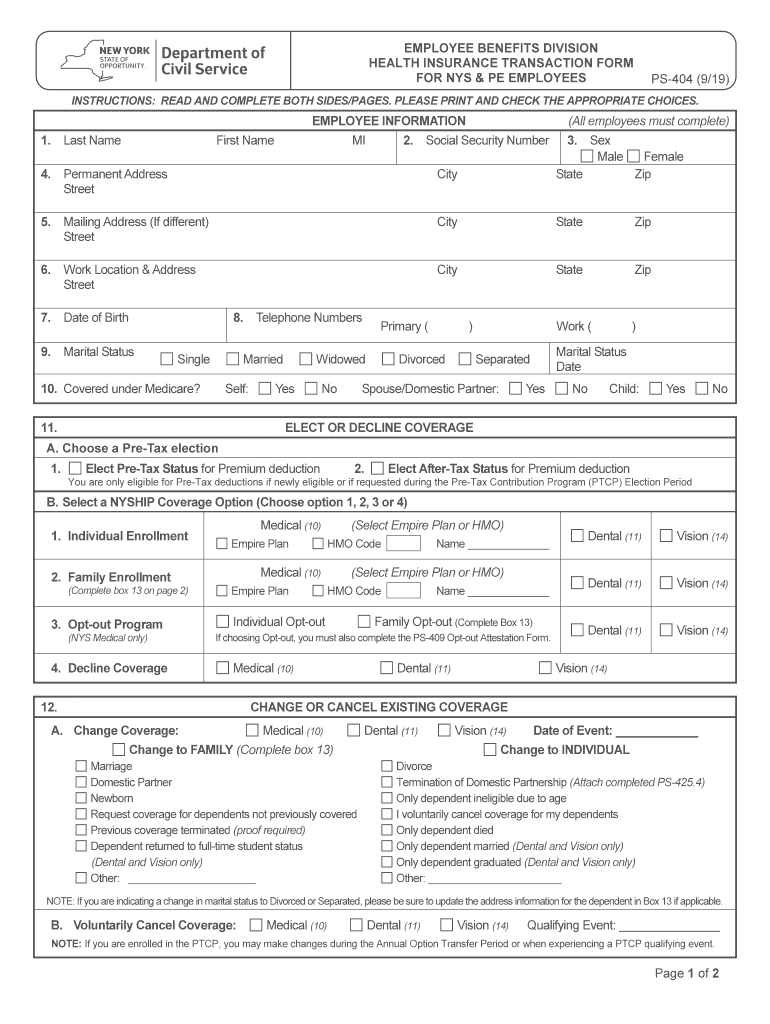
EMPLOYEE BENEFITS DIVISION HEALTH INSURANCE TRANSACTION FORM FOR NYS PE EMPLOYEES PS-404 9/17 INSTRUCTIONS READ AND COMPLETE BOTH SIDES/PAGES. PLEASE PRINT AND CHECK THE APPROPRIATE CHOICES. EMPLOYEE INFORMATION 1. Employee Signature Required AGENCY USE ONLY Retirement Tier Registration HBA Signature Required Sick Leave Information Hours Hourly Rate of Pay Date Entered on NYBEAS Effective Date Instructions for NYS Health Insurance Transaction Form NYSHIP Program Information Resources To enroll in benefits or to change your current benefits you will most likely be required to submit proofs of eligibility for coverage or evidence of a qualifying event with the completed and signed Health Insurance Transaction Form PS-404. B. Voluntarily Cancel Coverage Vision 14 Qualifying Event NYS Department of Civil Service Albany NY 12239 Health Insurance Transaction Form Page 2 - PS-404 9/17 DEPENDENT INFORMATION Must be provided when choosing to enroll or opt-out of NYSHIP family coverage use addit....

Open form follow the instructions

Easily sign the form with your finger

Send filled & signed form or save
How to fill out the NY PS-404 online
The NY PS-404 form is essential for employees participating in the New York State Health Insurance Program (NYSHIP). This guide offers clear, step-by-step instructions to help users complete the form accurately and effectively, ensuring that all necessary coverage choices are made.
Follow the steps to complete the NY PS-404 form online.
- Click ‘Get Form’ button to obtain the form and open it for editing.
- Provide your employee information in boxes 1 through 10. This includes your last name, first name, social security number, permanent address, date of birth, and contact details.
- Indicate your marital status in box 9. Select the appropriate option and write the date of your marital status if it is applicable.
- In box 11, choose whether to elect or decline coverage. Indicate your preference for medical, dental, and vision coverage, checking the appropriate boxes.
- For box 12, select whether you want to change your existing coverage or cancel it, if necessary. Provide any required event dates to document your request.
- Complete box 13 for dependent information, ensuring to include all necessary details such as names, dates of birth, and social security numbers of any dependents.
- In box 14, enter any requests for annual option transfer. Make sure to complete this section during the designated periods.
- Finally, review the authorization section. Ensure you sign and date the form, confirming that all information provided is accurate and truthful.
- Once completed, users can save changes, download, print, or share the form as required.
Complete your NY PS-404 form online today to ensure you have the necessary health insurance coverage.
Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Related content
No information is available for this page.Learn why
NYS HEALTH INSURANCE TRANSACTION FORM. PS-404 (3/17). INSTRUCTIONS: READ AND COMPLETE BOTH...
PS 804/954. 400 L2. PS 404. P5. PS 804 pg 95. P$ 1004/1154. COL: PS 0. F5 Tư ... PS 04...
Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
If you believe that this page should be taken down, please follow our DMCA take down process here.
This form is available in several versions. Select the version you need from the drop-down list below.