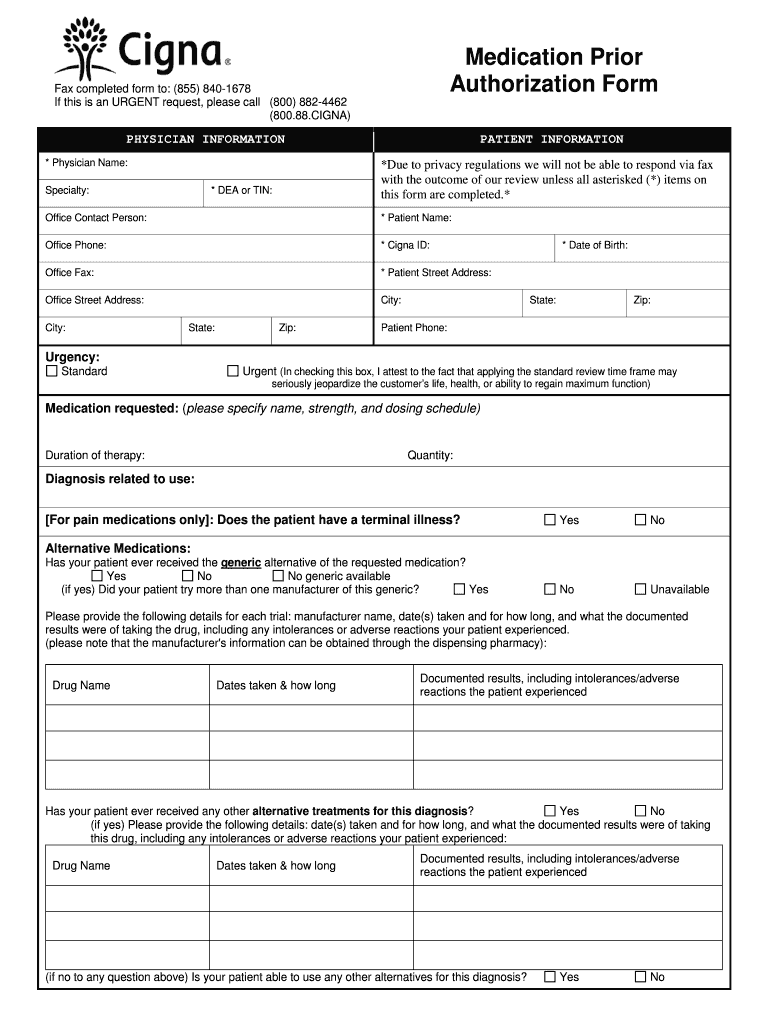
CIGNA HealthCare - Medication Prior Authorization Form Pharmacy Services Notice Failure to complete this form in its entirety may result in delayed processing or an adverse determination for insufficient information. Phone 800 244-6224 Fax 800 390-9745 PROVIDER INFORMATION PATIENT INFORMATION Provider Name Specialty Due to privacy regulations we will not be able to respond via fax with the outcome of our review unless all asterisked items on this form are completed DEA or TIN Office Contact Person Patient Name Office Phone CIGNA ID Office Fax Date Of Birth Is your fax machine kept in a secure location May we fax our response to your office Yes Office Street Address City No Patient Street Address State Zip Patient Phone Medication requested please specify name strength and dosing schedule Diagnosis related to use Duration of therapy Formulary alternatives tried please include length of trial and/or if samples were given Additional pertinent information please include clinical reasons fo....

Open form follow the instructions

Easily sign the form with your finger

Send filled & signed form or save
How to fill out the Cigna Medication Prior Authorization Form online
This guide provides clear instructions for users on completing the Cigna Medication Prior Authorization Form online. Following these steps will help ensure that all necessary information is accurately submitted for the approval process.
Follow the steps to successfully fill out the form.
- Press the ‘Get Form’ button to obtain the form and open it in your preferred editor.
- Begin by filling out the physician information section. Include the physician's name and specialty. Make sure to keep this information accurate for processing.
- In the patient information section, complete all required fields, marked with an asterisk (*), which include the patient’s name, date of birth, Cigna ID, address, and phone number.
- Indicate the urgency of the request by selecting either 'Standard' or 'Urgent.' If selecting 'Urgent,' add a note confirming that a delay could negatively impact the patient’s health.
- Fill in the medication requested, detailing the name, strength, and dosing schedule of the medication, as well as the duration of therapy and quantity needed.
- Describe the diagnosis related to the use of the medication. For pain medications, answer whether the patient has a terminal illness by selecting the appropriate option.
- Complete the alternative medications section by indicating if the patient has previously received a generic alternative. Indicate any specific trials taken, detailing drug names, dates, and results, if applicable.
- If the patient has tried other alternative treatments, provide the same level of detail as required for the previous section.
- If no alternatives are available, provide reasons why the patient is unable to use them in the space provided.
- Include any additional pertinent information that may support your patient’s request, such as clinical reasons and relevant lab values.
- Once all fields are complete, review the form for accuracy and clarity. Save the changes, download, print, or share the completed form as needed.
Submit your completed Cigna Medication Prior Authorization Form online for a streamlined process.
Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Related content
Prior Authorization Request Form for Health Care Services for Use in Indiana ... requires...
CIGNA HealthCare. - Medication Prior Authorization Form -. Notice: Failure to complete...
Mar 24, 2017 - 4.1 Prior authorization; 4.2 STEP therapy; 4.3 Appeals ... 2 novel...
Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
If you believe that this page should be taken down, please follow our DMCA take down process here.