Loading
Form preview
  • US Legal Forms
  • Other Templates
  • More Forms
  • More Uncategorized Forms
  • Wps Medicare Part B Redetermination Request Form. Wps Medicare Part B Redetermination Request Form

Get Wps Medicare Part B Redetermination Request Form. Wps Medicare Part B Redetermination Request Form

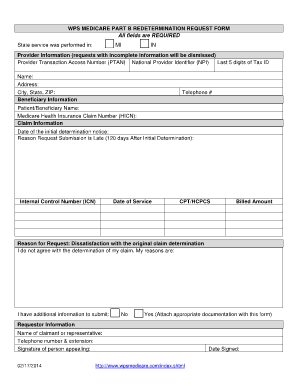
WPS MEDICARE PART B REDETERMINATION REQUEST FORM All fields are REQUIRED State service was performed in: MI IN Provider Information (requests with incomplete information will be dismissed) Provider.

How it works

  1. Open form

    Open form follow the instructions

  2. Easily sign form

    Easily sign the form with your finger

  3. Share form

    Send filled & signed form or save

How to fill out the WPS Medicare Part B Redetermination Request Form online

The WPS Medicare Part B Redetermination Request Form is essential for individuals seeking to contest a decision made on their claim. This guide will provide clear, step-by-step instructions to help users complete the form accurately and efficiently.

Follow the steps to complete your redetermination request.

  1. Click ‘Get Form’ button to obtain the form and open it for review.
  2. State where the service was performed by selecting your state from the options provided (MI or IN).
  3. In the provider information section, enter the required details, including the provider transaction access number (PTAN), national provider identifier (NPI), last five digits of the tax ID, name, address, city, state, and ZIP code.
  4. Fill in the beneficiary information by providing the patient's telephone number, name, and Medicare health insurance claim number (HICN).
  5. Complete the claim information section, including the date of the initial determination notice, reason for late submission (if applicable), internal control number (ICN), date of service, CPT/HCPCS code, and billed amount.
  6. Specify the reason for your request, indicating dissatisfaction with the original claim determination and detailing the reasons in the provided space.
  7. Indicate whether you have additional information to submit by selecting 'Yes' or 'No' and attach appropriate documentation if necessary.
  8. In the requestor information section, provide the name of the claimant or representative, telephone number and extension, and the signature of the person appealing along with the date signed.
  9. Finally, submit the completed form by faxing or mailing it to the appropriate address indicated on the form. Ensure you send it to the correct WPS Medicare Part B address for your state.

Ready to complete your WPS Medicare Part B Redetermination Request Form online? Start now!

Get form

Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Get form

Related content

First Level of Appeal: Redetermination by a...
Nov 15, 2019 — A redetermination is a review of the claim by Medicare Administrative...
Learn more
Medicare Overpayments - CMS
Request Immediate Recoupment: Occurs when Medicare recovers an ... Redetermination is the...
Learn more
The United States Government Manual...
Contact Us Privacy Accessibility Developed by: Government Printing Office | Digital...
Learn more

Related links form

Request For An Accounting Of Disclosures - Columbia University ... Alaska Wildland Journey Alaska Wildland Journey - Columbia Alumni ... - Alumni Columbia Exception Ordering Form For Desktop And Laptop Computers Traveler Information Name Net ID Address

Questions & Answers

Get answers to your most pressing questions about US Legal Forms API.

Contact support

You'll generally get a decision from the MAC (either in a letter or an MSN) called a "Medicare Redetermination Notice" within 60 days after they get your request. If you disagree with this decision, you have 180 days after you get the notice to request a reconsideration by a Qualified Independent Contractor (QIC).

What's it used for? Requesting an appeal (redetermination) if you disagree with Medicare's coverage or payment decision.

Third Level of Appeal: Decision by Office of Medicare Hearings and Appeals (OMHA) Any party that is dissatisfied with the Qualified Independent Contractor's (QIC's) reconsideration decision may request a hearing before an Administrative Law Judge (ALJ) with the Office of Medicare Hearings and Appeals (OMHA).

The appeals process consists of five levels. The appellant must begin the appeal at the first level after receiving an initial determination. Each level, after the initial determination, has procedural steps the Page 13 appellant must take before appealing to the next level.

Any party to the redetermination that is dissatisfied with the decision may request a reconsideration. A reconsideration is an independent review of the administrative record, including the initial determination and redetermination, by a Qualified Independent Contractor (QIC).

A redetermination must be requested in writing....Make a written request containing all of the following information: Beneficiary name. Medicare number. Specific service(s) and/or item(s) for which a redetermination is being requested. Specific date(s) of service. Name of the party, or the representative of the party.

A reconsideration consists of a review of an adverse organization determination, the evidence and findings upon which it was based, and any other evidence the parties submit or the MA organization or CMS obtains.

You must send your request to the QIC that will handle your reconsideration. The QIC's address is listed on the redetermination notice. You can submit additional information or evidence after the reconsideration request has been filed, but it may take longer for the QIC to make a decision.

Get This Form Now!

Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
Get form
If you believe that this page should be taken down, please follow our DMCA take down processhere.
Get WPS MEDICARE PART B REDETERMINATION REQUEST FORM. WPS MEDICARE PART B REDETERMINATION REQUEST FORM
Get form
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
  • Real Estate Handbook
  • All Guides
  • Notarize
  • Incorporation services
  • For Consumers
  • For Small Business
  • For Attorneys
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Form Packages
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
Form Categories
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
Customer Service
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
Legal Guides
  • Real Estate Handbook
  • All Guides
Prepared for you
  • Notarize
  • Incorporation services
Our Customers
  • For Consumers
  • For Small Business
  • For Attorneys
Our Sites
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Social Media
Call us now toll free:
+1 833 426 79 33
As seen in:
© Copyright 1999-2026 airSlate Legal Forms, Inc. 17 Station Street, Ste. 203, Brookline, MA 02445
  • Your Privacy Choices
  • Terms of Service
  • Privacy Notice
  • Content Takedown Policy
  • Bug Bounty Program