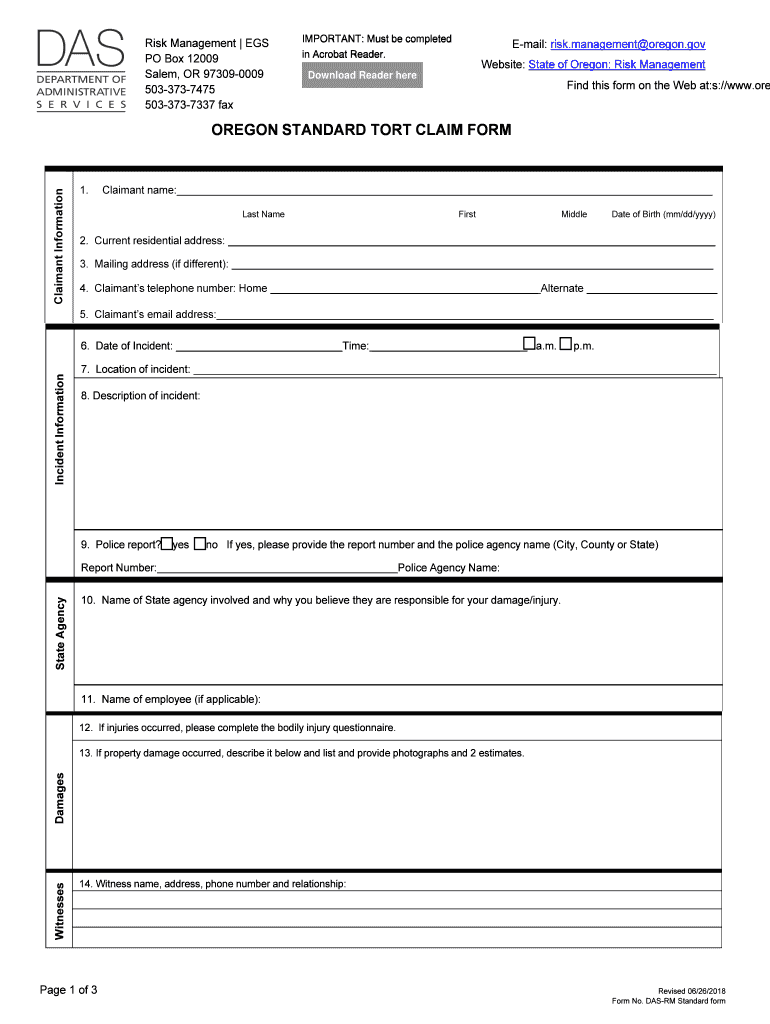
K.management oregon.gov Website: State of Oregon: Risk Management Download Reader here Find this form on the Web at: https://www.oregon.gov/das/Risk/Documents/Form AllClaimsNonAuto.pdf Claimant Information OREGON STAND ARD TORT CLAIM FORM 1. Claimant name: Last Name First Middle Date of Birth (mm/dd/yyyy) 2. Current residential address: 3. Mailing address (if different):.

Open form follow the instructions

Easily sign the form with your finger

Send filled & signed form or save
How to use or fill out the OR DAS-RM online
The OR DAS-RM, or Oregon Standard Tort Claim Form, is essential for individuals seeking to report claims related to damages or injuries involving state agencies. Filling out this form accurately and completely ensures your claim is processed efficiently.
Follow the steps to successfully complete the OR DAS-RM online.
- Press the ‘Get Form’ button to access the OR DAS-RM form and open it in your preferred editor.
- Provide your complete name, including your last name, first name, and middle name, followed by your date of birth in the specified format (mm/dd/yyyy).
- Enter your current residential address and, if different, your mailing address.
- Fill in your primary telephone number and an alternate contact number.
- List your email address for any necessary communication regarding your claim.
- Record the date and time of the incident, ensuring to specify whether it occurred in the a.m. or p.m.
- Detail the location of the incident in the designated field.
- Provide an accurate description of the incident, including any relevant details.
- State whether a police report was filed; if yes, supply the report number and the name of the police agency involved.
- Indicate the name of the state agency involved in your claim and explain why you believe they are responsible.
- If applicable, include the name of the employee associated with the claim.
- If you experienced injuries, complete the bodily injury questionnaire by providing your last name, first name, date of birth, and gender.
- Answer whether the incident is related to an auto accident and, if applicable, specify your seating position in the vehicle.
- Indicate whether you used a seatbelt and if the airbag deployed during the incident.
- Thoroughly describe your injury and record when you first noticed it. Mention any medical treatment you sought and list the medical providers visited.
- Estimate the total amount of medical costs incurred to date and indicate if future treatment is expected.
- Provide information on any prior injuries to the affected body part.
- Complete any additional information you think is relevant to your claim.
- Review your responses for accuracy, then save changes. You may download, print, or share the form if needed.
Complete your claim form online today to ensure timely processing.
Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Related content
Management (DAS RM) to direct and manage all risk management and insurance pro- grams of...
L. Farhadi, S.N Ricketts, M.J. Rust, M. Das, R.M. Robertson-Anderson, J.L. Ross. Soft...
Jan 18, 2017 — ... ADRF KOREA, Inc.. Document Includes User Manual ADXV DAS User Manual...
Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
If you believe that this page should be taken down, please follow our DMCA take down process here.