Loading
Form preview
  • US Legal Forms
  • Other Templates
  • More Forms
  • More Uncategorized Forms
  • Health Care Claim Form Pdf

Get Health Care Claim Form Pdf

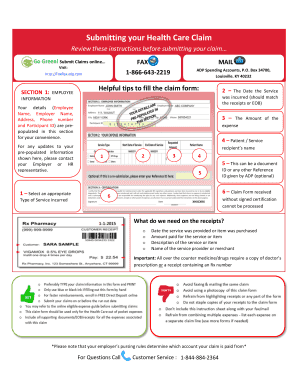
Submitting your Health Care Claim Review these instructions before submitting your claim Go Green! Submit Claims online Helpful tips for documentation: Visit: FAX 18666432219 MAIL Ensure that the.

How it works

  1. Open form

    Open form follow the instructions

  2. Easily sign form

    Easily sign the form with your finger

  3. Share form

    Send filled & signed form or save

How to fill out the Health Care Claim Form PDF online

Filling out the Health Care Claim Form PDF online can streamline the reimbursement process for your eligible medical expenses. This guide will walk you through each section of the form, ensuring a smooth and accurate submission.

Follow the steps to complete the Health Care Claim Form online.

  1. Click the ‘Get Form’ button to obtain the form, and open it in your preferred editor.
  2. Review the pre-populated Employee Information section, which includes your name, employer, address, phone number, and participant ID. Ensure that this information is accurate; if any details require updating, contact your employer or HR representative.
  3. In the Expense Information section, provide the date of the service incurred, ensuring it matches the receipts or Explanation of Benefits (EOB). Fill in the amount of the expense along with the patient's name who received the service.
  4. Select the appropriate type of service from the options provided, which may include medical, vision, dental, or prescription. Make sure to check the box that corresponds to each claimed expense.
  5. Attach any necessary documentation, such as itemized receipts or EOBs. Remember that all over-the-counter medicines require a corresponding prescription or a receipt containing an Rx number.
  6. Sign and date the certification section, confirming that the expenses claimed have not been reimbursed and understand the terms outlined in the form.
  7. Once all sections are completed, save the changes made to the form. You can then print, download, or share the form as needed to submit it according to your preferred method.

Complete your Health Care Claim Form online today for a faster reimbursement process.

Get form

Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Get form

Related content

health insurance claim form - CDC
payment of medical benefits to the undersigned physician or supplier for services...
Learn more
Claim Form Manual V7 0 7 11 - UserManual.wiki
The 1500 Health Insurance Claim Form (1500 Claim Form) is in the public domain. ... 5010...
Learn more

Related links form

Corporate Master Wakala Agreement For Investment... History Of Life Webquest Answer Key Field Hockey Coaching Manual Entry Form (Individual) - Judo.or.jp

Questions & Answers

Get answers to your most pressing questions about US Legal Forms API.

Contact support

The UB-04 (CMS-1450) form is the claim form for institutional facilities such as hospitals or outpatient facilities. This would include things like surgery, radiology, laboratory, or other facility services. The HCFA-1500 form (CMS-1500) is used to submit charges covered under Medicare Part B.

Before filing a claim, it's important to know which form to use in order to get proper reimbursement. CMS-1500 & UB-04 are the most common claim forms submitted to the insurance companies.

Also known as the Healthcare Financing Administration (HCFA) form, the CMS-1500 form is used for claim reimbursement for several government insurance plans such as Medicaid, Tricare, and Medicare.

In order to purchase claim forms, you should contact the U.S. Government Printing Office at 1-866-512-1800, local printing companies in your area, and/or office supply stores. Each of the vendors above sells the CMS-1500 claim form in its various configurations (single part, multi-part, continuous feed, laser, etc).

In SimplePractice, you can generate CMS 1500 claim forms to submit electronically through the system, or download and print to submit outside the system.

The Referring Provider is the individual who directed the patient for care to the provider rendering the services being reported.

The CMS-1500 form is the standard claim form used by a non-institutional provider or supplier to bill Medicare carriers and durable medical equipment regional carriers (DMERCs) when a provider qualifies for a waiver from the Administrative Simplification Compliance Act (ASCA) requirement for electronic submission of ...

Both the CMS-1500 and UB-04 forms contain many of the same boxes that need to be filled out including patient demographics, provider identification information, procedures and charges and insurance plan identification information. The more information you can provide to the patient's insurance company, the better.

Get This Form Now!

Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
Get form
If you believe that this page should be taken down, please follow our DMCA take down processhere.
Get Health Care Claim Form PDF
Get form
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
  • Real Estate Handbook
  • All Guides
  • Notarize
  • Incorporation services
  • For Consumers
  • For Small Business
  • For Attorneys
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Form Packages
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
Form Categories
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
Customer Service
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
Legal Guides
  • Real Estate Handbook
  • All Guides
Prepared for you
  • Notarize
  • Incorporation services
Our Customers
  • For Consumers
  • For Small Business
  • For Attorneys
Our Sites
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Social Media
Call us now toll free:
+1 833 426 79 33
As seen in:
© Copyright 1999-2026 airSlate Legal Forms, Inc. 17 Station Street, Ste. 203, Brookline, MA 02445
  • Your Privacy Choices
  • Terms of Service
  • Privacy Notice
  • Content Takedown Policy
  • Bug Bounty Program