Loading
Form preview
  • US Legal Forms
  • Other Templates
  • More Forms
  • More Uncategorized Forms
  • Retroactive Health Care Coverage Request Form Magi Medicaid - Hca Wa

Get Retroactive Health Care Coverage Request Form Magi Medicaid - Hca Wa

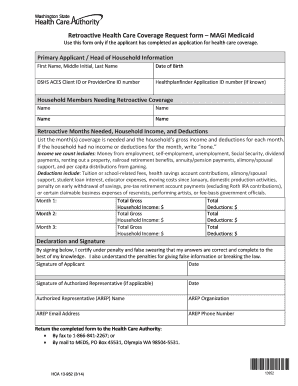
Retroactive Health Care Coverage Request form MAGI Medicaid Use this form only if the applicant has completed an application for health care coverage. Primary Applicant / Head of Household Information.

How it works

  1. Open form

    Open form follow the instructions

  2. Easily sign form

    Easily sign the form with your finger

  3. Share form

    Send filled & signed form or save

How to fill out the Retroactive Health Care Coverage Request Form MAGI Medicaid - Hca Wa online

This guide provides comprehensive instructions on filling out the Retroactive Health Care Coverage Request Form for MAGI Medicaid online. Whether you are new to the process or need a refresher, this step-by-step guidance will help you complete the form accurately.

Follow the steps to successfully fill out your form.

  1. Click ‘Get Form’ button to access the Retroactive Health Care Coverage Request Form MAGI Medicaid.
  2. Begin by entering personal information for the primary applicant or head of household. Fill in the first name, middle initial, last name, date of birth, DSHS ACES client ID or ProviderOne ID number, and healthplanfinder application ID number if known.
  3. List household members who need retroactive coverage. Provide the names of each individual requiring coverage.
  4. Specify the retroactive months needed. For each month, indicate the household’s gross income and any applicable deductions. If there is no income or deductions for a particular month, clearly write “none.”
  5. For each month listed, ensure you accurately report the total gross household income and deductions as required. Remember to include all necessary income sources and deductions stated in the form instructions.
  6. Complete the declaration and signature section. By signing, you certify that the information provided is accurate to the best of your knowledge. If applicable, have your authorized representative fill in their information as well.
  7. Review the completed form for accuracy before submission. Once satisfied with all entered information, you can save, download, print, or otherwise share the form, as needed.

Start filling out your Retroactive Health Care Coverage Request Form MAGI Medicaid online today.

Get form

Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Get form

Related content

Retroactive health care coverage request form...
Return the completed form to the Health Care Authority: • By fax to 1-866-841-2267; or...
Learn more
UnitedHealthCare Group Medicare Advantage PPO - HR...
Public Employees' Medical & Hospital Care Act (PEMHCA) ... Social Security, Medicaid (the...
Learn more

Related links form

CA JV-433 2023 CA AT-167/EJ-152 2022 CA JV-440 2023 Partnering With Pfizer Worldwide R&D Brochure 2017

Questions & Answers

Get answers to your most pressing questions about US Legal Forms API.

Contact support

Depending on how you apply, you can find out right away if you are eligible for Medicaid coverage. In some cases, it could take the state up to 45 days. Once you are approved for Medicaid, you'll receive a welcome packet from the state.

Q. Can I use my Medicaid coverage in any state? A: No. Because each state has its own Medicaid eligibility requirements, you can't just transfer coverage from one state to another, nor can you use your coverage when you're temporarily visiting another state, unless you need emergency health care.

Retroactive coverage is available for up to 3 months before you apply for the program as long as you met the eligibility requirements during that time. If eligible, you will need to pay premiums for the retroactive coverage.

Medicaid does not pay money to you. It sends payments directly to your health care providers. Medicaid can pay for medical services in your own home or if you live in a residential care facility that takes Medicaid residents. Learn more about how to apply for Medicaid.

Children (18 & under)–Apple Health eligibility Total number in family (children and adults)Monthly income limit for free coverageMonthly income limit: $20 per month fee1$2,612$3,2202$3,533$4,3553$4,454$5,4904$5,375$6,6252 more rows

You may still be eligible for Washington Apple Health Classic Medicaid coverage, even if you have Medicare coverage. This coverage could include Apple Health coverage, help paying for Medicare premiums, or long-term services and supports.

Blind, or. Have a disability or a family member in your household with a disability, or. Be 65 years of age or older....Who is eligible for Washington Medicaid? Household Size*Maximum Income Level (Per Year)1$19,3922$26,2283$33,0644$39,9004 more rows

Get This Form Now!

Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
Get form
If you believe that this page should be taken down, please follow our DMCA take down processhere.
Get Retroactive Health Care Coverage Request Form MAGI Medicaid - Hca Wa
Get form
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
  • Real Estate Handbook
  • All Guides
  • Notarize
  • Incorporation services
  • For Consumers
  • For Small Business
  • For Attorneys
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Form Packages
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
Form Categories
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
Customer Service
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
Legal Guides
  • Real Estate Handbook
  • All Guides
Prepared for you
  • Notarize
  • Incorporation services
Our Customers
  • For Consumers
  • For Small Business
  • For Attorneys
Our Sites
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Social Media
Call us now toll free:
+1 833 426 79 33
As seen in:
© Copyright 1999-2026 airSlate Legal Forms, Inc. 17 Station Street, Ste. 203, Brookline, MA 02445
  • Your Privacy Choices
  • Terms of Service
  • Privacy Notice
  • Content Takedown Policy
  • Bug Bounty Program