Loading
Get Pyramids Pharmacy Dermatology Enrollment Form (p-s)
How it works
-

Open form follow the instructions
-

Easily sign the form with your finger
-

Send filled & signed form or save
How to fill out the Pyramids Pharmacy Dermatology Enrollment Form (P-S) online
Completing the Pyramids Pharmacy Dermatology Enrollment Form (P-S) online can be a straightforward process with the right guidance. This guide provides a step-by-step approach to ensure that you fill out each section accurately and efficiently.
Follow the steps to complete the form successfully.
- Click the ‘Get Form’ button to access the document and open it in your selected editor.
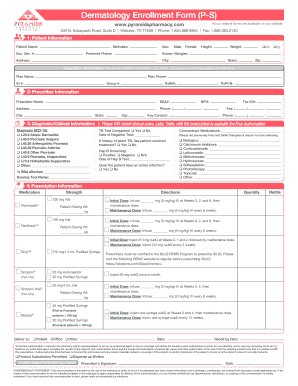
- Begin with the Patient Information section. Fill in the patient’s full name, birthdate, social security number, and preferred phone number. Indicate the patient’s sex and record height and weight in either pounds or kilograms. Add known allergies and the patient’s address, including city, state, and zip code.
- In the Insurance Information section, provide the plan name and phone number. You will need to fax a copy of both the front and back of all insurance cards, including prescription and medical cards. Fill in the ID number, group number, RxBIN, and RxPCN.
- Move to the Prescriber Information section. Enter the prescriber’s name, DEA number, NPI number, and their contact information including address, phone number, and fax number. Include the prescriber’s tax ID number and key contact.
- Next, complete the Diagnosis/Clinical Information section. Indicate the diagnosis using the ICD-10 codes provided. Select the appropriate options for TB test completion and document the date of the negative test if applicable. Include details about any concomitant medications.
- List previously tried and failed therapies in the designated area along with the reasons for discontinuation. Indicate the result of the Hep B screening and provide the date of the Hep B test.
- In the Medication section, select the medication, specify the strength, and provide the necessary information regarding patient dosing and directions for use. Document the quantity and refills as required.
- Specify the delivery preference in the designated area, indicating whether the medication should be delivered to the patient, office, or another party. Enter the needs by date for the prescription.
- Prescriber's authorization is required. Check the appropriate boxes for product substitution and sign at the bottom, ensuring the prescriber’s signature is authentic.
- Once you have filled out all necessary fields, review the form for accuracy. You can then save your changes, download, print, or share the completed enrollment form as needed.
Get started on completing your documents online today!