Loading
Form preview
  • US Legal Forms
  • Other Templates
  • More Forms
  • More Multi-State Forms
  • Empire Station, Po Box 2052

Get Empire Station, Po Box 2052

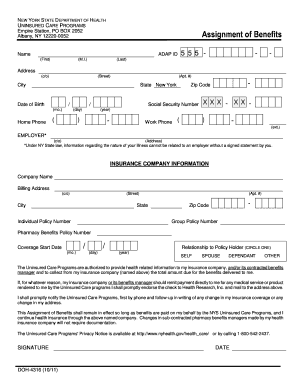
NEW YORK STATE DEPARTMENT OF HEALTHUNINSURED CARE PROGRAMS Empire Station, PO BOX 2052 Albany, NY 122200052Assignment of BenefitsName5 5 5 ADAP ID (First)(M.I.)(Last)Address (c/o)(Street)(Apt. #)CityState.

How it works

  1. Open form

    Open form follow the instructions

  2. Easily sign form

    Easily sign the form with your finger

  3. Share form

    Send filled & signed form or save

How to fill out the Empire Station, PO BOX 2052 online

This guide will assist you in completing the Empire Station, PO BOX 2052 form efficiently online. By following these steps, you will be able to accurately fill out the required information without confusion.

Follow the steps to fill out the Empire Station form online.

  1. Press the ‘Get Form’ button to access the form and open it for completion.
  2. Begin by providing your name in the designated fields. Enter your first name, middle initial, and last name as they appear on official documents.
  3. Next, fill in your address information, including street address, apartment number (if applicable), city, state (New York), and zip code.
  4. Input your date of birth in the requested format, as well as your home and work phone numbers. Include the area code for each phone number.
  5. Provide your Social Security number in the appropriate fields, ensuring to separate each segment with dashes as indicated.
  6. List your employer's name and address if applicable. Remember that under New York State law, certain medical information cannot be disclosed to your employer without your signed consent.
  7. Next, complete the insurance company information section. Include the company's name, billing address, individual policy number, group policy number, and pharmacy benefits policy number.
  8. Indicate the coverage start date and confirm your relationship to the policyholder by circling one of the provided options: self, spouse, dependent, or other.
  9. Review the Assignment of Benefits statement and understand your responsibilities regarding payment remittance and notifying the Uninsured Care Programs of any changes to your coverage or address.
  10. Finally, provide your signature and the date at the bottom of the form to certify that the information provided is accurate.
  11. After completing all sections accurately, save your changes, download the form, print it, or share it as necessary to ensure submission.

Complete your form online today to ensure timely processing of your application.

Get form

Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Get form

Related content

Uninsured Care Programs ADAP Plus Agreement Form
Empire Station, P.O. Box 2052,. Albany, NY 12220-0052 ... ADAP Plus serves HIV-infected...
Learn more
Application & Instructions for the HIV Uninsured...
Empire Station. P.O. Box 2052. Albany, NY 12220-0052. 1-800-542-2437. Application &...
Learn more
store number
2209 STATE ST. NEW ALBANY ... 715 BLUE RIVER HWY, PO BOX 26870 SILVERTHORNE ... 2052...
Learn more

Related links form

The Autobiography Of Fbi Agent Dale Cooper Epub 2020 Memorandum Of Understanding NCW - Rockingham County Schools - Rock K12 Nc 2020 Kumon Answer Book Level G 2020 SMHS School Profile - Charlotte-Mecklenburg Schools - Schools Cms K12 Nc 2020

Questions & Answers

Get answers to your most pressing questions about US Legal Forms API.

Contact support

The AIDS Drug Assistance Program (ADAP) is a statewide, federally funded prescription medication program for low-income people living with HIV. This program provides access to medications to eligible uninsured clients or by purchase of health insurance that includes coverage for HIV medications.

Required Documentation Income Verification (one or more of the following): Three (3) current paycheck stubs. Three (3) current bank statements. SSI or SSDI letter.

The AIDS Drug Assistance Program (ADAP) provides free medications for the treatment of HIV/AIDS and opportunistic infections. The drugs provided through ADAP can help people with HIV/AIDS to live longer and treat the symptoms of HIV infection.

For questions regarding your ADAP and ADAP Plus coverage, call 1-800-542-2437 or 1-844-682-4058.

ADAP can help people with no insurance, partial insurance, Medicaid Spend-down/Surplus or Medicare Part D. ADAP Plus (Primary Care)pays for outpatient primary care services through participating clinics, hospitals, laboratory providers, and private practitioners.

The AIDS Drug Assistance Program (ADAP) is a statewide, federally funded prescription medication program for low-income people living with HIV. This program provides access to medications to eligible uninsured clients or by purchase of health insurance that includes coverage for HIV medications.

Eligibility Criteria Medical: HIV-infection or at risk of acquiring HIV infection consistent with the guidelines for Pre-Exposure Prophylaxis. Residency: New York State (U.S. citizenship is not required.) Financial: Financial eligibility is based on 500% of the Federal Poverty Level (FPL).

Dental and Vision Plans: Dental plans can be covered only if a client is already enrolled in OA-HIPP for a health insurance plan. Vision insurance can also be paid but only if included as part of a combined health or dental plan.

Get This Form Now!

Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
Get form
If you believe that this page should be taken down, please follow our DMCA take down processhere.
Get Empire Station, PO BOX 2052
Get form
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
  • Real Estate Handbook
  • All Guides
  • Notarize
  • Incorporation services
  • For Consumers
  • For Small Business
  • For Attorneys
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Form Packages
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
Form Categories
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
Customer Service
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
Legal Guides
  • Real Estate Handbook
  • All Guides
Prepared for you
  • Notarize
  • Incorporation services
Our Customers
  • For Consumers
  • For Small Business
  • For Attorneys
Our Sites
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Social Media
Call us now toll free:
+1 833 426 79 33
As seen in:
© Copyright 1999-2026 airSlate Legal Forms, Inc. 17 Station Street, Ste. 203, Brookline, MA 02445
  • Your Privacy Choices
  • Terms of Service
  • Privacy Notice
  • Content Takedown Policy
  • Bug Bounty Program