Loading
Form preview
  • US Legal Forms
  • Other Templates
  • More Forms
  • More Multi-State Forms
  • Wellnet Individual Medical Questionnaire 2014

Get Wellnet Individual Medical Questionnaire 2014-2026

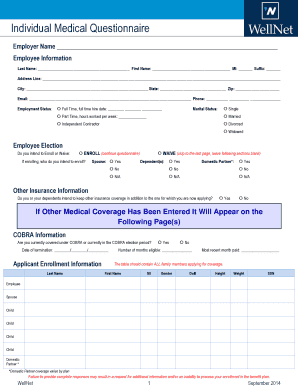
Individual Medical Questionnaire Employer Name Employee Information Last Name: First Name: MI: Suffix: Address Line: City: State: Zip: Email: Phone: Employment Status: Full Time, full time hire date:.

How it works

  1. Open form

    Open form follow the instructions

  2. Easily sign form

    Easily sign the form with your finger

  3. Share form

    Send filled & signed form or save

How to fill out the WellNet Individual Medical Questionnaire online

The WellNet Individual Medical Questionnaire is a crucial document for individuals seeking medical benefits coverage. This guide provides clear, step-by-step instructions to help users navigate the form efficiently and accurately.

Follow the steps to complete the form successfully.

  1. Press the ‘Get Form’ button to access the WellNet Individual Medical Questionnaire and open it in your preferred online editor.
  2. Begin by filling out the employer name at the top of the form to identify the company associated with your coverage.
  3. Complete the employee information, including your last name, first name, middle initial, suffix, complete address, city, state, zip code, email, and phone number.
  4. Indicate your employment status by checking the appropriate box and providing the required date for full-time employees.
  5. Select your marital status by choosing one of the available options: single, married, divorced, or widowed.
  6. In the employee election section, indicate whether you intend to enroll or waive coverage. If enrolling, specify if you will include your spouse, dependents, or domestic partner.
  7. Answer the other insurance information questions. If applicable, list any family members maintaining additional insurance coverage and provide insurance company names and policy numbers.
  8. Provide any relevant COBRA information regarding your current coverage status and related dates.
  9. For the applicant enrollment information, list all family members applying for coverage, including their personal details such as first name, middle initial, gender, date of birth, height, weight, and social security number.
  10. Fill out the required medical information section by carefully answering all questions regarding your and your dependents' health conditions and medical history.
  11. In the authorization section, confirm your understanding and agreement to release medical information as required for eligibility determination.
  12. Check the appropriate box for waiving coverage, if applicable, and provide a reason if necessary.
  13. Finish by signing and dating the form. If someone else is signing on your behalf, indicate their authority.
  14. Finally, review all provided information for accuracy before saving changes, downloading, printing, or sharing the completed form.

Complete your WellNet Individual Medical Questionnaire online today!

Get form

Experience a faster way to fill out and sign forms on the web. Access the most extensive library of templates available.
Get form

Related content

Cohort Profile: Effectiveness of a 12-Month...
by JR John · 2020 · Cited by 9 — The broader aim of the WellNet study is to evaluate...
Learn more
2011 - Alabama Department of Public Health (ADPH)
by PN Trotter — The HAI Program staff conducted validation of HAI data submitted by...
Learn more
economic report president - The White House [PDF]...
I have met small business owners struggling to pay for health care for their workers;...
Learn more

Related links form

High School Student Sponsorship Form High School Student ... Antisteering Form Tna 2020 Ivy Tech Qma Practice Test

Questions & Answers

Get answers to your most pressing questions about US Legal Forms API.

Contact support

WELLNET HEALTHCARE is honored to provide third party administrative services to its clients and their workforce. We value the trust placed in us and we are committed to maintaining your trust and confidence in our products and services.

Payer Name: WellNet|Payer ID: 41124|Professional (CMS1500)/Institutional (UB04)[Hospitals]

Definition of 'health questionnaire' A health questionnaire is a list of questions about someone's health issued by underwriters before accepting a person as a risk. Failure to volunteer full information on a health questionnaire can result in coverage being voided during a claim.

* Timely enrollment occurs within 31 days, or as allowed under the Plan, from the date a person is eligible for coverage.

Get This Form Now!

Use professional pre-built templates to fill in and sign documents online faster. Get access to thousands of forms.
Get form
If you believe that this page should be taken down, please follow our DMCA take down processhere.
Get WellNet Individual Medical Questionnaire
Get form
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
  • Real Estate Handbook
  • All Guides
  • Notarize
  • Incorporation services
  • For Consumers
  • For Small Business
  • For Attorneys
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Form Packages
  • Adoption
  • Bankruptcy
  • Contractors
  • Divorce
  • Home Sales
  • Employment
  • Identity Theft
  • Incorporation
  • Landlord Tenant
  • Living Trust
  • Name Change
  • Personal Planning
  • Small Business
  • Wills & Estates
  • Packages A-Z
Form Categories
  • Affidavits
  • Bankruptcy
  • Bill of Sale
  • Corporate - LLC
  • Divorce
  • Employment
  • Identity Theft
  • Internet Technology
  • Landlord Tenant
  • Living Wills
  • Name Change
  • Power of Attorney
  • Real Estate
  • Small Estates
  • Wills
  • All Forms
  • Forms A-Z
  • Other Templates
Customer Service
  • Legal Hub
  • About Us
  • Help Portal
  • Legal Resources
  • Blog
  • Affiliates
  • Contact Us
  • Delete My Account
  • Site Map
  • Industries
  • Forms in Spanish
  • Localized Forms
  • State-specific Forms
  • Forms Kit
Legal Guides
  • Real Estate Handbook
  • All Guides
Prepared for you
  • Notarize
  • Incorporation services
Our Customers
  • For Consumers
  • For Small Business
  • For Attorneys
Our Sites
  • USLegal
  • FormsPass
  • pdfFiller
  • signNow
  • altaFlow
  • DocHub
  • Instapage
Social Media
Call us now toll free:
+1 833 426 79 33
As seen in:
© Copyright 1999-2026 airSlate Legal Forms, Inc. 17 Station Street, Ste. 203, Brookline, MA 02445
  • Your Privacy Choices
  • Terms of Service
  • Privacy Notice
  • Content Takedown Policy
  • Bug Bounty Program