Loading
Get Form Approved Omb No 0938 0357
How it works
-

Open form follow the instructions
-

Easily sign the form with your finger
-

Send filled & signed form or save
How to fill out the Form Approved OMB No 0938 0357 online
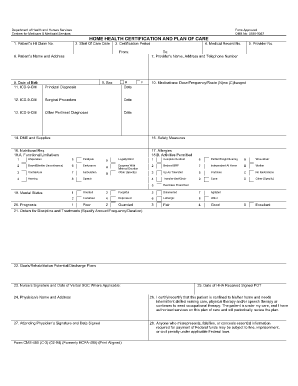
Filling out the Form Approved OMB No 0938 0357, also known as the Home Health Certification and Plan of Care, is an essential task for healthcare providers. This guide will provide you with clear, step-by-step instructions on how to complete the form online efficiently and accurately.
Follow the steps to complete the Home Health Certification and Plan of Care form.
- Use the ‘Get Form’ button to obtain the form and load it in your online editor.
- Begin by entering the patient’s Health Insurance Claim Number (HI Claim No.) in the designated field.
- Specify the Start of Care Date. This should reflect the first day the patient will begin receiving care.
- Input the Medical Record Number, which is unique to the patient’s records within the healthcare facility.
- Indicate the Certification Period, specifying both the start and end dates.
- Provide the provider's name, address, and telephone number in the respective fields.
- Fill in the Date of Birth for the patient and ensure the information matches official records.
- Provide the principal diagnosis using the ICD-9-CM code and the corresponding date.
- Indicate the patient's sex and provide the date on which this information is recorded.
- Input any surgical procedures associated with the patient using the appropriate ICD-9-CM code.
- If applicable, document other pertinent diagnoses with their respective ICD-9-CM codes and dates.
- List the medications, detailing the dosage, frequency, and route, marking whether they are new or changed.
- Mention any durable medical equipment (DME) and supplies that the patient may require.
- Describe any safety measures that need to be implemented for the patient.
- Detail any nutritional requirements for the patient.
- Specify any functional limitations the patient has, selecting appropriate options from the list provided.
- Document any known allergies that the patient has.
- Indicate the activities that the patient is permitted to engage in.
- Assess and report the patient’s mental status based on the options available.
- Describe the prognosis for the patient with any specific comments.
- Document orders for discipline and treatments, including amount, frequency, and duration.
- Clearly outline the goals, rehabilitation potential, and discharge plans for the patient.
- Ensure the nurse’s signature and date of the verbal Start of Care (SOC) is documented where applicable.
- Input the date the Home Health Agency (HHA) received the signed plan of care.
- Provide the attending physician's name and address in the relevant section.
- Ensure the attending physician's signature and date is present as part of the certification.
- Finally, review all provided information for accuracy, and ensure that any necessary disclaimers are acknowledged.
Complete your Home Health Certification and Plan of Care form online today for confident and efficient submission.
What is the Home Health Certification and Plan of Care for? The form CMS-485 is used by the HHA Home Health Care Agency to serve as a plan of care and certification or recertification in case the physician assumes oversight of patient care.